Related Experiment Video
Updated: Oct 29, 2026

Cardiac Loading using Passive Left Atrial Pressurization and Passive Afterload for Graft Assessment
Published on: August 2, 2024
Waitlist Outcomes of Multiorgan Heart Transplant Candidates
Ann B Nguyen1, Molly White1, Anthony Kanelidis1
1Department of Medicine, University of Chicago, Chicago, IL.

Background:
In recent years, the number of patients undergoing simultaneous multiorgan heart transplant (MOT) has increased significantly. However, there is no unified policy for MOT allocation, allowing Organ Procurement Organizations to individually determine priority for match runs across all organ types. We evaluated if heart transplant (HT) candidates listed simultaneously for a kidney or liver are at a disadvantage on the waitlist.
Methods:
Adult HT candidates registered with the Scientific Registry of Transplant Recipients between 2019-2023 were included. Candidates were waitlisted statuses 1-6 within the heart allocation system in order of medical urgency. The primary outcomes were transplantation and removal from the waitlist for death or clinical deterioration, estimated with cumulative incidence functions for the first-year after listing, stratified by both waitlist status and type of organ listing. Rates of transplantation and removal from the waitlist at 1 year were reported. Using cox proportional hazards models, cause-specific hazards of transplantation and removal, holding waitlist status constant were estimated.
Results:
Of 20,588 HT candidates, 9.3% were heart kidney (HK) and 1.4% were heart liver (HL) candidates. Irrespective of status, heart-alone candidates had higher cumulative incidence of transplant (70.6% vs. 67.9% HK, p < 0.01; vs. 63.6% HL, p < 0.01), and lower cumulative incidence of removal from the waitlist for death or deterioration (5.3% vs. 10.3%, p < 0.01); vs. 10.4%, p < 0.01). In adjusted analysis and stratified by candidate listing center, MOT listing was significantly associated with lower likelihood of transplant (HK: HR 0.71, 0.68-0.75; HL: HR 1.13, 1.09-1.17), and a significantly higher risk of delisting due to death or deterioration (HK: HR 2.08, 1.81, 2.39; HL: HR 2.45, 1.75, 3.42). Hemodialysis-dependent HK candidates experienced the highest cumulative incidence of death or deterioration at 1 year (13%) compared to non-hemodialysis dependent (8.7%, p < 0.01) and heart-alone (5.3%, p < 0.01) candidates, but similar to HL candidates (10.4%, p = 0.32).
Conclusion:
MOT candidates, especially HK, had worse waitlist outcomes with lower rates of transplantation and higher incidence of removal from the waitlist compared to heart-alone candidates. These outcomes demonstrate a need for MOT allocation based on criteria more reflective of medical urgency.
More Related Videos
 08:15
Innovative Strategies for Organ Preservation in Heart Transplantation: Uniform Cooling Preservation and Ex-situ Normothermic Perfusion
Published on: November 28, 2025
 08:15
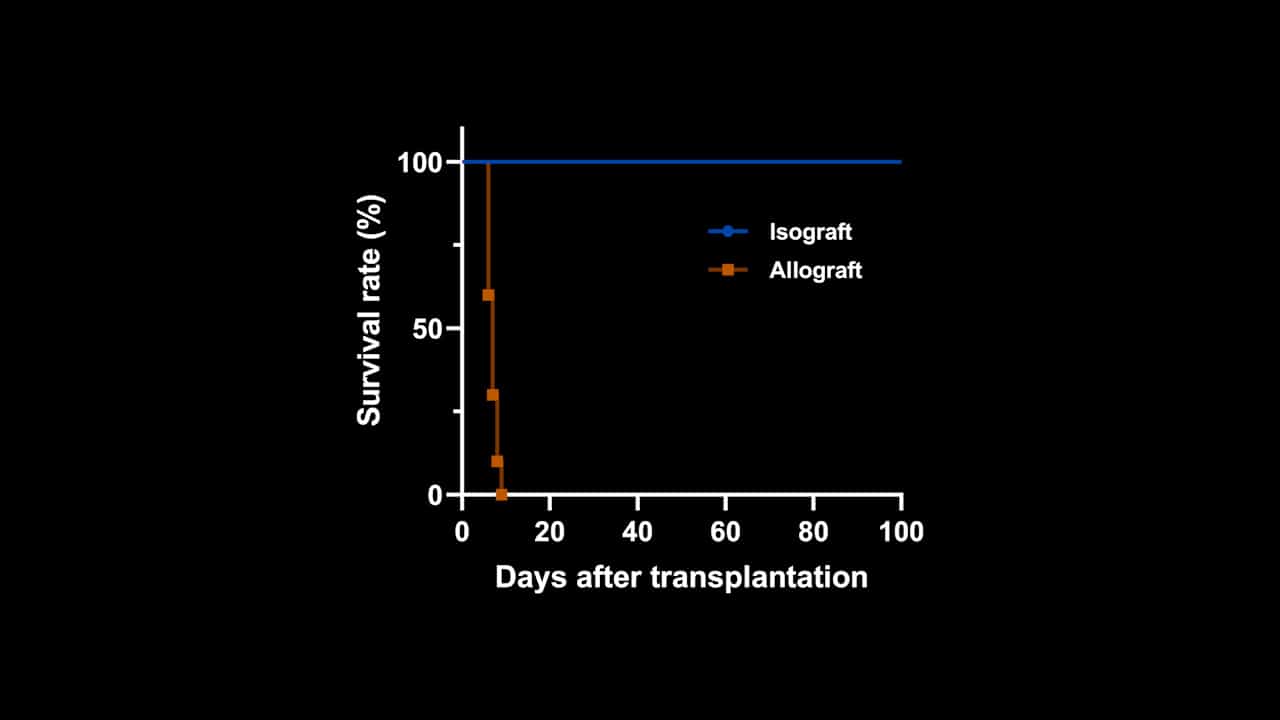
Cervical Heterotopic Mouse Heart Transplantation using End-to-side Anastomosis Technique to Study Transplant Immunology
Published on: July 3, 2026
Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...