Related Experiment Video
Updated: Oct 29, 2026
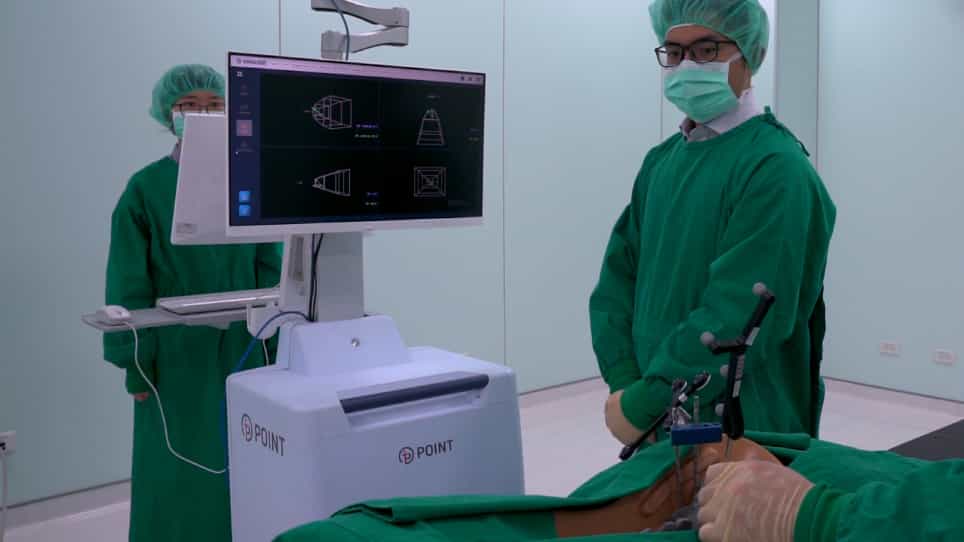
A Spine Robotic-Assisted Navigation System for Pedicle Screw Placement
Published on: May 11, 2020
Robotic navigation strategies for PFNA fixation: impact on one-time guide pin success rate and anteversion angle
Yong-Yi Huang1, Gui-Xiang Tang2, Yi-Fan Chen2
1Department of Orthopaedics & Traumatology, Yunfu People's Hospital, Regional Cooperative Hospital of Nanfang Hospital, Southern Medical University, No. 120 Huanshi East Road, Yunfu, 527300, Guangdong Province, PR China. hyy065@163.com.

Abstract:
This study evaluated the clinical efficacy of three navigation strategies (full robotic navigation, robotic navigation for the main nail only with freehand anteversion, and conventional freehand technique) in PFNA fixation for intertrochanteric fractures, analyzed factors affecting anteversion angle accuracy, and quantified the learning curve of robot-assisted surgery. A retrospective review was conducted on 121 intertrochanteric fracture cases managed with PFNA. We categorized patients into three groups by navigation strategy: G1 (double navigation, n = 41), G2 (single navigation, n = 40), and G3 (non-navigation, n = 40). Perioperative parameters (fluoroscopy time span, total fluoroscopy times, number of attempts, visible intraoperative blood loss, etc.) were compared among groups. The main metric assessed was the attempt frequency for anteversion determination (reflecting one-time success rate). Within G1, Spearman correlation and multivariable linear regression explored the associations between anteversion error and medullary canal diameter, as well as fluoroscopy times for main nail insertion. Curve estimation was used to evaluate learning curves for fluoroscopy time span and main nail insertion time. Baseline characteristics were similar across the three groups, with no significant differences (P > 0.05). The number of attempts to determine anteversion in G1 (1.22 ± 0.48) was significantly lower than in G2 (4.30 ± 2.49) and G3 (3.98 ± 1.93) (both P < 0.001). Regarding overall surgical efficiency, fluoroscopy time span in G1 (65.95 ± 8.71 min) was 12.0 min shorter (15.4% reduction, P < 0.05) than in G3 (77.93 ± 29.98 min), total fluoroscopy times (40.63 ± 7.89) were 16.3 fewer (28.6% reduction, P < 0.001); visible intraoperative blood loss (99.8 ± 91.2 mL) was 119.5 mL less (54.5% reduction, P < 0.001), and blood transfusion volume (0.73 ± 1.45 units) was significantly lower than in G3 (2.14 ± 1.72 units, P = 0.002). Compared with G2, G1 also showed significantly reduced fluoroscopy time span, total fluoroscopy times, and visible intraoperative blood loss (all P < 0.05). Main nail insertion time in G2 (43.78 ± 6.94 min) was significantly longer than in G3 (34.65 ± 17.59 min, P = 0.002), whereas G1 (37.80 ± 6.43 min) was not significantly different from G3. Within G1, anteversion error showed a strong negative correlation with medullary canal diameter (r = - 0.807, P < 0.001). Multiple regression identified medullary canal diameter as the only independent predictor of anteversion error (β = - 0.781, P < 0.001). Learning curve analysis demonstrated a marked reduction in fluoroscopy time span with robotic case order (R² = 0.644, P < 0.001), with the quadratic model providing the best fit. Full robotic navigation (double navigation) significantly improves anteversion-angle positioning efficiency (fewer attempts), reduces fluoroscopy time span and exposure frequency (suggesting lower radiation exposure), and decreases visible intraoperative blood loss. However, anteversion accuracy still depends on patient anatomy, particularly medullary canal diameter, necessitating consideration during preoperative planning. Moreover, the learning curve showed rapid early improvement, followed by a gradual plateau.
