Related Experiment Video
Updated: Oct 29, 2026

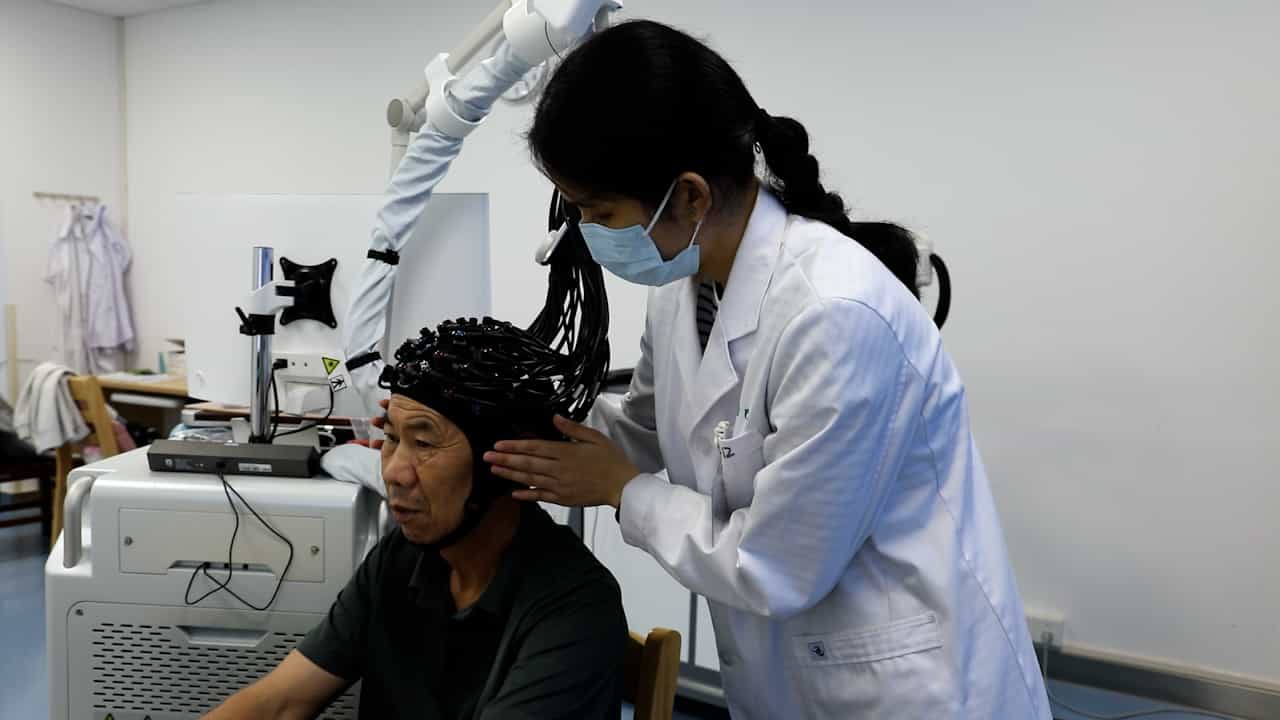
Motor Imagery Brain-Computer Interface in Rehabilitation of Upper Limb Motor Dysfunction After Stroke
Published on: September 1, 2023
The application of brain-computer interface combined with neuromodulation for stroke upper-limb rehabilitation: a
Hede Zhu1, Cong Kang1, Yuanyuan Luo2
1School of Health and Physical Education, Shangluo University, Shangluo City, Shaanxi, China.

Background:
In conventional rehabilitation, upper-limb recovery in patients with stroke is slow and limited. Motor Imagery-Based Brain-Computer Interface (MI-BCI) may promote cortical plasticity by translating brain signals into commands to control external devices; however, the effects of different intervention approaches remain unclear.
Methods:
This study followed the PRISMA 2020 statement and searched PubMed, EBSCO, Web of Science, Scopus, the Cochrane Library, and the China National Knowledge Infrastructure (CNKI) for randomised controlled trials (RCTs) reporting outcomes related to upper-limb function or activities of daily living. Risk of Bias 2 (RoB 2) and Confidence in Network Meta-Analysis (CINeMA) were used to assess risk of bias and confidence in the evidence. Network meta-analysis was conducted using the network and mvmeta modules in Stata 18.0 to assess heterogeneity, network consistency, robustness of the results, and publication bias.
Results:
A total of 49 studies involving 2,209 participants and 13 intervention strategies were included. For the Fugl-Meyer Assessment of the Upper Extremity (FMA-UE), interventions showing relatively favourable effects included MI-BCI combined with transcranial ultrasound stimulation and functional electrical stimulation (FES) (MD = 17.65, 95% CI: 6.88 to 28.43), MI-BCI combined with repetitive transcranial magnetic stimulation (rTMS) and rehabilitation robotics (ROB) (MD = 14.22, 95% CI: 2.98 to 25.47), and MI-BCI combined with transcranial direct current stimulation (tDCS) and ROB (MD = 13.59, 95% CI: 6.90 to 20.28). For the Action Research Arm Test (ARAT), favourable interventions included MI-BCI combined with ROB and tDCS (MD = 17.26, 95% CI: 5.96 to 28.55) and MI-BCI combined with FES (MD = 14.94, 95% CI: 9.10 to 20.78). For the Wolf Motor Function Test (WMFT), MI-BCI combined with ROB showed the largest effect (MD = 10.72, 95% CI: 9.44 to 17.18). For the Modified Barthel Index (MBI), favorable interventions included MI-BCI combined with tDCS and ROB (MD = 20.40, 95% CI: 11.21 to 29.60), MI-BCI combined with rTMS and ROB (MD = 19.46, 95% CI: 9.33 to 29.59), and MI-BCI combined with intermittent theta-burst stimulation and ROB (MD = 18.24, 95% CI: 5.93 to 30.55). Overall, the network evidence showed no obvious inconsistency; between-study heterogeneity was within an acceptable range, and no clear publication bias was detected.
Conclusion:
Some non-invasive MI-BCI combined interventions like neuromodulation, ROB, or FES might improve upper-limb function and daily activities in stroke patients. However, rankings don't imply clinical importance. Due to small samples, limited evidence, and differences, these findings need confirmation in larger trials.