Associations Between Diagnostic Blood-Based Biomarkers and Neuroimaging Findings in Mild Traumatic Brain Injury
Related Experiment Video
Updated: Oct 30, 2026

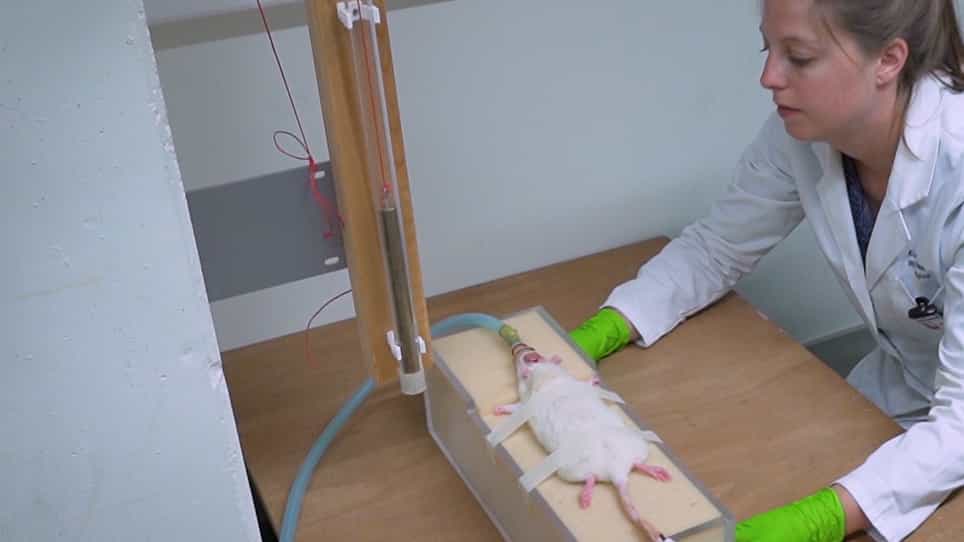
Systems Analysis of the Neuroinflammatory and Hemodynamic Response to Traumatic Brain Injury
Published on: May 27, 2022
Shraddha Pandey1, Yanying Chen1, John K Yue2
1School of Medicine, University of California, San Francisco, San Francisco, CA.

Study Objective:
Mild traumatic brain injury (mTBI) is a prevalent and resource-intensive injury in the emergency department (ED). The blood-based biomarkers glial fibrillary acidic protein (GFAP) and ubiquitin c-terminal hydrolase L1 (UCH-L1) have demonstrated diagnostic potential for acute structural brain injury. Our objective was to clinically validate a US Food and Drug Administration-approved plasma test to aid in the identification of intracranial injury in patients with mTBI presenting to the ED and assess its integration with existing protocols.
Methods:
This single-center validation study enrolled 104 adult patients with suspected mTBI undergoing head computed tomography (CT) for evaluation between October 2023 and June 2024 at a Level I trauma center. Peripheral blood draw was completed within 12 hours postinjury and processed at the hospital clinical laboratory. Sensitivity, specificity, and predictive values for the test were calculated and compared with a standard clinical decision rule (Canadian Head CT Rule). ED length of stay and diagnostic turnaround times were examined.
Results:
Within the cohort (n=104), 83 patients had elevated biomarker levels (GFAP >30 pg/mL or UCH-L1 >360 pg/mL), and 11 patients had intracranial injury identified on CT. The combination plasma test demonstrated high sensitivity (0.91 [95% confidence interval {CI} 0.59 to 1.00]) but low specificity (0.22 [95% CI 0.14 to 0.31]) for predicting intracranial injury on CT with low positive predictive value (0.12 [95% CI 0.06 to 0.21]) and high negative predictive value (0.95 [95% CI 0.76 to 1.00]). These findings are consistent with prior studies (pooled sensitivity 0.97 [95% CI 0.95 to 0.98]; specificity 0.28 [95% CI 0.23 to 0.34]). False-positive cases (78%) were older than true-negative cases (median 72 years [interquartile range (IQR) 54 to 83] versus 58.5 years [IQR 38.25 to 66]). Median turnaround time for the GFAP/UCH-L1 test was 2 hours faster than head CT (1.09 hours [IQR 0.87 to 1.65] versus 3.28 hours [IQR 2.37 to 4.70]).
Conclusions:
Blood biomarkers for mTBI have potential as an initial rule-out tool for intracranial injury prior to obtaining CT imaging; however, large multicenter studies are needed to clarify its impact on ED resource utilization, length of stay, and acute and long-term costs and benefits to patients and health care systems.