Long-Term Pancreatic Function, Reconstruction Durability, and Disease Control After Pancreas-Preserving Total Duodenectomy: Systematic Review and Single-Arm Meta-Analysis
Related Experiment Video
Updated: Oct 30, 2026
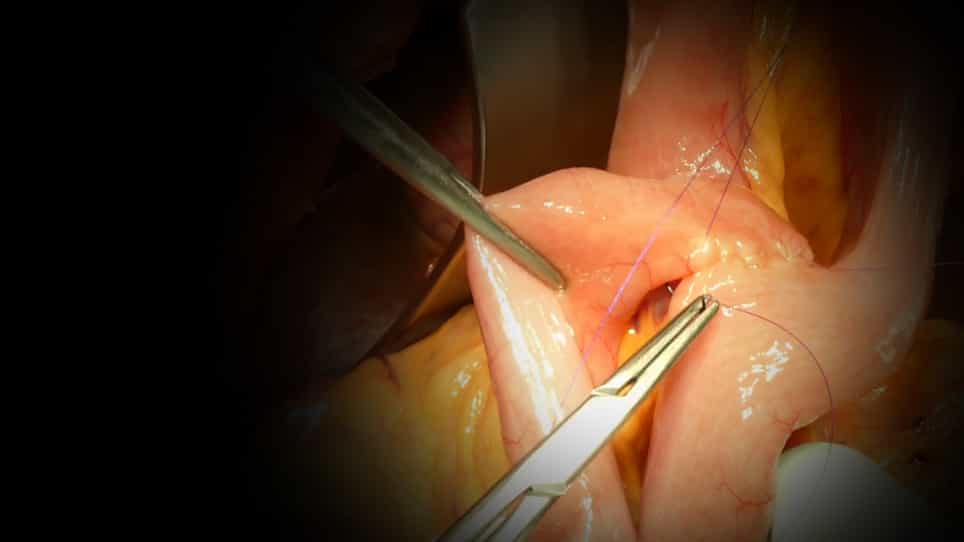
Modified Single-Loop Reconstruction for Pancreaticoduodenectomy
Published on: September 28, 2019
Philipe Franco do Amaral Tafner1, Giulia Trucolo de Brito1, Morgana Danúbia Gomes de Souza Bonfitto2
1Department of Surgery, School of Medical Sciences, University of Campinas (UNICAMP), Campinas, SP, Brazil.

Background:
Pancreas-preserving total duodenectomy (PPTD) enables complete duodenal resection while preserving the pancreatic head in selected benign or premalignant disease. Long-term pancreatic function, reconstruction durability, and disease control after PPTD remain incompletely defined.
Methods:
We performed a PRISMA-compliant systematic review and single-arm meta-analysis registered in PROSPERO. PubMed, Scopus, Web of Science, and the Cochrane Library were searched through June 29, 2026. Institutional reports were grouped into cohort families to avoid patient duplication. Pooled proportions were estimated using inverse-variance logit models or generalized linear mixed models for prespecified outcomes with zero events. Risk of bias and certainty of evidence were assessed using ROBINS-I and GRADE.
Results:
Nine independent retrospective cohorts comprising 199 patients were included; 86.4% had familial adenomatous polyposis, and follow-up ranged from 20 to 125 months. Overall postoperative morbidity was 64.7% (95% CI, 51.5-76.0), major morbidity 40.3% (28.5-53.3), biliopancreatic anastomotic leakage 32.1% (23.5-42.1), and clinically relevant postoperative pancreatic fistula 27.5% (17.5-40.5). One early postoperative death was reported. New-onset diabetes and exocrine pancreatic insufficiency were each reported in 1.8%, and subsequent pancreatic resection occurred in 3.6%. Late pancreatitis occurred in 18.3%, recurrent pancreatitis in 12.4%, biliopancreatic stenosis in 5.0%, cholangitis in 3.3%, and late reoperation in 9.5%. Endoscopic surveillance was documented in 83.3%; jejunal adenomas occurred in 25.8%, additional jejunal resection in 4.8%, jejunal cancer in 2.5%, and gastric cancer in 4.6%. Certainty of evidence was very low across outcomes.
Conclusions:
PPTD is associated with substantial perioperative morbidity but low early mortality, with infrequently reported long-term endocrine and exocrine impairment, although no study applied functional testing. Late pancreatitis and metachronous jejunal disease remain clinically relevant and support lifelong endoscopic surveillance. Evidence remains limited to small retrospective series and does not establish comparative superiority over other surgical strategies.
