Risk Stratification of Prostate Imaging Reporting and Data System (PI-RADS 3) Lesions in the Peripheral and Transition Zones Using Clinical and Quantitative MRI Markers
Related Experiment Video
Updated: Oct 30, 2026

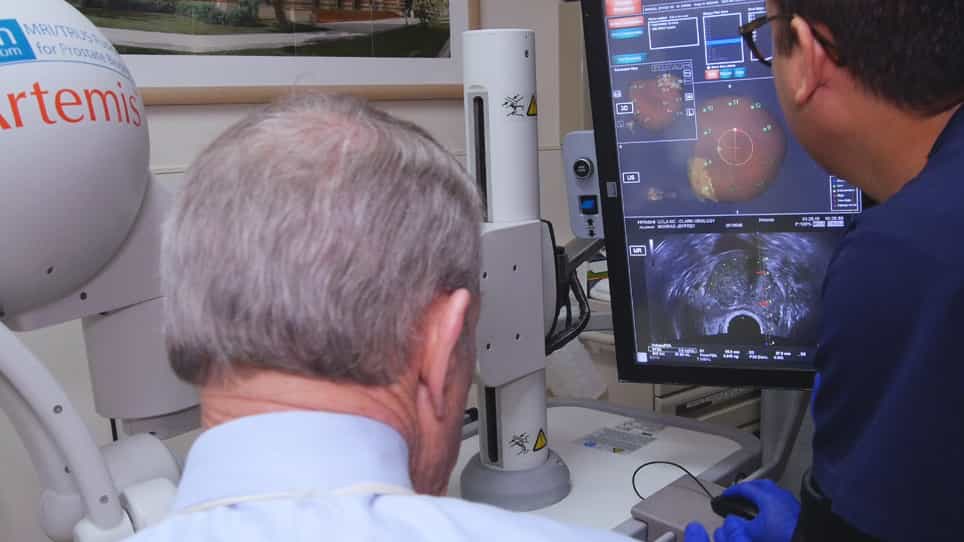
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
Tejinder Kaur1, Reve Chahine1, Nicole Seiberlich1,2
1Department of Radiology, University of Michigan, Ann Arbor, Michigan, USA.

Background:
Prostate Imaging Reporting and Data System (PI-RADS) 3 lesions often undergo biopsy despite a low positive predictive value (< 25%) for clinically significant prostate cancer (csPCa), defined as International Society of Urological Pathology (ISUP) Grade Group ≥ 2.
Purpose:
To determine whether mean apparent diffusion coefficient (mADC), alone or with prostate-specific antigen (PSA)-based metrics, improves zone-specific PI-RADS 3 classification for csPCa detection.
Study Type:
Retrospective, single-center.
Population:
One hunderd and seventy-one males (71 ± 8 years) with 191 PI-RADS 3 lesions who underwent multiparametric MRI and targeted biopsy.
Field Strength/Sequence:
3 T, T2-weighted turbo spin-echo imaging, single-shot echo-planar diffusion-weighted imaging, and fat-suppressed dynamic contrast-enhanced T1-weighted gradient echo sequences.
Assessment:
mADC, PSA, PSA density (PSAD), prostate volume, and body mass index were analyzed.
Statistical Tests:
Logistic regression and receiver operating characteristic (ROC) analyses assessed associations with malignancy and diagnostic performance.
Results:
mADC was significantly lower in cancers than non-cancers in 133 PZ lesions (885 ± 165 vs. 1068 ± 168 × 10-6 mm2/s) and 58 TZ lesions (670 ± 127 vs. 832 ± 179 × 10-6 mm2/s). In the PZ, mADC alone, and with PSAD showed no significantly different area under the curve (AUC, 0.79 vs. 0.80, p = 0.28). A combination of mADC and PSAD would result in hypothetical estimated lesion-level biopsy avoidance. In the TZ, combining mADC with PSAD yielded significantly higher AUC than mADC alone (0.88 vs. 0.77, difference: 0.109 [95% CI: 0.010-0.208]). This combination would result in hypothetical estimated lesion-level biopsy avoidance in 58 of 82 non-cancers (71%) while missing one csPCa in the PZ, and 27 of 35 noncancerous lesions while missing one csPCa in TZ.
Data Conclusion:
mADC combined with PSAD showed a significant increase in discrimination in the TZ, suggesting improved PI-RADS 3 stratification; independent validation is required before clinical implementation.
Evidence Level:
3.
Technical Efficacy:
2.