Rhythmic auditory stimulation combined with split-belt treadmill training improves spatiotemporal gait parameters in hemiparetic stroke patients: a randomized controlled trial
Related Experiment Video
Updated: Oct 30, 2026
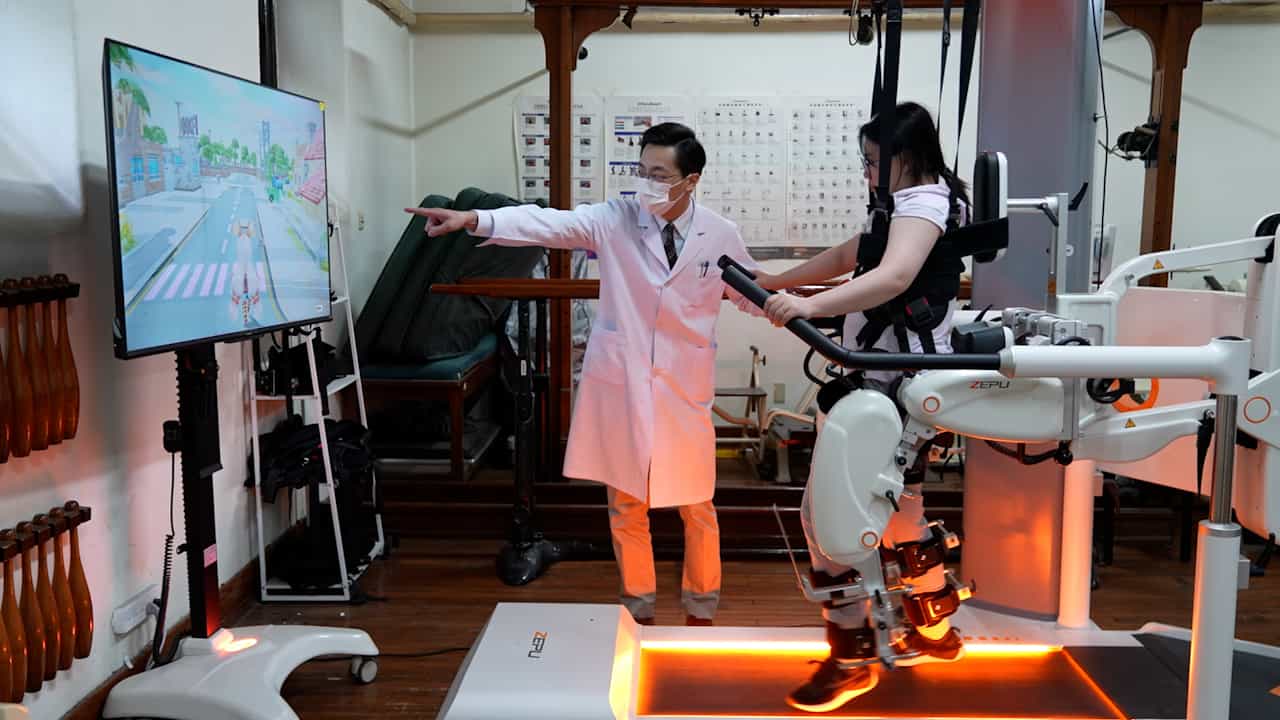
A Rehabilitation Program of Exoskeleton-assisted Body Weight-Supported Treadmill Training with Non-immersive Virtual Reality for Stroke Patients
Published on: May 16, 2025
Minghui Du1, Wei Zhang1, Liang Xia1
1School of Physical Education, Xi'an Jiaotong University, Xi'an, Shaanxi, China.

Background:
Split-belt walking training (SWT) primarily ameliorates spatial gait asymmetry after stroke, yet its effect on temporal gait parameters remains limited. Rhythmic auditory stimulation (RAS) enhances cadence and rhythmicity via auditory-motor coupling. This study examined whether combining RAS with SWT yields greater walking benefits than SWT alone or conventional rehabilitation.
Methods:
Thirty patients with post-stroke hemiparesis were randomized to RAS+SWT (n = 11), SWT alone (n = 8), or conventional rehabilitation (control, n = 11). Interventions were delivered for three weeks (five sessions/week). Primary outcomes were spatiotemporal gait parameters: walking speed, cadence, step length, and limping index. Linear mixed-effects models were used, with Hedges' g for effect sizes.
Results:
No dropouts occurred. Significant time-group interactions were found for walking speed (F = 10.68, p < 0.001), cadence (F = 5.01, p = 0.014), and affected-side step length (F = 6.21, p = 0.006). The RAS+SWT group showed greater improvements than controls in walking speed (mean difference = 0.167, 95% CI [0.090, 0.245]), cadence (mean difference = 9.340, 95% CI [4.456, 14.223]), and step length (unaffected: mean difference = 0.077, 95% CI [0.039, 0.116]; affected: mean difference = 0.081, 95% CI [0.035, 0.127]), and greater walking speed improvements than the SWT group (mean difference = 0.110, 95% CI [0.022, 0.197]). For the limping index, a significant main effect of group was observed (F = 5.41, p = 0.011); however, the time-by-group interaction was not significant (F = 0.430, p = 0.655).
Conclusion:
RAS combined with SWT is more effective than conventional rehabilitation in improving multidimensional spatiotemporal gait parameters-including walking speed, cadence, and affected-side step length-in patients with post-stroke hemiparesis. Compared with SWT alone, the combined intervention yielded greater improvements in walking speed, while no significant between-group differences were observed for cadence or step length. The combined protocol is feasible and safe.
Clinical Trial Registration:
ChiCTR2600121963.
