Xerostomia symptom severity and frailty among community-dwelling older adults: a survey-weighted structural equation modeling analysis
Related Experiment Video
Updated: Oct 31, 2026
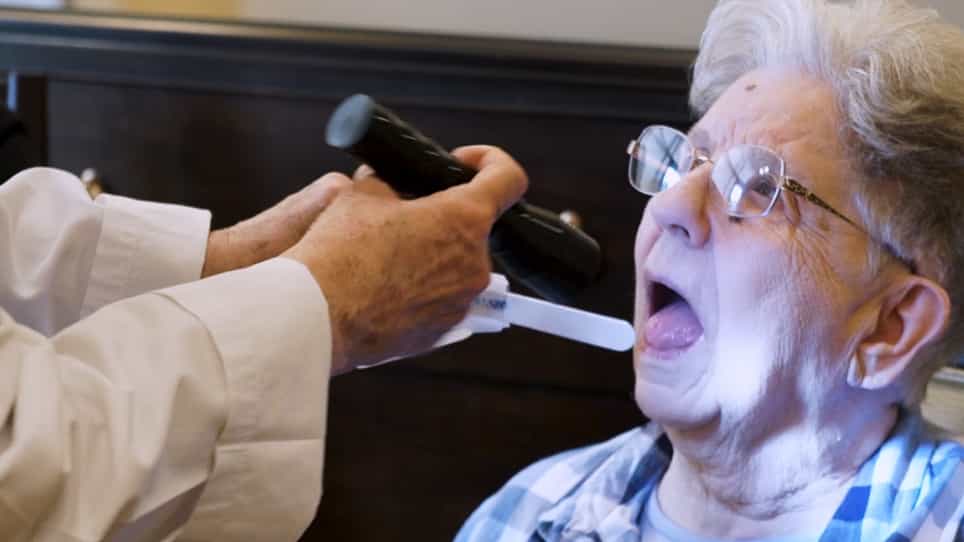
Oral Health Assessment by Lay Personnel for Older Adults
Published on: February 2, 2020
Patrícia Soares da Silva Pereira1, Billy de Jesus Vieira de Paula E Silva2, Ana Laura Melo Gonçalves2
1Bauru School of Medicine, University of São Paulo, Bauru, Brazil.

Objective:
To investigate the direct and indirect associations between xerostomia symptom severity and frailty among community-dwelling older adults, considering nutritional vulnerability as a potential mediator using structural equation modeling.
Methods:
This cross-sectional population-based study analyzed 398 community-dwelling older adults from two municipalities in southeastern Brazil. Xerostomia was assessed using the Summated Xerostomia Inventory (SXI-5), nutritional status using the Mini Nutritional Assessment-Short Form (MNA-SF), and frailty using the Edmonton Frail Scale (EFS). Xerostomia, nutritional vulnerability, and frailty were modeled as continuous scores. Nutritional vulnerability was calculated as 14 minus the MNA-SF score, with higher values indicating poorer nutritional status. Survey-weighted structural equation modeling estimated direct, indirect, and total associations, adjusting for age, sex, and educational attainment and accounting for clustering in the sampling design.
Results:
The weighted prevalence of high xerostomia symptoms was 24.5% (95% CI: 16.2-35.3), nutritional risk or malnutrition was 35.5% (95% CI: 29.7-41.8), and frailty was 12.3% (95% CI: 6.5-22.1). Xerostomia symptom severity was not significantly associated with nutritional vulnerability (B = 0.146; 95% CI: -0.073 to 0.364; standardized β = 0.179; P = 0.177). Nutritional vulnerability was associated with higher EFS scores (B = 0.226; 95% CI: 0.046-0.405; β = 0.206; P = 0.017). Xerostomia symptom severity showed a significant direct association with the EFS score (B = 0.130; 95% CI: 0.008-0.252; β = 0.145; P = 0.039) and a significant total association (B = 0.163; 95% CI: 0.012-0.313; β = 0.182; P = 0.036). However, the indirect association through nutritional vulnerability was not statistically significant (B = 0.033; 95% CI: -0.022 to 0.088; β = 0.037; P = 0.225). The model explained 9.2% of the variance in nutritional vulnerability and 15.3% of the variance in frailty.
Conclusions:
Greater xerostomia symptom severity was directly associated with higher frailty scores, but there was no evidence of an indirect association through nutritional vulnerability. These findings indicate that the relationship between xerostomia and frailty may involve pathways beyond nutritional status and reinforce the potential value of integrating oral health assessment into comprehensive care for older adults.
