Gonadotropin-releasing hormone antagonists versus agonists for endometriosis: a systematic review and meta-analysis of randomized controlled trials
Related Experiment Video
Updated: Oct 31, 2026
Surgical Techniques to Optimize Ovarian Reserve during Laparoscopic Cystectomy for Ovarian Endometrioma
Published on: January 22, 2022
Tianmeng Liu1, Yuhong Cai2, Mingyang Li3
1Department of Obstetrics and Gynecology, Xiamen Susong Hospital, Xiamen, Fujian, China.

Background:
Endometriosis is a chronic estrogen-dependent inflammatory disease requiring individualized long-term hormonal management. Gonadotropin-releasing hormone agonists (GnRH-a) effectively suppress ovarian function but may induce hypoestrogenic adverse effects, whereas oral gonadotropin-releasing hormone antagonists (GnRH-ant) offer rapid, reversible suppression with reduced hormonal fluctuation. However, their comparative efficacy and safety remain unclear.
Methods:
We performed a systematic review and meta-analysis of randomized controlled trials comparing GnRH-ant with leuprolide-based GnRH-a for the treatment of endometriosis, assessing symptom relief, pelvic signs, bone mineral density (BMD), quality of life, and hormonal outcomes.
Results:
Five randomized controlled trials were included. Compared with GnRH-ant, GnRH-a yielded greater improvements in dysmenorrhea (standardized mean difference (SMD) = 0.69, 95% CI: 0.48-0.91), nonmenstrual pelvic pain (NMPP) (SMD = 0.33, 95% CI: 0.16-0.50), overall pelvic pain (OPP) (SMD = 0.25, 95% CI: 0.13-0.38), and dyspareunia (SMD = 0.14, 95% CI: 0.02-0.26). GnRH-a was also associated with better outcomes in pelvic tenderness, Douglas pouch induration scores, peak pain severity, analgesic requirements, and menstrual blood loss. Subgroup analysis suggested a more pronounced analgesic benefit of GnRH-a after 12 weeks of treatment. In contrast, GnRH-ant resulted in significantly less BMD reduction (SMD = 0.64, 95% CI: 0.39-0.89), a stronger bone-sparing effect at 24 weeks. No significant differences were observed in most quality-of-life domains.
Conclusions:
Leuprolide-based GnRH-a provides superior symptom control, whereas GnRH-ant offers less decline in BMD and reversible ovarian suppression, but differences among individual antagonists should be considered. Treatment selection should be individualized based on symptom severity, bone health, and fertility goals. Long-term head-to-head trials are warranted.
Systematic Review Registration:
https://www.crd.york.ac.uk/PROSPERO/view/CRD420261289010, identifier CRD420261289010.
Related Concept Videos
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:25
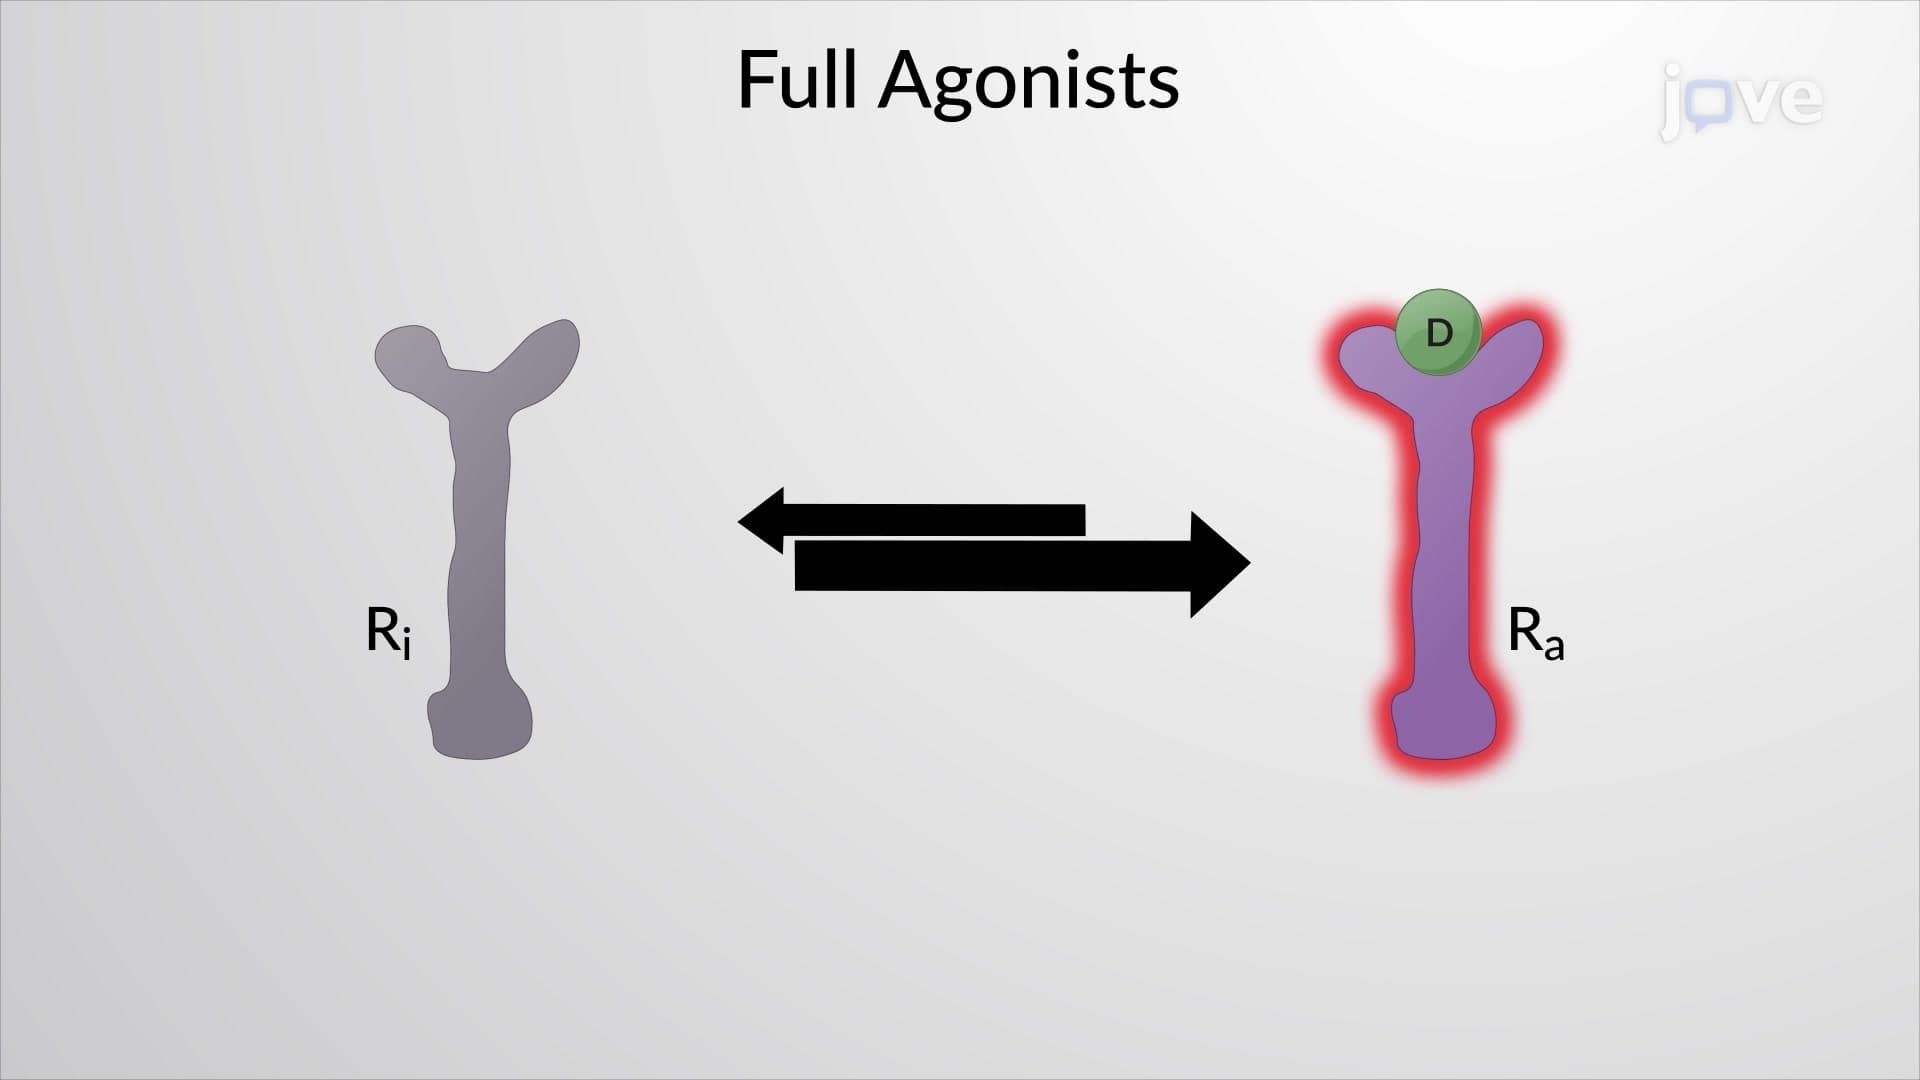
Drug-Receptor Interaction: Agonist
Agonists can bind to receptors in different ways. Some agonists bind directly to the receptor's active site, mimicking the endogenous ligand's action.