Spirometry documentation gaps and reporting delays in a COPD reporting system: implications for surveillance data quality
Related Experiment Video
Updated: Oct 31, 2026
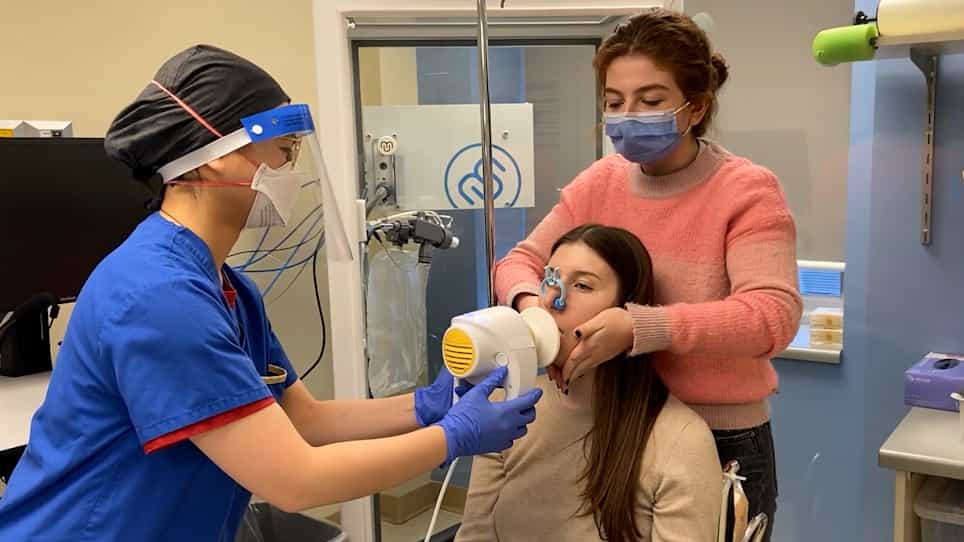
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Changfu Chen1,2, Jiali Zhou1,2, Hongying Zhang1,2
1Department of Science and Education, Rehabilitation Hospital of Chongqing Medical University, Chongqing, China.

Background:
Chronic obstructive pulmonary disease (COPD) reporting systems can support public health surveillance and quality improvement, but their value depends on complete diagnostic documentation and timely data entry.
Methods:
We conducted a retrospective cross-sectional analysis of records from the COPD case-reporting module of the Chongqing municipal chronic disease monitoring platform, provided by the Chongqing Center for Disease Control and Prevention, with clinical visit dates in 2024. Records from persons younger than 40 years were excluded. Acute exacerbation of COPD (AECOPD) was classified from explicit diagnostic text indicating acute exacerbation. Spirometry documentation was defined as diagnostic-basis documentation of pulmonary function testing or a recorded pre- or post-bronchodilator FEV1/FVC value. Reporting delay was calculated from the clinical visit date to the system-recorded entry timestamp; >7 days was prespecified as an operational quality threshold rather than a statutory reporting deadline, with >14- and >30-day thresholds examined in sensitivity analyses.
Results:
Among 1,076 included records, median age was 73.2 years (IQR 68.1-80.3), and 829 (77.0%) records were for males. AECOPD was explicitly recorded in 357 (33.2%) records. Any spirometry documentation was present in 195 (18.1%) records, diagnostic-basis spirometry in 167 (15.5%), and post-bronchodilator FEV1/FVC in 133 (12.4%). Older age was associated with higher odds of absent spirometry documentation (OR 1.03 per year, 95% CI 1.01-1.04), whereas municipal-hospital records had lower odds than county/district-hospital records (OR 0.52, 95% CI 0.33-0.82). Median reporting delay was 19 days (IQR 9-32.5), and 851 (79.1%) records were entered >7 days after the visit.
Conclusion:
Gaps in spirometry documentation and delays in reporting-system entry were common. These findings identify actionable data-quality targets for COPD surveillance systems, particularly structured spirometry-status fields, explicit reasons for unavailable testing, and routine timeliness monitoring. Because the study evaluated submitted records from a single municipal reporting system, the findings should not be interpreted as estimates of clinical spirometry utilization or population-level case capture and should be validated in other reporting settings.
Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:28
Physical Assessment of the Respiratory Tract I: Health History
Subjective Data
Subjective data provides vital information about the patient's health history and symptoms. This data is typically collected through interviews in which patients describe their experiences, symptoms, and concerns.
Health history and key...
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...