Intraoperative ventilatory air leak as a predictor of prolonged air leak following lung resection: a pilot prospective comparative study
Related Experiment Video
Updated: Oct 31, 2026

Non-Intubated Video-Assisted Thoracoscopic Surgery
Published on: May 26, 2023
Haritha Therese Joseph1, Sabyasachi Bal1, Rohit Kumar Rathi1
1Department of Thoracic Surgery and Thoracic Surgical Oncology, Sir Ganga Ram Hospital, New Delhi, India.

Background:
Prolonged air leak (PAL) remains a common complication following pulmonary resection and is associated with increased morbidity, prolonged hospitalisation, and higher healthcare costs. The Brunelli Score (BS) is a validated clinical prediction model for PAL, while intraoperative ventilatory air leak (VAL) has emerged as a potential physiological predictor. This pilot study evaluated the predictive value of VAL and compared its performance with BS.
Methods:
This prospective observational pilot study included 109 patients undergoing pulmonary resection between September 2022 and December 2024. Preoperative BS and intraoperative VAL measurements were recorded. PAL was defined as air leak persisting beyond postoperative day 5. Receiver operating characteristic (ROC) analysis, logistic regression, and three-group comparative analysis were performed.
Results:
PAL occurred in 24 patients (22%). VAL demonstrated an area under the curve (AUC) of 0.818 (95% confidence interval (CI) 0.715-0.921), while BS demonstrated an AUC of 0.656 (95% CI 0.536 to 0.776). The optimal VAL cut-off (≥ 11.1%) yielded 58.3% sensitivity and 94.1% specificity, whereas BS (≥ 2.5) also demonstrated the same sensitivity but a lower specificity (64.7%). The difference in AUC was 0.162 (95% CI 0.003 to 0.322) and reached nominal statistical significance on DeLong comparison (p = 0.046). On multivariable analysis, VAL ≥ 11.1% remained independently associated with PAL (adjusted odds ratio (OR) 17.22, 95% CI 4.56 to 65.07, p < 0.001), whereas the BS was not independently predictive after adjustment (adjusted OR 0.55, 95% CI 0.12 to 2.55, p = 0.446). Lower forced expiratory volume in 1 s (FEV1), open thoracotomy, major resection, dense pleural adhesions, and infective pulmonary pathology were associated with PAL on univariable analysis.
Conclusions:
VAL demonstrated higher discrimination and a stronger independent association with PAL than the BS. The difference between the two AUCs was of borderline statistical significance in a cohort well short of the calculated sample size, so definitive superiority cannot be claimed on these data. The BS and VAL may have complementary roles in preoperative risk stratification and intraoperative physiological assessment of PAL risk. Larger multicentre studies are required for validation.
Graphical Abstract:
Intraoperative ventilatory air leak (VAL) and the preoperative Brunelli Score were compared as predictors of prolonged air leak in 109 consecutive patients undergoing elective pulmonary resection. Prolonged air leak occurred in 24 patients (22.0%). VAL discriminated better than the Brunelli Score (area under the curve 0.818 versus 0.656), and the difference reached borderline statistical significance on DeLong testing (p = 0.046). VAL was the only variable retaining independent significance after adjustment for surgical approach, extent of resection and dense pleural adhesions. AUC, area under the curve; ROC, receiver operating characteristic curve; BMI, body mass index; CI, confidence interval; FEV₁, forced expiratory volume in 1 second; VAL, ventilatory air leak.
Supplementary Information:
The online version contains supplementary material available at https://doi.org/10.1007/s12055-026-02276-8.
Related Concept Videos
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:15
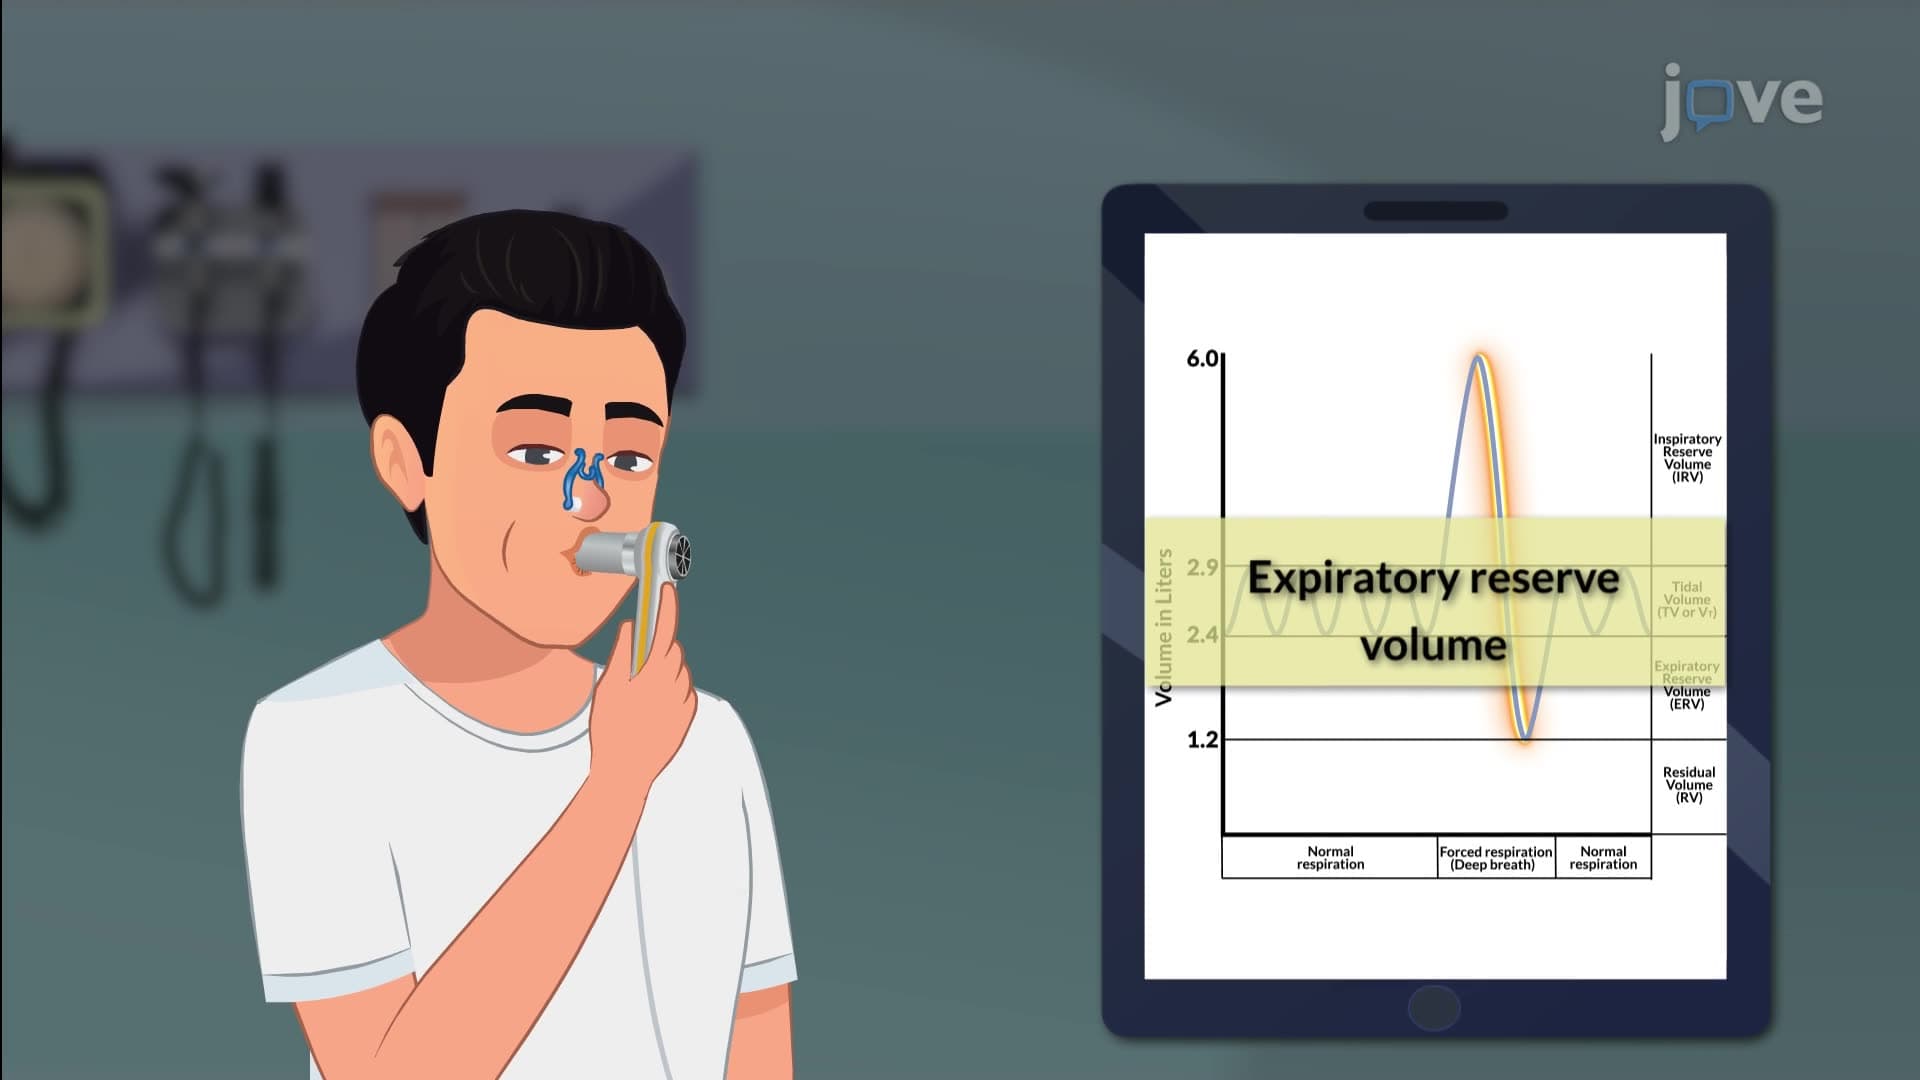
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...