Intermuscular Posterolateral Minimally Invasive Open Approach Revisited: Spectrum of Applications and Stabilization Outcomes
Related Experiment Video
Updated: Oct 31, 2026
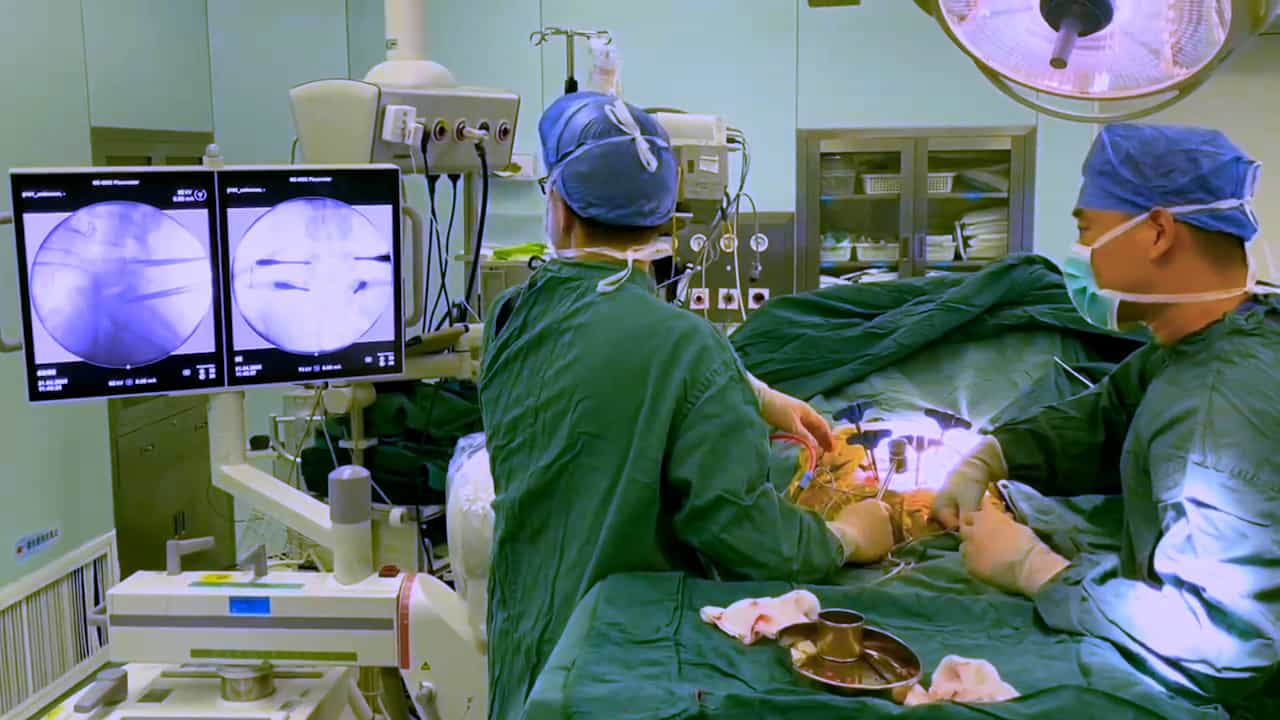
Novel Mini-open Transforaminal Lumbar Interbody Fusion
Published on: June 6, 2025
Ajay Krishnan1,2, Bharatkumar R Dave2, Amritesh Singh2
1Spine Surgery, Bhavnagar Institute of Medical Science, Bhavnagar, IND.

Introduction And Aim:
Conventional posterior midline open surgical approach (COA) for thoracolumbar spine fixation requires extensive muscular dissection and retraction, resulting in significant complications, including excessive intraoperative bleeding, prolonged postoperative pain, muscle ischemia, and delayed functional recovery. While percutaneous pedicle screw fixation (PPSF) offers reduced invasiveness, it carries inherent risks of radiation exposure and high rates of pedicle screw breach. The posterolateral intermuscular minimally invasive open approach (PLOA) represents an alternative MISS technique that develops an intermuscular plane between paraspinal muscles. This study aimed to evaluate the safety, efficacy, and clinical utility of PLOA pedicle screw fixation (PSF) in various thoracolumbar spine pathologies requiring stabilization without extensive decompression Materials and methods: A retrospective analysis was conducted on 47 patients who underwent PLOA PSF between January 2016 and January 2023 at a tertiary care spinal unit and peripheral unit, with a minimum 24-month follow-up. Inclusion criteria encompassed traumatic fractures, fragility fractures, and pathological fractures, including spondylodiscitis and metastatic disease. Standard preoperative classification systems were applied for traumatic fractures, pathological fractures, and infectious cases. Surgical technique involved 8-10 cm paramedian incisions utilizing region-specific intermuscular posterolateral planes. Intraoperative variables, including operative time, blood loss, and screw accuracy, were documented. Postoperative assessment included hospital length of stay, analgesic requirements compared to COA, complications, and radiographic loss of correction on immediate and final follow-up radiographs using segmental Cobb's angles. Statistical analysis was performed using SPSS version 20.0 (Chicago, IL: SPSS Inc.).
Results:
A total of 47 patients (mean age 59.1±12.04 years; 53%, n=25 males) were enrolled. Primary indications included traumatic fractures (38.2%, n=18), infective spondylodiscitis (36.2%, n=17), pathological tumors (12.7%, n=6), and fragility fractures (8.5%, n=4). A total of 289 pedicle screws were placed (mean 6.14±1.43 per patient), with 100% accuracy achieved in both fluoroscopic (51%, n=24 patients) and O-arm navigated (49%, n=23 patients) insertions. Mean operative time was 61.73±14.9 min and 59.56±11.06 min, with minimal blood loss of 44.78±8.45 mL and 45.21±8.45 mL. Hospital stay averaged 2.46±0.55 days. Postoperatively, 61.7% (n=29) of patients required less analgesia than COA patients, while 29.7% (n=14) required equivalent analgesia and 8.5% (n=4) required more. Loss of correction ranged from 0-20° (mean: 3.46±4.92°) in 30 patients (63.8%), while 17 patients (36.2%) maintained correction. Complications were minimal, with 95.7% (n=45) experiencing no adverse events.
Conclusion:
PLOA represents a viable minimally invasive intermuscular dissection alternative for open thoracolumbar spine stabilization across diverse pathologies, demonstrating superior technical efficiency, minimal blood loss, and rapid postoperative recovery. It is a lower-morbidity approach in resource-limited settings where PPSFs per se are costlier or technology is unavailable in remote settings.