Basic science and surgical timing for polytrauma patients
Related Experiment Video
Updated: Oct 31, 2026
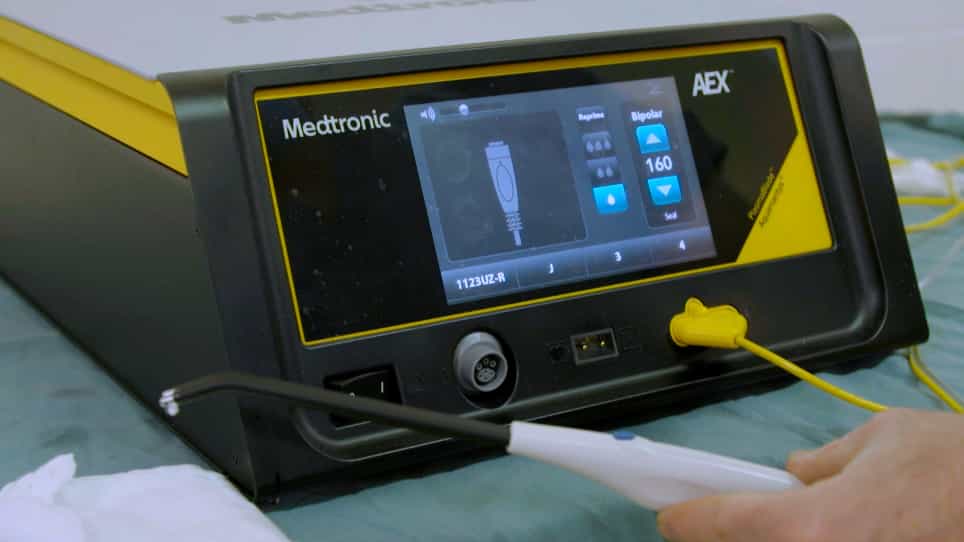
A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Emily Pedrick1, Roman Pfeifer2, Emil Schemitsch3
1Department of Orthopaedic Surgery, University of Utah, Salt Lake City, UT.

Abstract:
Polytrauma patients are a challenging cohort to treat because their multiple, potentially life-threatening injuries act synergistically with surgeries to affect cellular pathways necessary for survival. Current treatment algorithms and blood tests often fail to predict which patients will tolerate early fracture fixation and which patients will continue to deteriorate because of their injuries. Traditional laboratory tests in polytrauma patients have not been able to capture the nuances of cellular energy depletion, and lipidomics are now emerging as potential biomarkers to better categorize disease severity. Definitive treatment of fractures in polytrauma patients within 36 hours is recommended, but there is little consensus on the parameters necessitating "damage control" strategies. The IMPACT group recommends fixation within 24 hours and a dynamic treatment strategy rather than strict guideline adherence. In particular, patients with moderate to severe traumatic brain injury require cautious, individualized decision-making given their neurologic risks. The purpose of this review is to describe emerging diagnostic tools and treatment algorithms that are shifting the management of polytrauma patients from rigid protocols towards dynamic, individualized assessments.
Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:22
Aneurysm IV: Nursing Management