Neuromuscular Remodeling in Knee Osteoarthritis Across Aging: An Evidence-Bounded Joint-Afferent-Motor Unit Framework
Related Experiment Video
Updated: Oct 31, 2026
Dissection of Single Skeletal Muscle Fibers for Immunofluorescent and Morphometric Analyses of Whole-Mount Neuromuscular Junctions
Published on: August 14, 2021
1Department of Acupuncture and Tuina, Affiliated Hospital of Gansu University of Chinese Medicine, Lanzhou, Gansu, 730000, People's Republic of China.

Abstract:
Quadriceps weakness is a major determinant of disability in knee osteoarthritis (KOA), particularly in later life, yet weakness often exceeds the loss of muscle size. This discrepancy is clinically important because joint-derived activation failure occurs against a background of declining neuromuscular and regenerative reserve. We critically examine an evidence-bounded joint-afferent-motor unit framework in which abnormal afferent input from the diseased knee reduces effective neural drive through arthrogenic muscle inhibition (AMI). Persistent under-recruitment may be associated with altered motor-unit behavior and loading, impaired muscle quality, and greater reliance on compensatory reinnervation. We deliberately distinguish demonstrated human observations from provisional transitions and hypothesis-generating mechanistic extensions. Human evidence supports AMI and impaired muscle quality and provides preliminary cross-sectional evidence of altered motor-unit behavior; however, human studies have not established a temporal sequence from persistent AMI to motor-unit remodeling or denervation-reinnervation. Direct KOA-related neuromuscular junction (NMJ) evidence remains predominantly preclinical, and progressive NMJ degeneration has not been demonstrated in humans with KOA. Aging, sex, obesity, diabetes, systemic inflammation, pain sensitization, inactivity, and other comorbidities are treated as effect modifiers and competing explanations rather than proof of causation. We propose a testable, multimodal validation strategy combining joint imaging, standardized voluntary-activation testing, neurophysiology, high-density electromyography, motor-unit-number estimation, muscle imaging, and, when justified, tissue-level NMJ phenotyping. For older adults, the practical implication is mechanism-directed care: restore joint-related activation when inhibition dominates, use neural augmentation to enable adequate loading, address muscle-quality and metabolic constraints when present, and reserve NMJ-directed interventions for future human subgroups defined by convergent structural and physiological evidence.

Related Concept Videos
 01:13
Motor Units
Motor units come in different sizes, with smaller units...
 00:46
Motor Units
 01:19
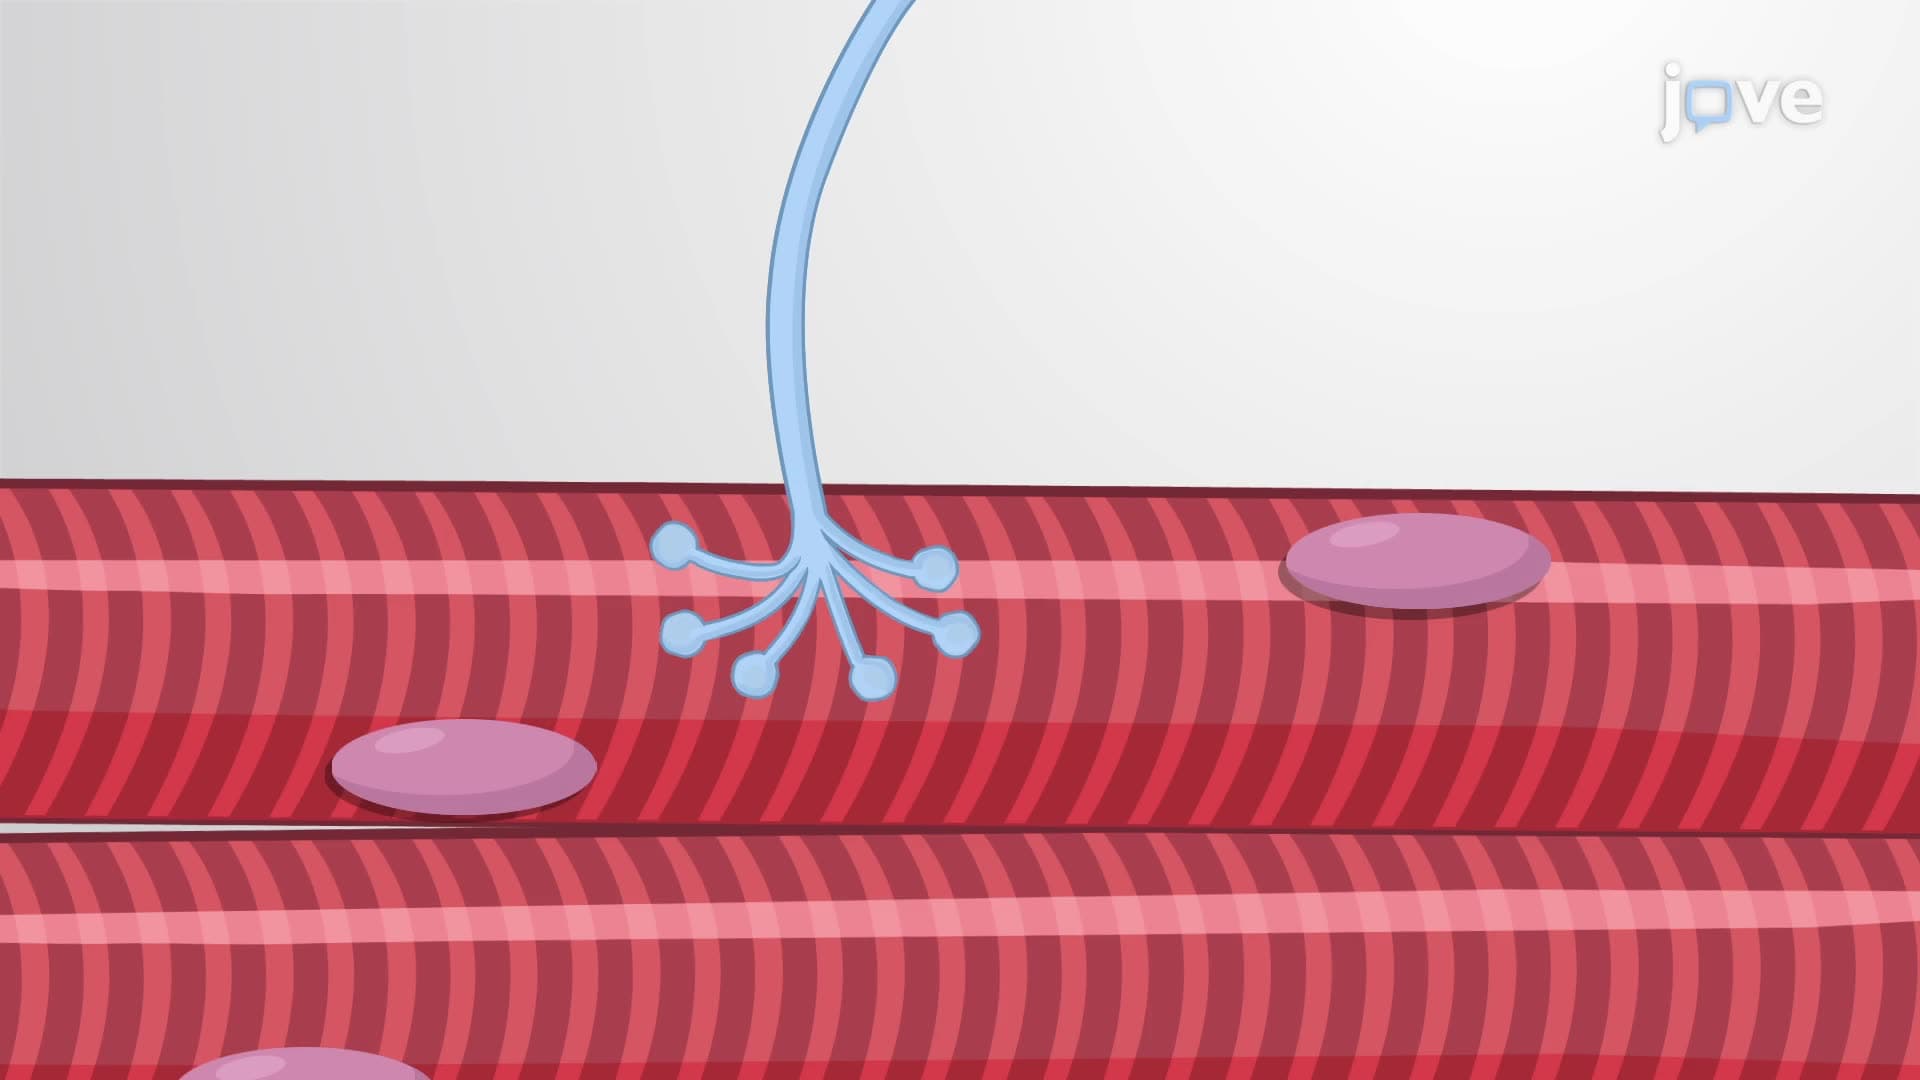
The Neuromuscular Junction
 01:23
Knee Joint
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris group...
 01:12
Alterations in Muscle Tone ll
 01:07
Development of the Limb Synovial Joints
The mesenchymal stem cells differentiate into chondrocytes that form the hyaline cartilage, and later the cartilaginous model of the bone. This model further transforms into a bone. This process is known as endochondral ossification.
During development, the limbs...