Vitamin supplementation and Alzheimer's disease: what the evidence shows
Related Experiment Video
Updated: Oct 31, 2026

Operation Procedure and Precautions of Thread-Embedding Acupuncture Therapy in Alzheimer
Published on: May 10, 2024
Lauren Gordon1, Ece Buyuksandalyaci Tunc2, Leah Vaikutis1
1Division of Geriatric Psychiatry, Department of Psychiatry and Behavioral Neuroscience, Saint Louis University School of Medicine, St. Louis, MO, USA.

Abstract:
Alzheimer's disease (AD) is the most common cause of major neurocognitive disorder worldwide, with growing prevalence and limited disease-modifying treatment options. Vitamin supplementation has attracted considerable interest as a potentially modifiable strategy in AD because several vitamins are involved in biological pathways implicated in AD pathogenesis, including oxidative stress, neuroinflammation, and homocysteine metabolism. However, the clinical relevance of these mechanistic associations remains uncertain, and findings from interventional studies have been inconsistent. This narrative review critically evaluates the current evidence regarding vitamin supplementation across the AD spectrum, including associations between vitamin deficiency and AD risk, the potential role of supplementation in AD prevention, and cognitive or functional outcomes among individuals with mild cognitive impairment or established AD. Among the vitamins reviewed, folic acid and vitamin B12 demonstrate the most consistent, although still limited, signal for potential cognitive benefit, particularly when used in combination although whether this benefit is concentrated among individuals with elevated homocysteine levels remains uncertain. Vitamin D deficiency has been relatively consistently associated with increased AD risk in observational studies, supporting consideration of vitamin D assessment and correction of documented deficiency as part of routine clinical care in older adults. Evidence for vitamin E suggests possible attenuation of functional decline at higher doses but does not support routine use for cognitive benefit or AD prevention. For vitamins A, C, thiamine, and niacin, clinical evidence remains sparse, indirect, and insufficient to support supplementation beyond correction of documented deficiencies. Overall, biological plausibility has consistently outpaced demonstrated clinical efficacy in vitamin literature. Vitamin supplementation should not be considered a disease-modifying intervention for AD; however, vitamin assessment, including baseline serum vitamin levels where clinically indicated, and supplementation should be individualized, with correction of documented deficiencies remaining appropriate for general health, particularly in older adults with poor intake, malabsorption risk, or medication-related deficiencies. Ensuring adequate B vitamin intake and correcting vitamin D deficiency when documented may be incorporated into a broader brain-health strategy alongside pharmacologic treatments and lifestyle interventions. Future research should prioritize adequately powered clinical trials with standardized outcomes, longer follow-up periods, and stratification by baseline nutritional status.
Related Concept Videos
 01:22
Alzheimer's Disease: Treatment
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:29
Alzheimer Disease l: Introduction
 01:23
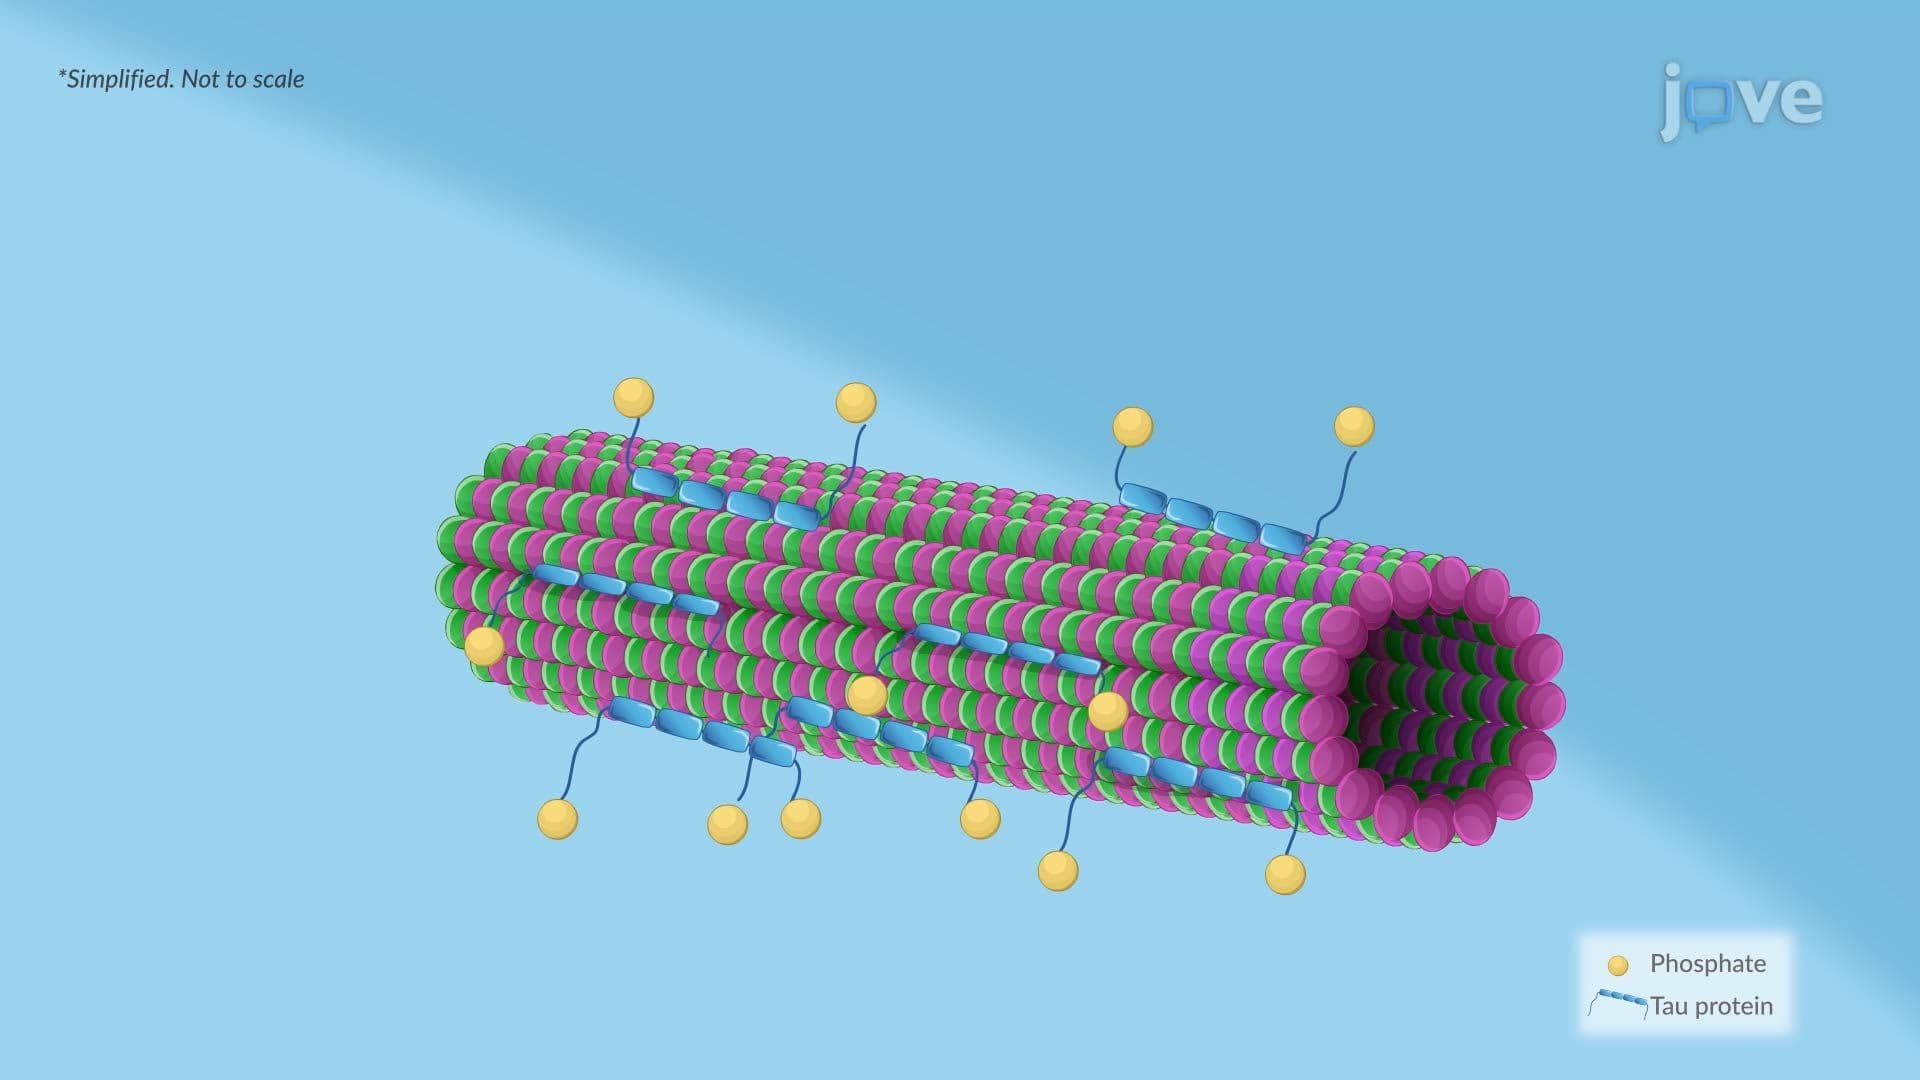
Alzheimer Disease ll: Pathophysiology
 01:30
Vitamins
 01:30
Cognitive Enhancers: Cholinesterase Inhibitors and NMDA Receptor Antagonists