Group A streptococcus vaccine strategies: virulence targets, resistance constraints and complementary control measures
Related Experiment Video
Updated: Oct 31, 2026
A Murine Model of Group B Streptococcus Vaginal Colonization
Published on: November 16, 2016
Manisha Agarwal1, Ankita Khataniar1, Sanchaita Rajkhowa2
1Centre for Biotechnology and Bioinformatics, Dibrugarh University, Dibrugarh, Assam, 786004, India.

Abstract:
Group A Streptococcus (GAS), or Streptococcus pyogenes, causes a connected spectrum of pharyngeal, cutaneous, invasive and immune-mediated diseases. Although beta-lactams remain active, treatment alone has not controlled transmission, recurrent infection, rapid invasive progression or acute rheumatic fever and rheumatic heart disease. Control is further weakened by increased macrolide and clindamycin resistance, heterogeneous diagnostic access, asymptomatic carriage, crowded living conditions and unreliable continuity of secondary prophylaxis. These limitations have shifted the field from a predominantly treatment-centered approach toward the development of vaccines as a prevention strategy. Target selection is guided by virulence functions that are required for colonization, immune evasion and tissue injury. These include the M protein, group A carbohydrate (GAC), streptolysin O, Streptococcus pyogenes cell envelope protease (SpyCEP), Streptococcus pyogenes adhesion and division protein (SpyAD), C5a peptidase and other conserved surface or secreted antigens. Current strategies include multivalent type-specific M-protein vaccines, conserved M-protein peptide vaccines, glycoconjugates, multicomponent non-M-protein formulations and mRNA-lipid nanoparticle platforms. The clinical pipeline has recently broadened. Phase I studies have been completed for StreptAnova and MJ8VAX, whereas the J8-K4S2 and p*17-K4S2 clinical trial studies have been completed, with peer-reviewed results pending. The GSK four-component vaccine initiated phase I evaluation in 2025 and remained under clinical evaluation in 2026, whereas the VAX-A1 formulation entered a first-in-human phase I study in 2026. However, no licensed GAS vaccine is available. Progress remains constrained by uncertain correlates of protection, autoimmune safety requirements, geographical emm diversity, endpoint selection and the need for trials in high-burden populations. This narrative review therefore focuses on the disease problem, targetable virulence mechanisms, limits of antimicrobial control, current vaccine pipeline and interventions required to complement future vaccine use.
More Related Videos
 11:32
Following in Real Time the Impact of Pneumococcal Virulence Factors in an Acute Mouse Pneumonia Model Using Bioluminescent Bacteria
Published on: February 23, 2014
 09:25
Implementation of a Permeable Membrane Insert-based Infection System to Study the Effects of Secreted Bacterial Toxins on Mammalian Host Cells
Published on: August 19, 2016
Related Concept Videos
 01:28
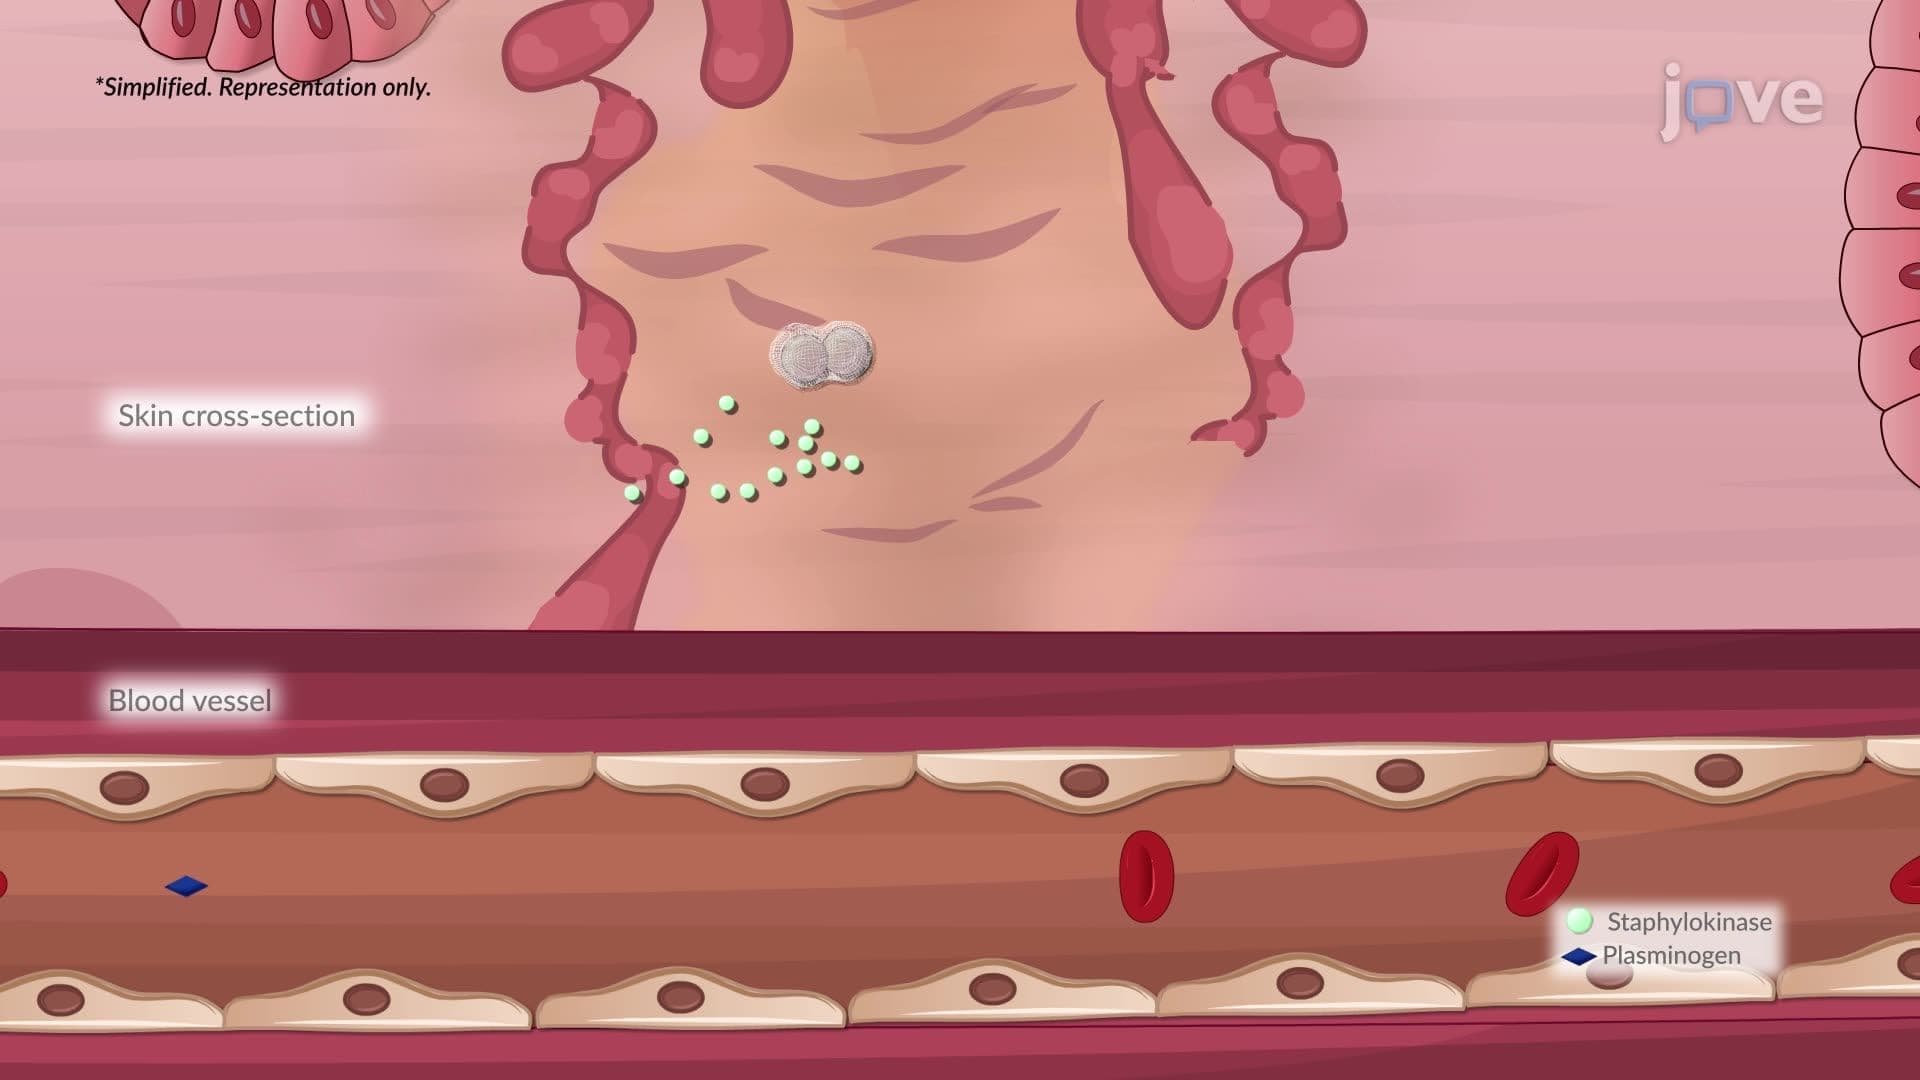
Regulation of Bacterial Virulence
 01:20
Determinants of Bacterial Pathogenicity and Virulence
 01:27
Streptococcal Pharyngitis
 01:25
Clinical Significance of Antibiotic Resistance
 01:24
Smallpox
 01:25
Mechanism of Antibiotic Resistance in MRSA