Dose deposition characteristics in theoretical 4π and clinical limiting 2π geometry: A proof of concept and potential implications for dose escalation
Related Experiment Video
Updated: Oct 31, 2026

Positron Emission Tomography-based Dose Painting Radiation Therapy in a Glioblastoma Rat Model using the Small Animal Radiation Research Platform
Published on: March 24, 2022
Biplab Sarkar1,2, Anirudh Pradhan3
1Department of Radiation Oncology, Apollo Multispeciality Hospitals, Kolkata, West Bengal, India.

Aim:
To evaluate the characteristic of the dose, fall inside and outside the stereotactic radiotherapy in theoretical 4π and clinical limiting 2π geometry. This will allow dose escalation to the target volume, without affecting dose falloff to the organs at risk. A total of 50 patients were evaluated in this study.
Materials And Methods:
Theoretical and clinical models were used to evaluate the dose falloff characteristics. In the theoretical model, targets with diameters of 0.5 cm, 1 cm, 2 cm, and 3 cm were placed inside a 10 cm diameter body/external contour. Dose escalation was 120%, 150%, and 200% at the core. Dose falloff characteristics for the "external contour" were determined. In the clinical model, 30 SRS patients were planned for uniform, 120%, 150%, and 200% doses to the core. Dose falloff at the external contour and variation in OAR doses were evaluated.
Results:
In the theoretical model, the maximum escalated dose was 181.6%. The characteristic dose falloff was a parabolic function, and there was little change in the spillage dose. Average spillage dose for 0.5 cm, 1 cm, 2 cm, and 3 cm targets was 0.4 ± 0.5%, 1.3 ± 1.9%, 1.5 ± 2.0%, and 0.8 ± 0.8%, respectively. Statistical comparison between uniform and escalated plans was performed using paired t-tests and Cohen's d effect size. For the clinical model, the maximum dose was 213.9%. Maximum dose differences Δ (120%-uniform), Δ (150%-uniform), and Δ (200%-uniform) for the brainstem were 1.3 ± 3%, 2.5 ± 5%, and 5.4 ± 13%. For the chiasm 0.4 ± 0.9%, 0.3 ± 0.9%, and 0.3 ± 1.0%. Left and right optic nerve, they were 0.3 ± 0.6%, 0.2 ± 0.4%, 0.7 ± 0.7%, and 0.0 ± 0.8%, -0.2 ± 1.8%, and -0.1 ± 1.4%.
Conclusion:
Dose at the center of the target can be increased, creating a heterogeneous dose distribution without affecting the OAR and spillage doses until target dose coverage remains constant. This property of dose distribution may be helpful in dose escalation for the resistant hypoxic targets. The study also suggests relevance to EUD/TCP modeling for hypoxic tumor escalation in SRS/SRT.
More Related Videos

Related Concept Videos
 01:21
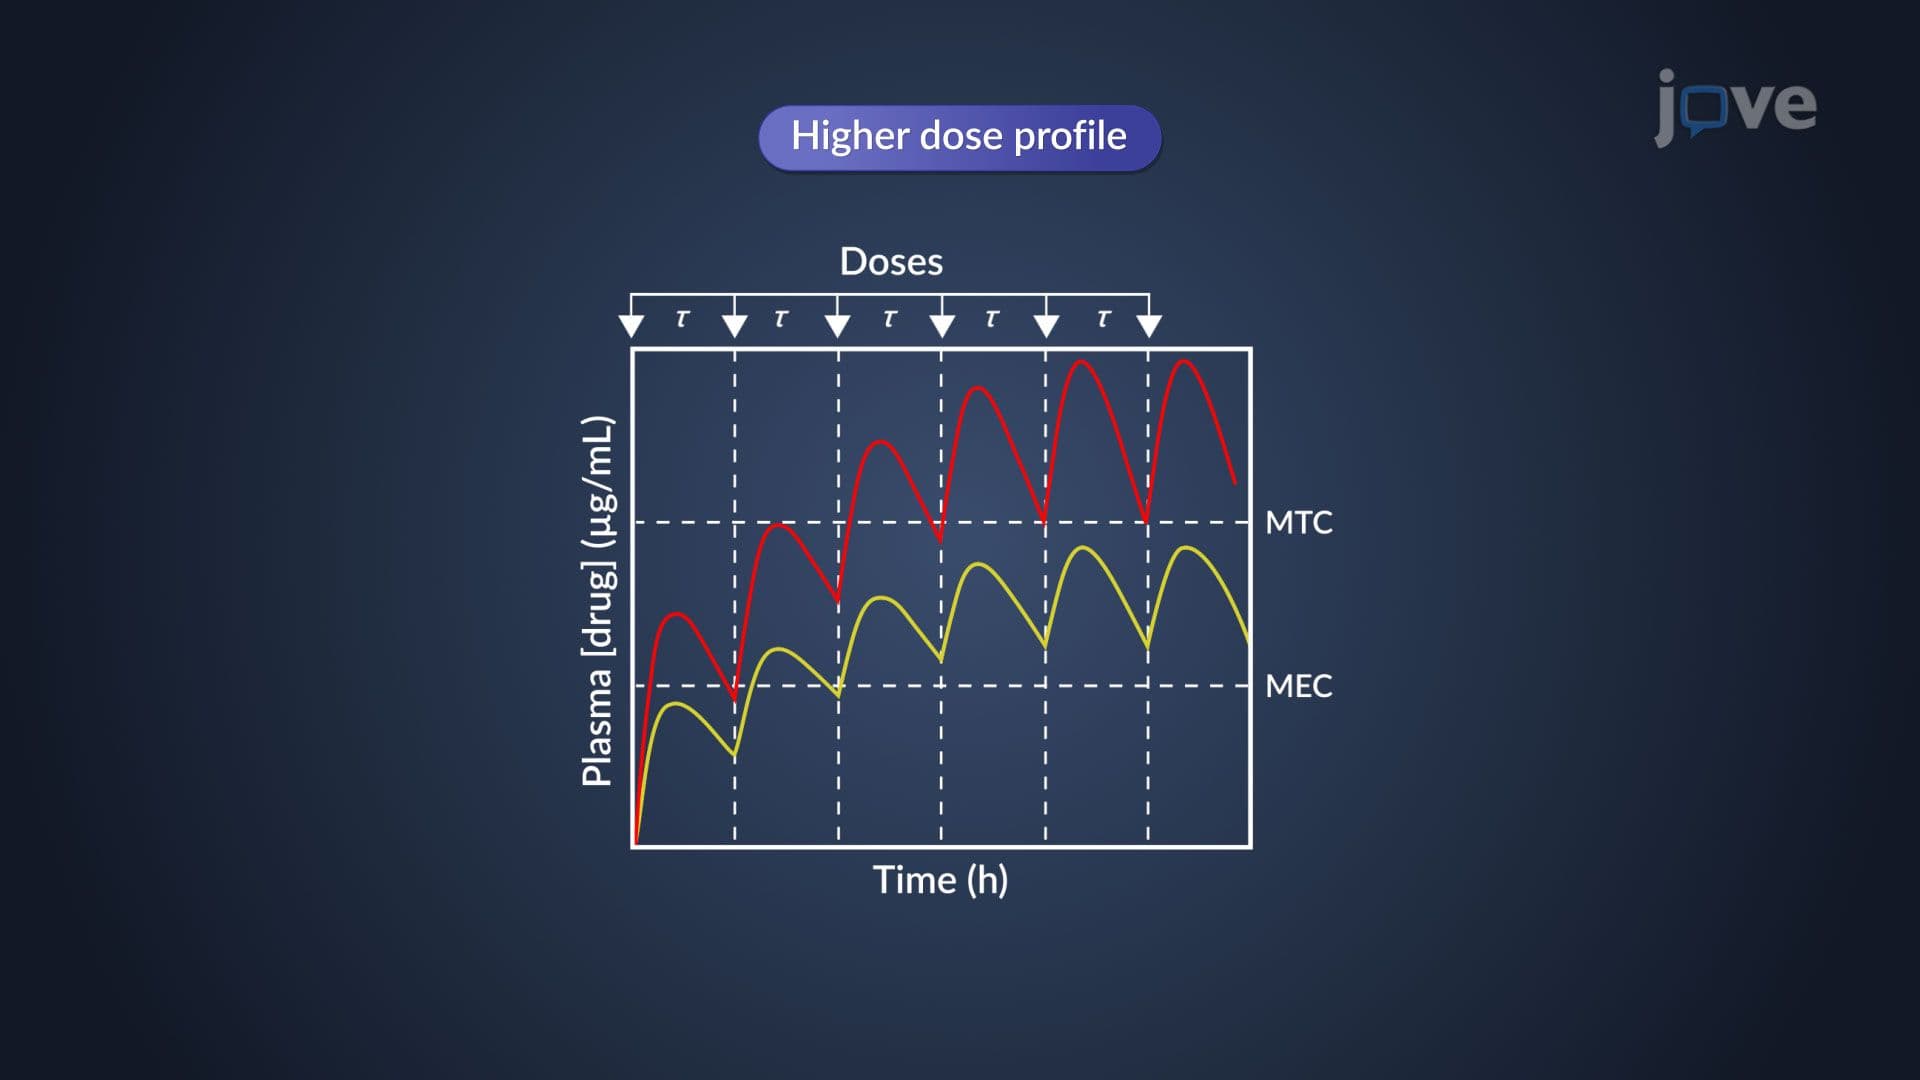
Dose Size and Dosing Frequency: Determination Methods
 01:21
Drug Accumulation During Multiple Dosing: Repetitive IV Injections
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
 01:03
Dose-Response Relationship: Overview
 01:21
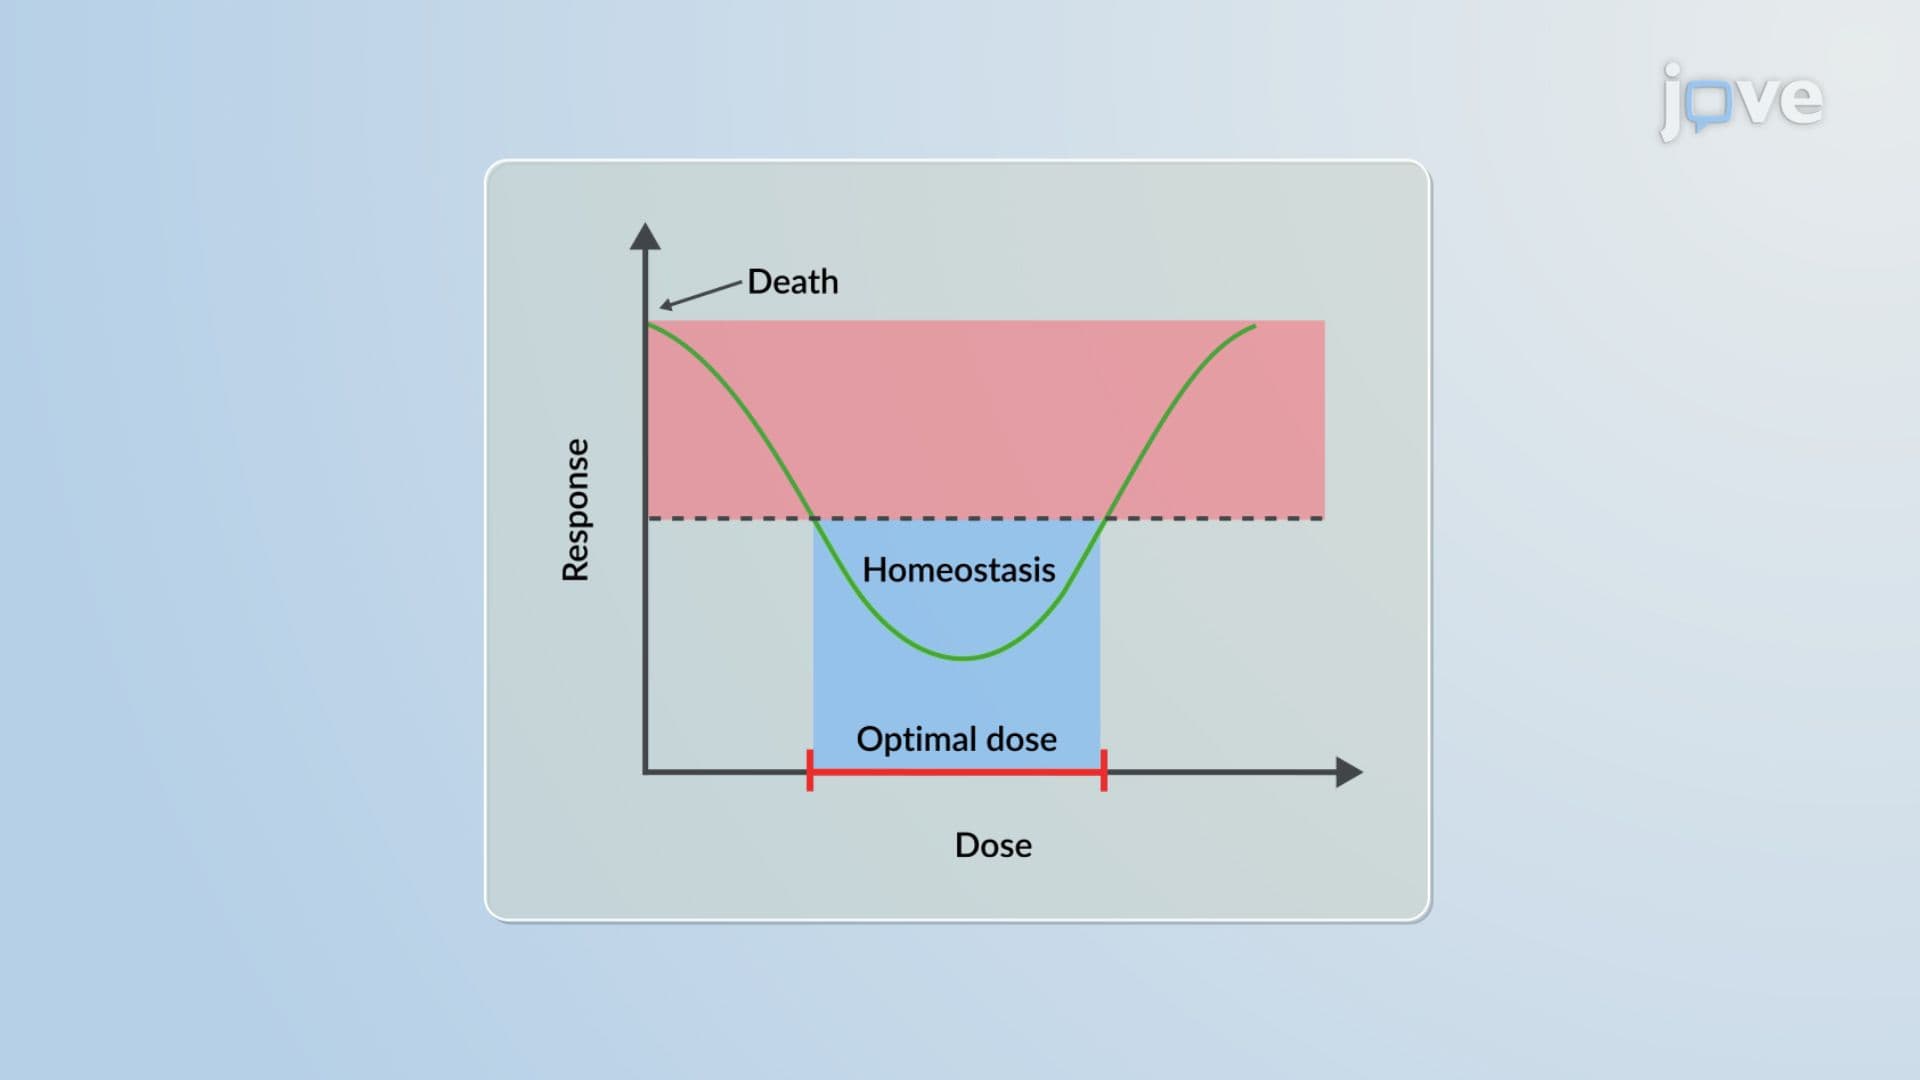
Dose Response Curve: Conventional Versus Nonmonotonic
 01:25
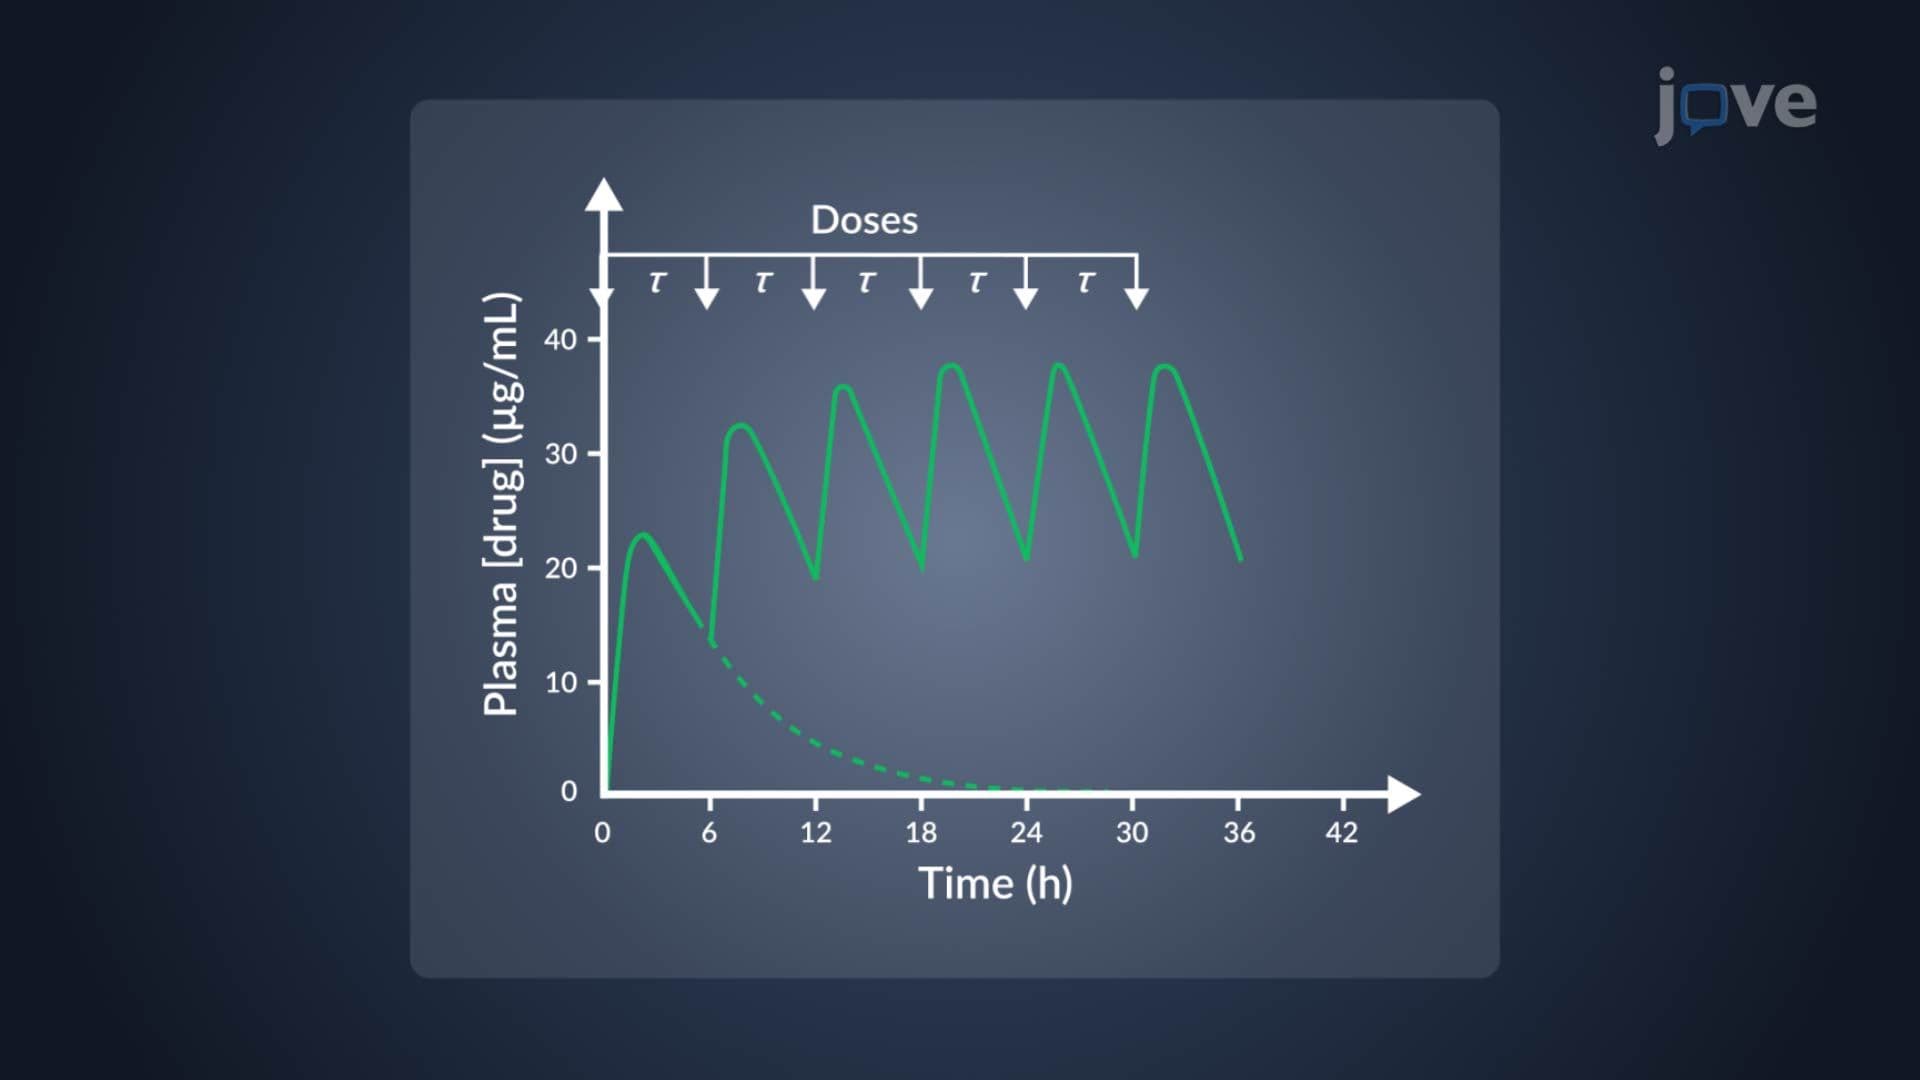
Dosage Regimen: Multiple Oral Dosage