Drivers of Increased Resource Utilization After Removal of Donation Service Area in Lung Transplant
Related Experiment Video
Updated: Oct 31, 2026
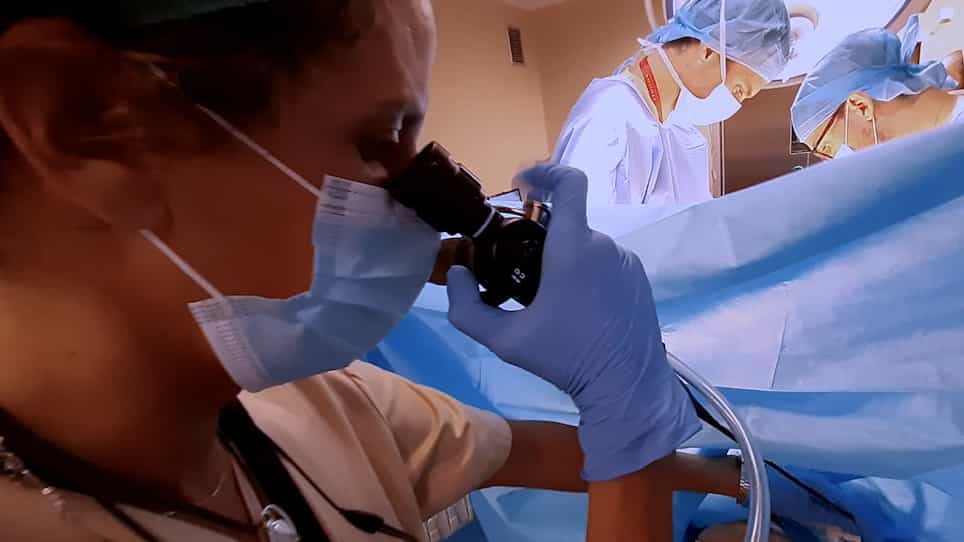
Lung Rapid Recovery Procurement Combined with Abdominal Normothermic Regional Perfusion in Controlled Donation after Circulatory Death
Published on: August 15, 2022
Andrew Kalra1, Leon Fan2, Shi Nan Feng2
1Division of Thoracic Surgery, Johns Hopkins University School of Medicine, Baltimore, Maryland; Division of Cardiac Surgery, Keck Hospital of the University of Southern California, Los Angeles, California.

Introduction:
The removal of donation service area (DSA)-based allocation increased lung transplants (LTs) and transplant hospitalization costs nationally. Regional differences in resource utilization for LT recipients have been identified; however, the specific clinical drivers remain unclear. These findings may inform evaluation of the current Composite Allocation Score system.
Methods:
We studied adult (≥18 y) LT recipients in the National Inpatient Sample in regions with previously increased resource utilization. Cochrane-Armitage was used to evaluate trends in hospital procedures in the DSA (8/2015-10/2017) versus non-DSA (12/2017-2/2020) eras. Multivariable generalized linear regression identified recipient factors associated with hospitalization costs and length of stay.
Results:
We identified 4870 DSA era and 4045 non-DSA era LT recipients. Over our study period time, we observed increases in the percentage of recipients requiring extracorporeal membrane oxygenation (ECMO) (14%-36%), mechanical ventilation <24 h (5%-10%), and dialysis (4%-5%; all P ≤ 0.01), while fewer recipients required tracheostomy (38%-26% P = 0.007). After adjustment, length of stay was significantly longer among recipients with prolonged mechanical ventilation (+25 d, 95% CI = 17-33, P < 0.001), tracheostomy (+17 d, 95% CI = 12-21, P < 0.001), ECMO (+8 d, 95% CI = 3-13, P = 0.003), bilateral LT (relative to single LT, +4 d, 95% CI = 1-7, P = 0.048), and higher Charlson Comorbidity Index (+2 d, 95% CI = 1-4, P < 0.001). Hospitalization costs were significantly higher among recipients with prolonged mechanical ventilation (+$152,992, 95% CI = $100,510-$205,473), dialysis (+$119,614, 95% CI = $27,305-$211,923), ECMO (+$113,690, 95% CI = $72,423-$154,957), tracheostomy (+$104,864, 95% CI = $78,887-$130,841), bilateral LT (+$28,829, 95% CI = $6560-$51,098), and higher Charlson Comorbidity Index (+$13,729, 95% CI = $4155-$23,304; all P ≤ 0.01).
Conclusions:
Factors associated with increased resource utilization post-DSA included mechanical ventilation, dialysis, and tracheostomy during hospitalization, ECMO, bilateral LT, and comorbidities.
Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:16
Kidney Transplant III: Nursing Management
 01:26
Kidney Transplant II: Surgical Procedure