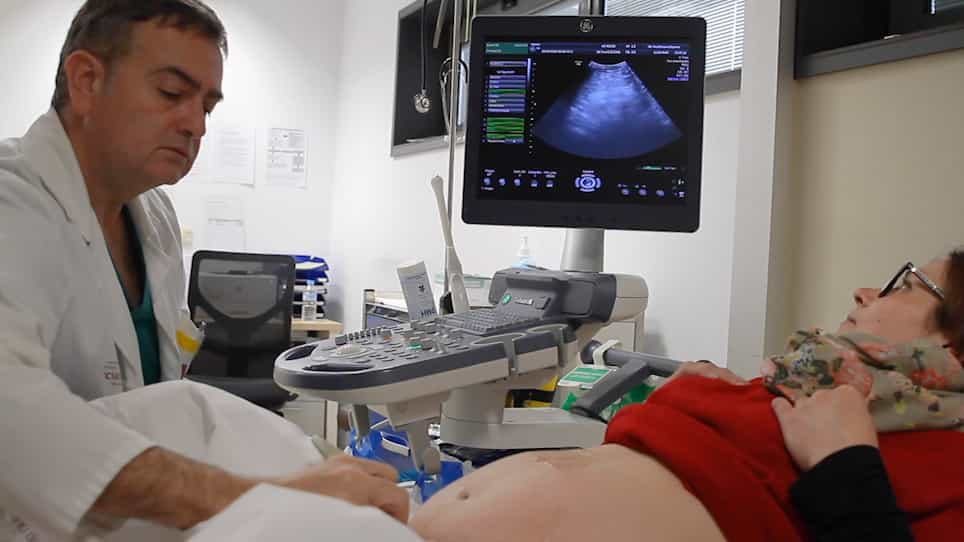
Association of Team Huddles with Reduced Nulliparous, Term, Singleton, Vertex Cesarean Rates
Related Experiment Video
Updated: Oct 31, 2026
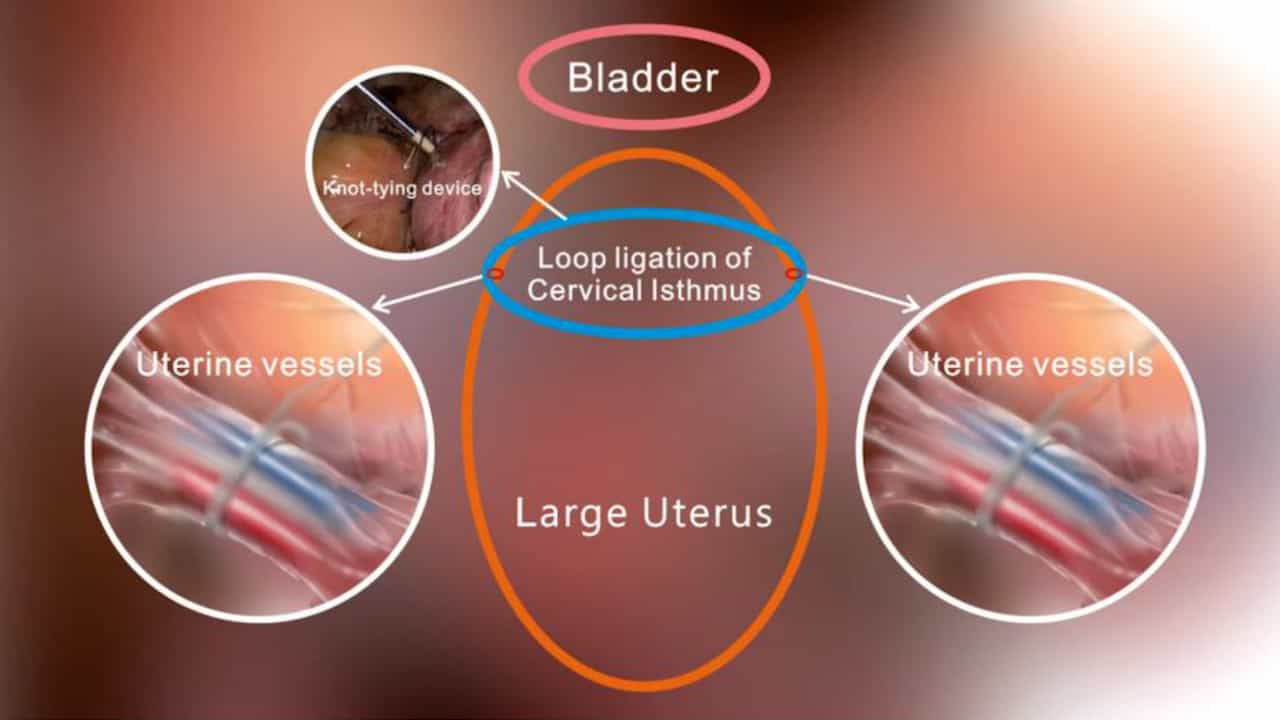
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Elizabeth Stiles1, Samantha Keller1, Ashley S Roman1
1NYU Grossman School of Medicine, Department of Obstetrics and Gynecology, New York, United States, New York.

Abstract:
Objective To evaluate whether structured multidisciplinary team huddles with standardized indication documentation before unscheduled Cesarean delivery (CD) were associated with changes in nulliparous, term, singleton, vertex (NTSV) CD rates. Study Design This retrospective cohort study included 2,051 NTSV deliveries from a single faculty practice at a large urban academic medical center from September 1, 2023, to June 30, 2025. A structured team huddle intervention requiring a standardized paper form before unscheduled, nonelective CD was implemented October 1, 2024. Patients were categorized into preintervention (N = 1,160), transition (N = 46), intervention (N = 606), and postintervention (N = 239) periods by delivery date. The primary outcome was NTSV CD rate by period. Secondary outcomes included CD indication, labor and delivery characteristics, maternal and neonatal outcomes, and compliance. Categorical variables were compared using chi-square tests, and continuous variables were compared using independent-samples t tests or analysis of variance. Results CD rates differed significantly across the preintervention, intervention, and postintervention periods (34.9% [405/1,160], 28.9% [175/606], and 32.6% [78/239], respectively; P = .037). The odds of CD were lower during the intervention period versus preintervention (odds ratio 0.76, 95% confidence interval 0.61-0.94). Among 228 eligible unscheduled, nonelective CDs, form completion differed significantly by period (33.3% [5/15] transition, 42.6% [63/148] intervention, 0% [0/65] postintervention; P < .001). Maternal and neonatal outcomes were similar across periods. Among completed forms, partial or no agreement between form- and chart-documented indications occurred in 36.8% (25/68). Conclusion A structured multidisciplinary team huddle before CD was associated with reduced CD rates without adverse maternal or neonatal outcomes. The effect was not sustained after discontinuation of the intervention. These findings suggest real-time, team-based clinical decision support may be an effective, low-cost strategy to reduce potentially avoidable CDs.