Surgical Procedure and Postoperative S-1 Chemotherapy Deliverability in Symptomatic Stage IV Gastric Cancer
Related Experiment Video
Updated: Oct 31, 2026
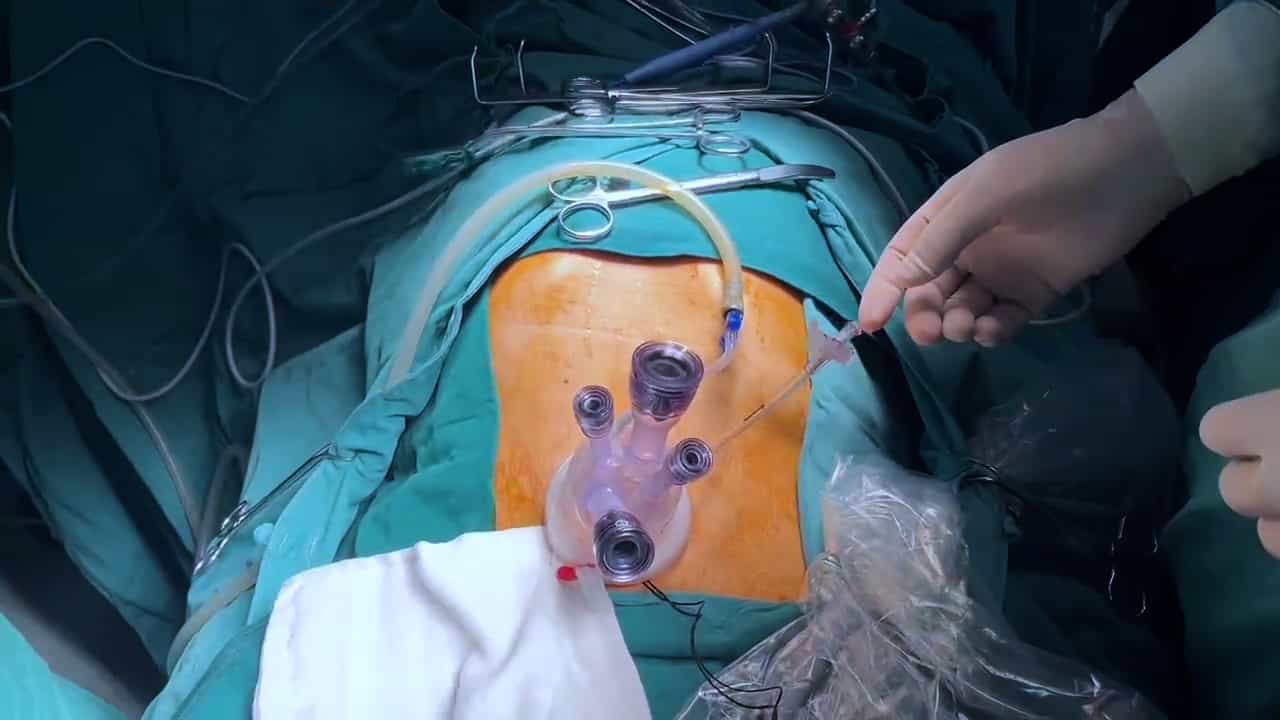
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
Kazuya Higashizono1,2, Masaya Watanabe3, Erina Nagai3
1Department of Gastroenterological Surgery, Shizuoka General Hospital, Shizuoka, Japan; sougou-soumu@shizuoka-pho.jp.

Background/Aim:
Symptomatic incurable stage IV gastric cancer (GC) may require palliative surgery for bleeding or obstruction before systemic therapy. We examined whether procedure type-distal gastrectomy (DG), total gastrectomy (TG), or gastrojejunostomy (GJ)-is associated with nutritional/inflammatory changes, S-1 deliverability, and overall survival (OS).
Patients And Methods:
We retrospectively studied 49 patients who underwent palliative DG (n=13), TG (n=20), or GJ (n=16) and then received S-1 as first-line postoperative chemotherapy. Body weight, prognostic nutritional index (PNI), and neutrophil-to-lymphocyte ratio (NLR) were assessed preoperatively and before chemotherapy. Deliverability was evaluated by time to S-1 initiation, continuation beyond 3 months, and treatment modification within 3 months. OS was analyzed using Kaplan-Meier and Cox models.
Results:
Postoperative complications were more frequent after GJ (p=0.002); time to S-1 initiation was similar among groups (p=0.144). S-1 continuation beyond 3 months was achieved in 29/49 patients (59.2%; DG 76.9%, TG 55.0%, GJ 50.0%; p=0.302). Weight loss was significantly greater after TG than after DG or GJ, and GJ showed a postoperative decline in PNI and a significantly higher pre-chemotherapy NLR than DG and TG (p=0.015 and p=0.036, respectively). Median OS was 474 days (DG: 812, TG: 422, and GJ: 293 days) and was significantly longer after DG than after TG (p=0.042) or GJ (p=0.003). In multivariate Cox analysis, chemotherapy for ≥3 months (HR=0.46, 95% CI=0.22-0.95; p=0.036) and high PNI (HR=0.31, 95% CI=0.13-0.77; p=0.012) were independent prognostic factors.
Conclusion:
In symptomatic incurable stage IV GC treated with palliative surgery followed by S-1, procedure type was associated with distinct perioperative profiles and OS. Maintaining chemotherapy and immuno-nutritional status may be clinically relevant in these patients.
Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...