Left ventricular geometry as a risk factor for recurrent subaortic stenosis after primary resection
Related Experiment Video
Updated: Oct 31, 2026
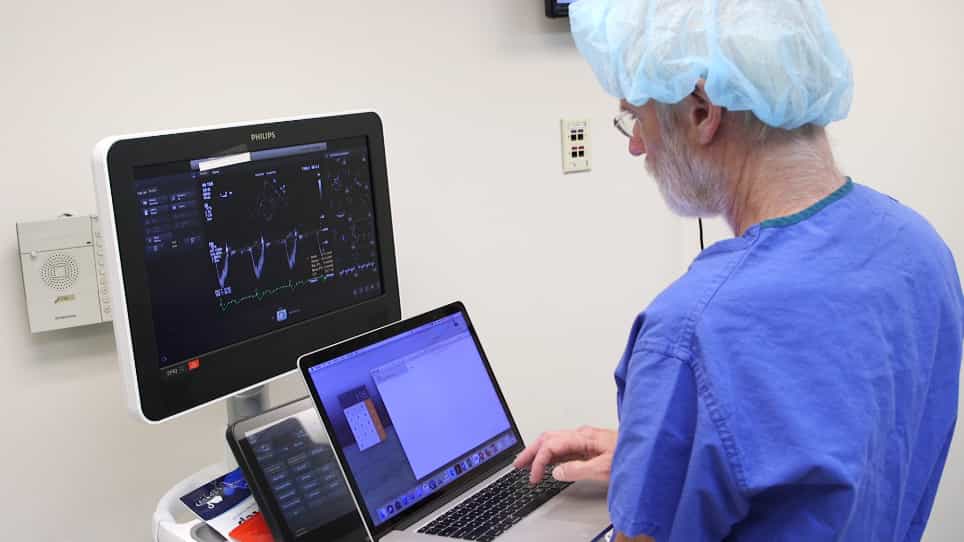
Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
Alaa Aman Felimban1,2,3, Heba Abdel-Ghafar Hessuin Mohamed1,2, Muna Ismail1,2,3
1Cardiac Sciences Department, King Abdulaziz Medical City, Ministry of National Guard-Health Affairs, Riyadh, Saudi Arabia.

Background:
Discrete subaortic stenosis is a progressive cause of left ventricular outflow tract obstruction in children, and recurrence after surgical resection is not uncommon. We evaluated echocardiographic and morphologic factors associated with reintervention after primary subaortic membrane resection.
Methods:
We conducted a single-centre retrospective cohort study of paediatric patients (0-14 years) who underwent primary surgical resection of subaortic membrane stenosis between 2002 and 2019. Demographic, clinical, and echocardiographic variables were compared between patients requiring reintervention and those requiring a single operation. Independent predictors were assessed using multivariable logistic regression.
Results:
Seventy-seven patients were included; 16 required reintervention and 61 did not. On univariate analysis, the reintervention group had higher preoperative left ventricular outflow tract peak and mean gradients and shorter membrane length. In multivariable analysis, shorter membrane length independently predicted reintervention (adjusted odds ratio 0.677 per 1-mm increase, 95% confidence interval 0.487-0.941; p = 0.020), as did higher preoperative left ventricular outflow tract peak gradient (adjusted odds ratio 1.066 per 1-mmHg increase, 95% confidence interval 1.023-1.111; p = 0.002). A smaller aorto-septal angle showed a trend towards increased risk but did not reach statistical significance (adjusted odds ratio 0.933, 95% confidence interval 0.866-1.005; p = 0.067). Aortic regurgitation was significantly worse at follow-up in patients requiring reintervention.
Conclusion:
Shorter subaortic membrane length and higher preoperative left ventricular outflow tract peak gradient were independent predictors of reintervention after primary resection. These findings may improve risk stratification and support closer echocardiographic surveillance of patients at increased risk of recurrence.

Related Concept Videos
 01:22
Mitral Stenosis I: Introduction
 01:25
Aortic Regurgitation III: Medical Management
 01:15
Aortic Regurgitation I: Introduction
 01:20
Mitral Regurgitation I: Introduction
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests