Radiologist-guided multimodal fusion network for differentiating parotid tumors on 3D non-contrast CT
Related Experiment Video
Updated: Oct 31, 2026
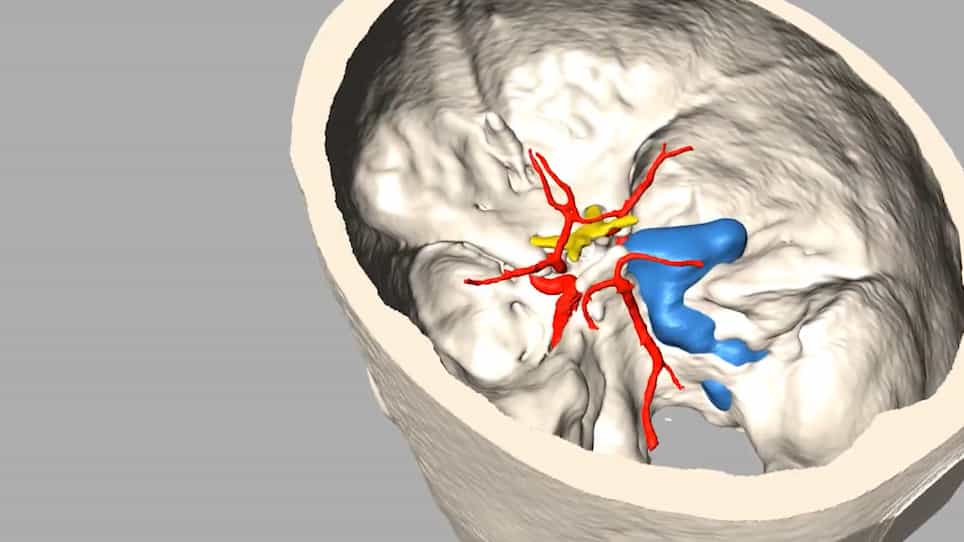
Multicolor 3D Printing of Complex Intracranial Tumors in Neurosurgery
Published on: January 11, 2020
Qin Yang1, Wenjun Liao2, Jianda Sun3
1Department of Radiation Oncology, Precision Radiation in Oncology Key Laboratory of Sichuan Province, Sichuan Clinical Research Center for Cancer, Sichuan Cancer Hospital & Institute, Sichuan Cancer Center, University of Electronic Science and Technology of China, Chengdu, China.

Objectives:
To improve the diagnostic accuracy of benign versus malignant parotid tumors using non-contrast CT. We propose a clinician-in-the-loop hybrid framework that mitigates low soft-tissue contrast by fusing semi-automated 3D visual features with expert semantic descriptors.
Methods:
This multi-center retrospective study analyzed non-contrast CTs from 367 patients. We developed AttenNet, a semi-automated model. First, an nnU-Net module automates 3D tumor segmentation, eliminating manual bounding boxes. A 3D-ResNet backbone then extracts volumetric features, which are dynamically fused with radiologist-provided semantic labels via a Multi-Head Cross-Attention Fusion (MHAF) mechanism. This allows the network to query visual morphology based on expert priors. Diagnostic performance and Gradient-weighted Class Activation Mapping (Grad-CAM) interpretability were evaluated.
Results:
The segmentation achieved a median Dice of 0.827. AttenNet (3D-ResNet) yielded an AUC of 0.908, significantly outperforming the image-only 3D-ResNet (AUC: 0.741) and expert-feature models (AUC: 0.821). External validation (n = 20) reached an AUC of 0.560-0.910.However, given the extremely small sample size, these results must be interpreted strictly as an exploratory proof-of-concept rather than definitive confirmation of generalizability. Grad-CAM confirmed that AttenNet highlights clinically essential geometric indicators-specifically tumor margins and internal heterogeneity-for differentiating malignancy, whereas single-modality baselines focused on background artifacts.
Conclusion:
This clinician-in-the-loop paradigm successfully integrates spatial imaging with expert reasoning. While multimodal fusion drove the primary performance gains, the MHAF mechanism provided enhanced spatial interpretability.