Stereotactic Radiosurgery for Trigeminal Neuralgia: A Comparison of Proximal and Distal Isocenter Outcomes
Related Experiment Video
Updated: Oct 31, 2026
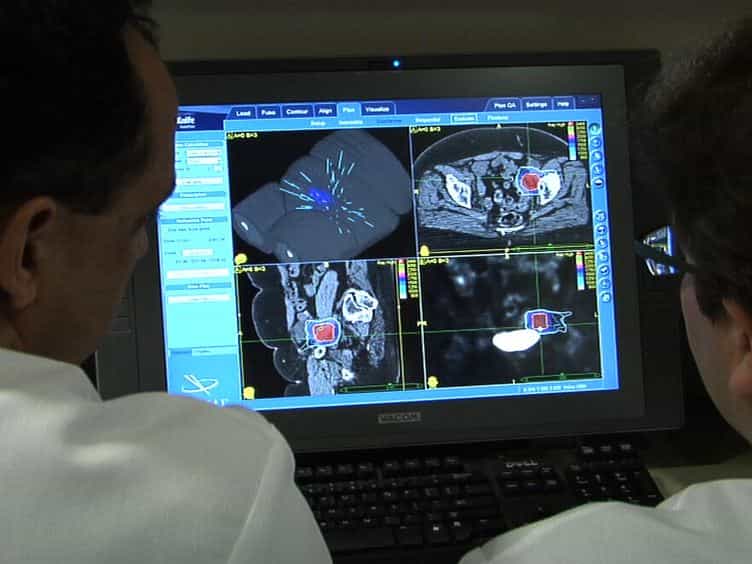
Stereotactic Radiosurgery for Gynecologic Cancer
Published on: April 17, 2012
Benjamin Hopkins1, David Qian2, Nicholis Boulis3
1Department of Radiation Oncology, Winship Cancer Institute of Emory University, Atlanta, Georgia.

Purpose:
Trigeminal neuralgia (TN) is a chronic neuropathic pain condition affecting the trigeminal nerve, with an incidence of approximately 4 to 5 per 100,000 persons annually, increasing to 20 per 100,000 after age 60 years, and a female-to-male ratio of approximately 3:2. Stereotactic radiosurgery (SRS) delivered by Gamma Knife or linear accelerators is a noninvasive alternative to surgical approaches for medically refractory cases. Although SRS for TN is commonly performed, consensus regarding optimal anatomic targeting remains lacking, with the 2 most common targets being the dorsal root entry zone (proximal) and the retrogasserian zone (distal). This study aimed to evaluate treatment outcomes in patients with TN treated with SRS based on proximal versus distal isocenter target locations.
Methods And Materials:
This multicenter retrospective analysis included patients treated for TN between 2017 and 2021 with Gamma Knife or linear accelerator-based SRS who were followed for at least 1 year. All patients received 85 Gy prescribed to the isocenter, located in either the dorsal root entry zone (proximal) or the retrogasserian zone (distal). Patient-reported pain relief was recorded as complete, partial, or absent. Duration of pain relief and medication de-escalation were also assessed. Outcomes were compared using the log-rank test and Cox proportional hazards analysis.
Results:
Eighty-six patients were included: 54 of 86 (63%) treated with proximal targeting (median age, 63 years; 72% women) and 32 of 86 (37%) with distal targeting (median age, 66 years; 71% women). Overall pain relief rates were 74% (proximal) and 90% (distal), although complete pain relief rates were 46% (proximal) and 31% (distal) (p = .011). Duration of pain relief did not differ significantly between groups (p = .18). Complete medication de-escalation was more frequent with proximal targeting (39% vs 13%), although partial de-escalation was more common with distal targeting (75% vs 33%) (P = .001).
Conclusions:
Both proximal and distal targeting approaches achieve high response rates for TN. Distal targeting may be associated with higher rates of any pain improvement, whereas proximal targeting may be associated with higher rates of complete pain relief and complete medication discontinuation. These findings are hypothesis-generating and warrant further investigation of efficacy and safety differences between these 2 approaches.