Long-term analgesic use after neuroma and upper limb nerve injury: patterns in Sweden
Related Experiment Video
Updated: Oct 31, 2026
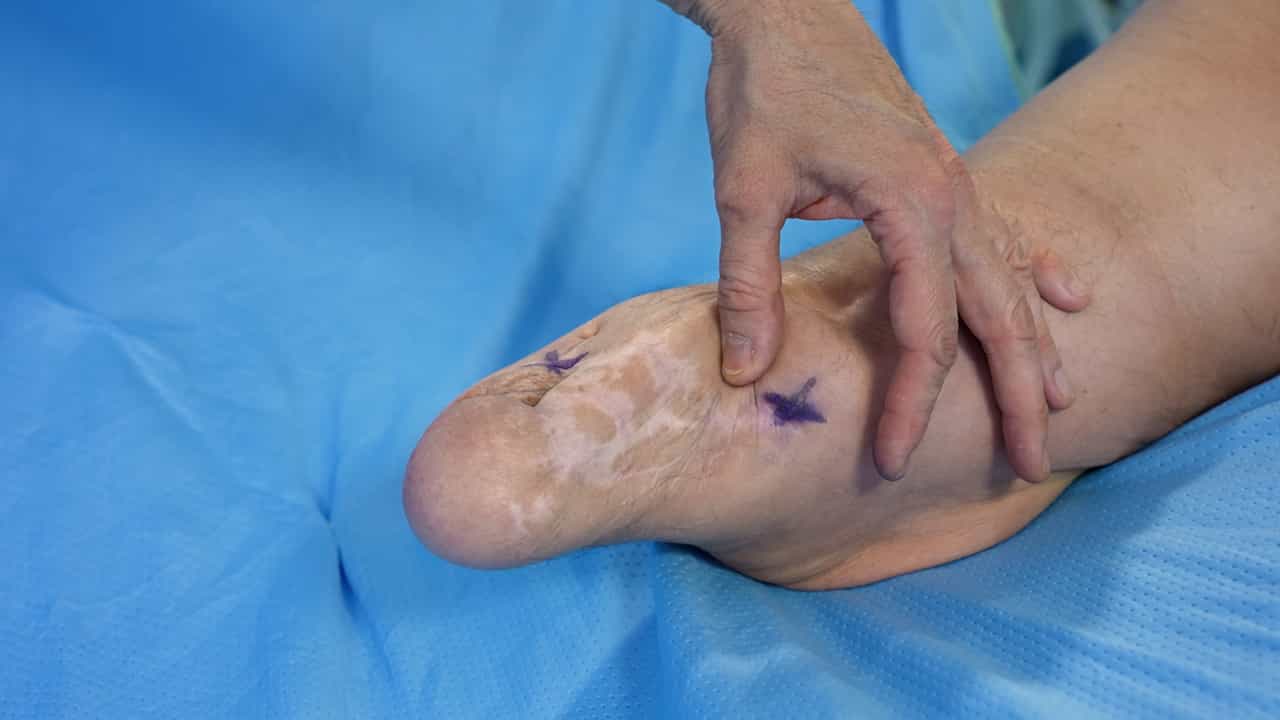
Targeted Muscle Reinnervation: Surgical Protocol for a Randomized Controlled Trial in Postamputation Pain
Published on: March 8, 2024
Emma Dahlin1,2, Raquel Perez1,3, Malin Zimmerman1,2
1Department of Translational Medicine-Hand Surgery, Lund University, Skåne University Hospital, Malmö, Sweden.

Objectives:
To examine demographic and socioeconomic differences in diagnosis and treatment of neuroma and nerve injury, assess risk of long-term use of centrally acting analgesics (CA-analgesics) compared with the general population, and describe how long-term use is distributed among individuals by demographic, socioeconomic, and treatment characteristics.
Methods:
In linked Swedish national registers (5,625,751 individuals, 25-80 years, residing 2010), incident cases of nonsurgically or surgically treated neuromas (n = 608' n = 189, respectively) or nerve injuries (n = 3,719, n = 2,122, respectively) were identified (no clinical data available) 2011 to 2014 and long-term CA-analgesic use was defined (prescription coverage ≥60% of days during 1 year; 60-day washout period after surgery). Multinomial and binary logistic regression models were used to estimate relative risks, adjusted for sex, age, income level, country of birth, and cohabiting. Absolute risks and absolute risk differences were calculated.
Results:
Neuroma or nerve injury cases were identified with variation in diagnosis and treatment by demographic and socioeconomic factors; women more likely to undergo neuroma surgery; men and younger individuals predominated among nerve injuries. All diagnostic treatment groups had markedly increased risks of long-term CA-analgesic use compared with the general population (adjusted relative risk range 3.5-6.0). Absolute risks among individuals exceeded 10% in socioeconomically disadvantaged subgroups (approximately 0.5% in the general population). Differences in long-term CA-analgesic use between nonsurgically and surgically treated individuals were modest.
Conclusions:
Neuroma and nerve injuries are associated with a substantial risk of long-term CA-analgesic use. Socioeconomic disadvantage strongly influences risk, whereas surgical treatment does not consistently reduce long-term medication use.
More Related Videos
 03:53
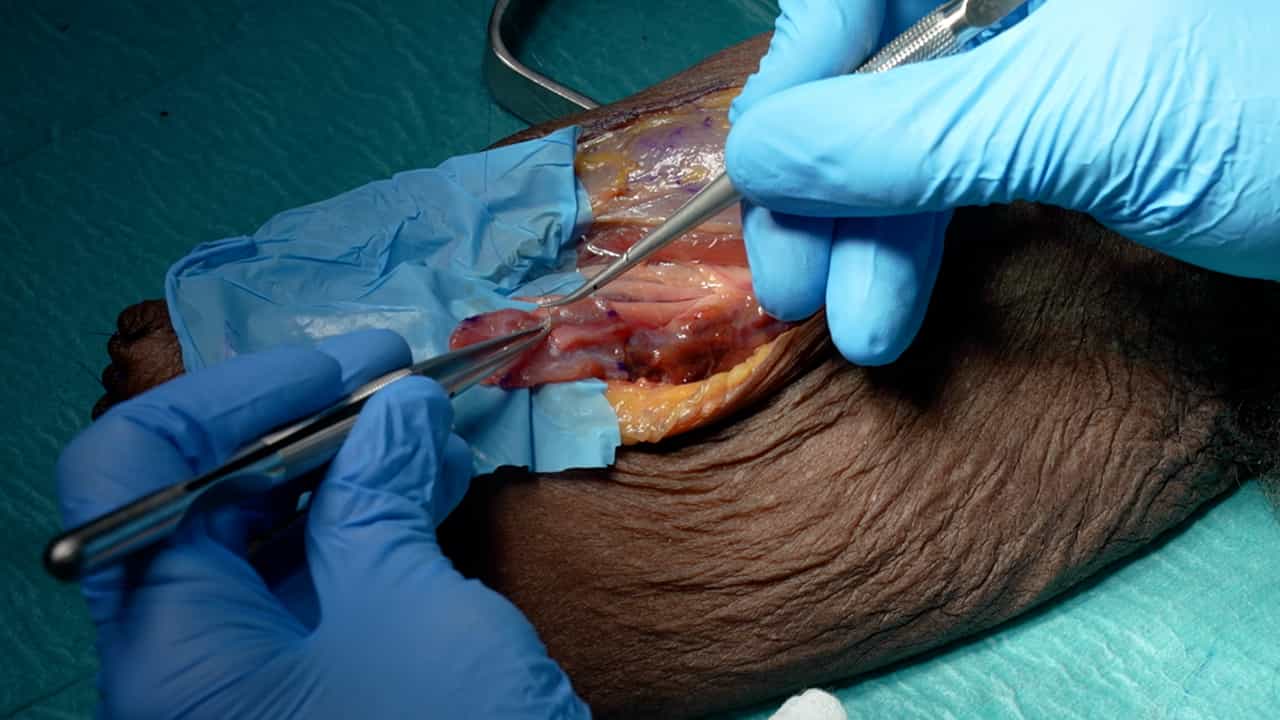
Regenerative Peripheral Nerve Interface: Surgical Protocol for a Randomized Controlled Trial in Postamputation Pain
Published on: March 15, 2024
 07:00
Novel Surgical Rodent Model for Studying Neuroma Pain Treatment Options using Targeted Muscle Reinnervation Through the Saphenous Nerve
Published on: November 14, 2025