Is the surgeon or hospital a larger cost driver for lumbar fusion? A hierarchical Bayesian approach using time-driven activity-based costing
Related Experiment Video
Updated: Nov 1, 2026
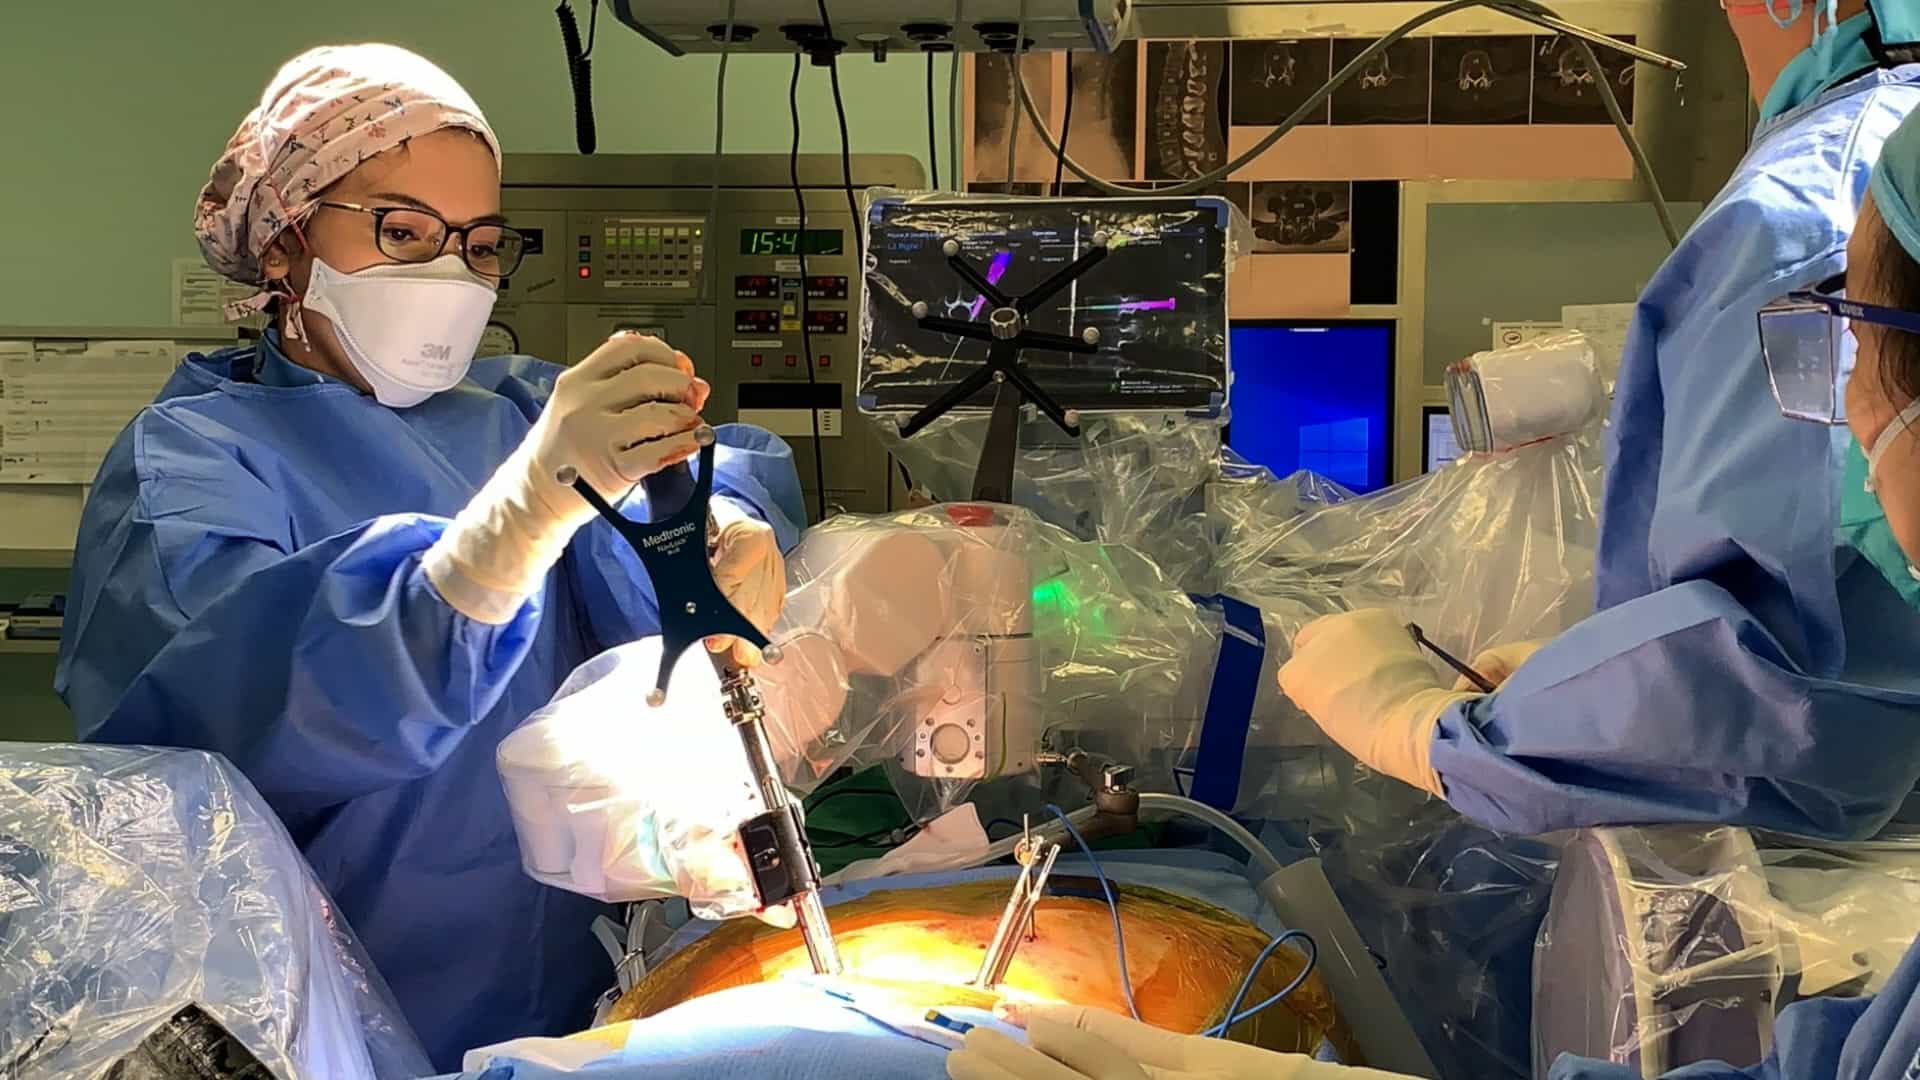
Three-dimensional Navigation-guided, Prone, Single-position, Lateral Lumbar Interbody Fusion Technique
Published on: July 15, 2021
Advith Sarikonda1,2, Danyal Quraishi1, Shaan Patel1
11Department of Neurological Surgery, Thomas Jefferson University, Philadelphia.

Objective:
Considerable variability exists in lumbar fusion outcomes, with prior studies demonstrating significant differences across both surgeons and hospitals. However, similar analyses for cost are lacking, making it unclear whether surgeons or hospitals are larger cost drivers for lumbar fusion, particularly in multihospital health systems. Therefore, the aim of this study was to perform a risk-adjusted time-driven activity-based costing (TDABC) analysis for single-level lumbar fusion to compare overall cost variance between surgeons and hospitals in a multihospital health system.
Methods:
This retrospective cohort study included single-level lumbar fusions performed (2020-2024) at a healthcare network encompassing several quaternary and community hospitals. TDABC was used to calculate the true intraoperative cost (not charges or reimbursement) of each case. Hierarchical Bayesian regression models were fit for total cost, and its primary drivers: supply cost and personnel cost. Random effects were specified for surgeon and hospital site, while fixed covariates included patient- and procedure-specific factors. Markov chain Monte Carlo sampling was performed to generate posterior draws for all model parameters, from which posterior medians and 95% Bayesian credible intervals (BCIs) were reported.
Results:
This analysis included 943 lumbar fusions performed by 23 surgeons across 9 hospitals. The mean total cost of surgery was $23,106 ± $10,475, driven by supplies (mean $20,344 ± $10,010) and personnel (mean $2755 ± $1019). Nonoverlapping BCIs demonstrated that between-surgeon variance was greater than between-site variance for both total cost and supply cost. Specifically, surgeon-level variance was 30-times greater than site-level variance for total cost (median 29.8, 95% BCI 1.4-10,756.4) and 53-times greater for supply cost (median 52.5, 95% BCI 2.0-28,374.7). Furthermore, for each 1 standard deviation difference between surgeons, there was a 29.9% (95% BCI 18.2-48.5) increase in total cost and a 35.2% (95% BCI 21.1-57.3) increase in supply cost, whereas comparable differences between sites were associated with only 5.5% (95% BCI 0.3-23.8) and 4.8% (95% BCI 0.2-23.4) increases in cost, respectively. In contrast, surgeon and site contributions were comparable for personnel cost, with overlapping BCIs.
Conclusions:
In cases of single-level lumbar fusions performed at a multihospital health system, variation in cost between surgeons was 30-times greater than variation between hospitals, although residual/unexplained variance was considerable. These hypothesis-generating findings might enhance physician awareness of cost drivers and practice heterogeneity. However, additional research is necessary to identify sources of unexplained variance, as well as to integrate costs with outcomes to determine whether cost variability represents value or waste.