Awake intubation in a Japanese tertiary emergency department: a single-center retrospective descriptive study
Related Experiment Video
Updated: Nov 1, 2026
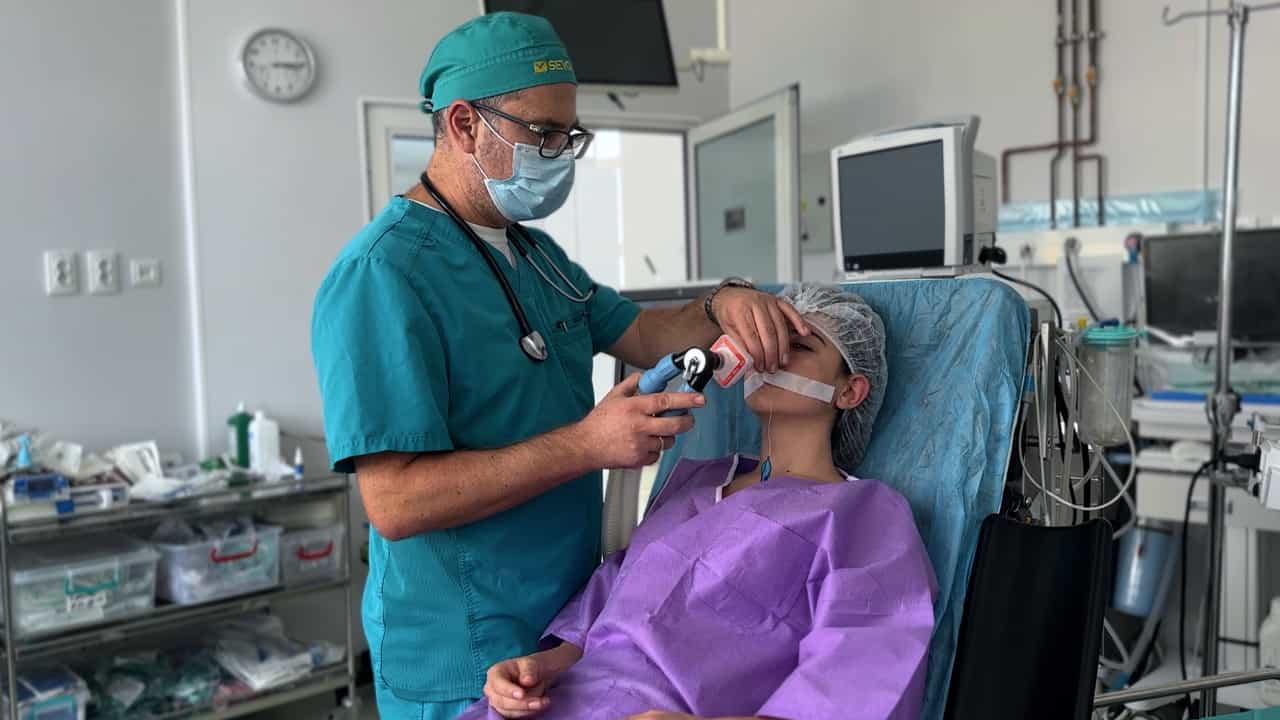
The Flexible Rhino-Laryngoscope for Awake Nasotracheal Intubation
Published on: August 2, 2024
Sayaka Nakahara1, Atsushi Yamamoto1, Akira Yamada1
1Emergency and Critical Care Center, Kurashiki Central Hospital, 1-1-1 Miwa, Kurashiki, Okayama, 710-8602, Japan.

Background:
Evidence on awake intubation in emergency departments (EDs) is limited. We aimed to describe patient characteristics, intubation indications, procedural practices, and outcomes for awake intubation in the ED.
Methods:
This single-center retrospective descriptive study included consecutive adult patients who underwent tracheal intubation at a tertiary ED in Japan from April 2020 through December 2025. Patients intubated during cardiac arrest were excluded. Operational definition for awake tracheal intubation required topical upper airway anesthesia, no neuromuscular blockers before or during the initial attempt, and documented preservation of consciousness and spontaneous ventilation throughout that attempt. Outcomes included first-pass success, adverse events related to airway management, and definitive airway management, including rescue.
Results:
Eighty-four patients underwent awake tracheal intubation, representing 5.5% of intubations in patients without cardiac arrest (84/1531). Upper airway infectious diseases were present in 54 patients (64.3%); airway-related indications accounted for 63 cases (75.0%). Emergency physicians performed 79 initial attempts (94.0%); a flexible bronchoscope was used initially in 49 patients (58.3%). First-pass success occurred in 63 patients (75.0%; 95% confidence interval, 64.4%-83.8%). Seven patients (8.3%) experienced adverse events related to airway management. Eighty patients (95.2%) achieved definitive airway management without a surgical airway. Four patients (4.8%) required a surgical airway, all after first-pass failure.
Conclusions:
Awake intubation, performed primarily by emergency physicians, was used to manage upper airway infectious diseases with actual or impending obstruction in a tertiary ED. A flexible bronchoscope was used initially in over half of cases and most patients were intubated without a surgical airway.

Related Concept Videos
 01:15
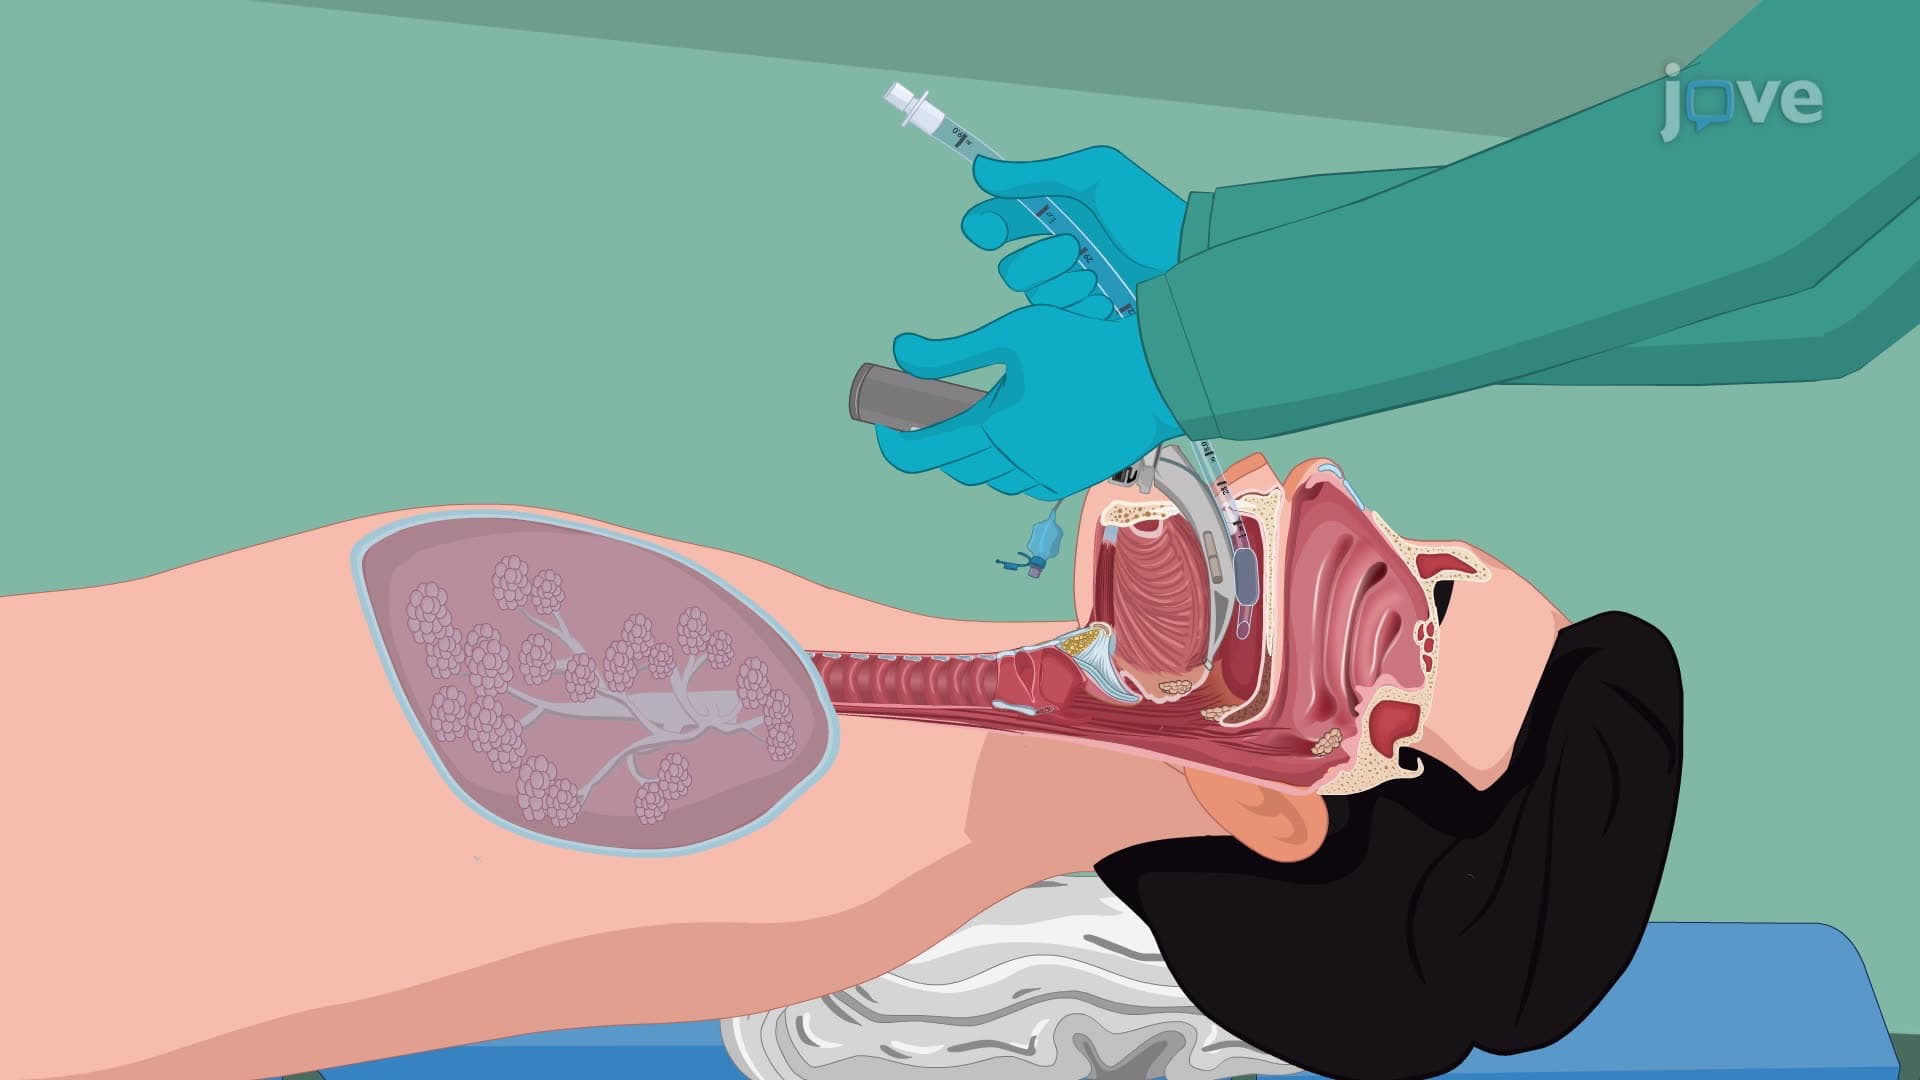
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
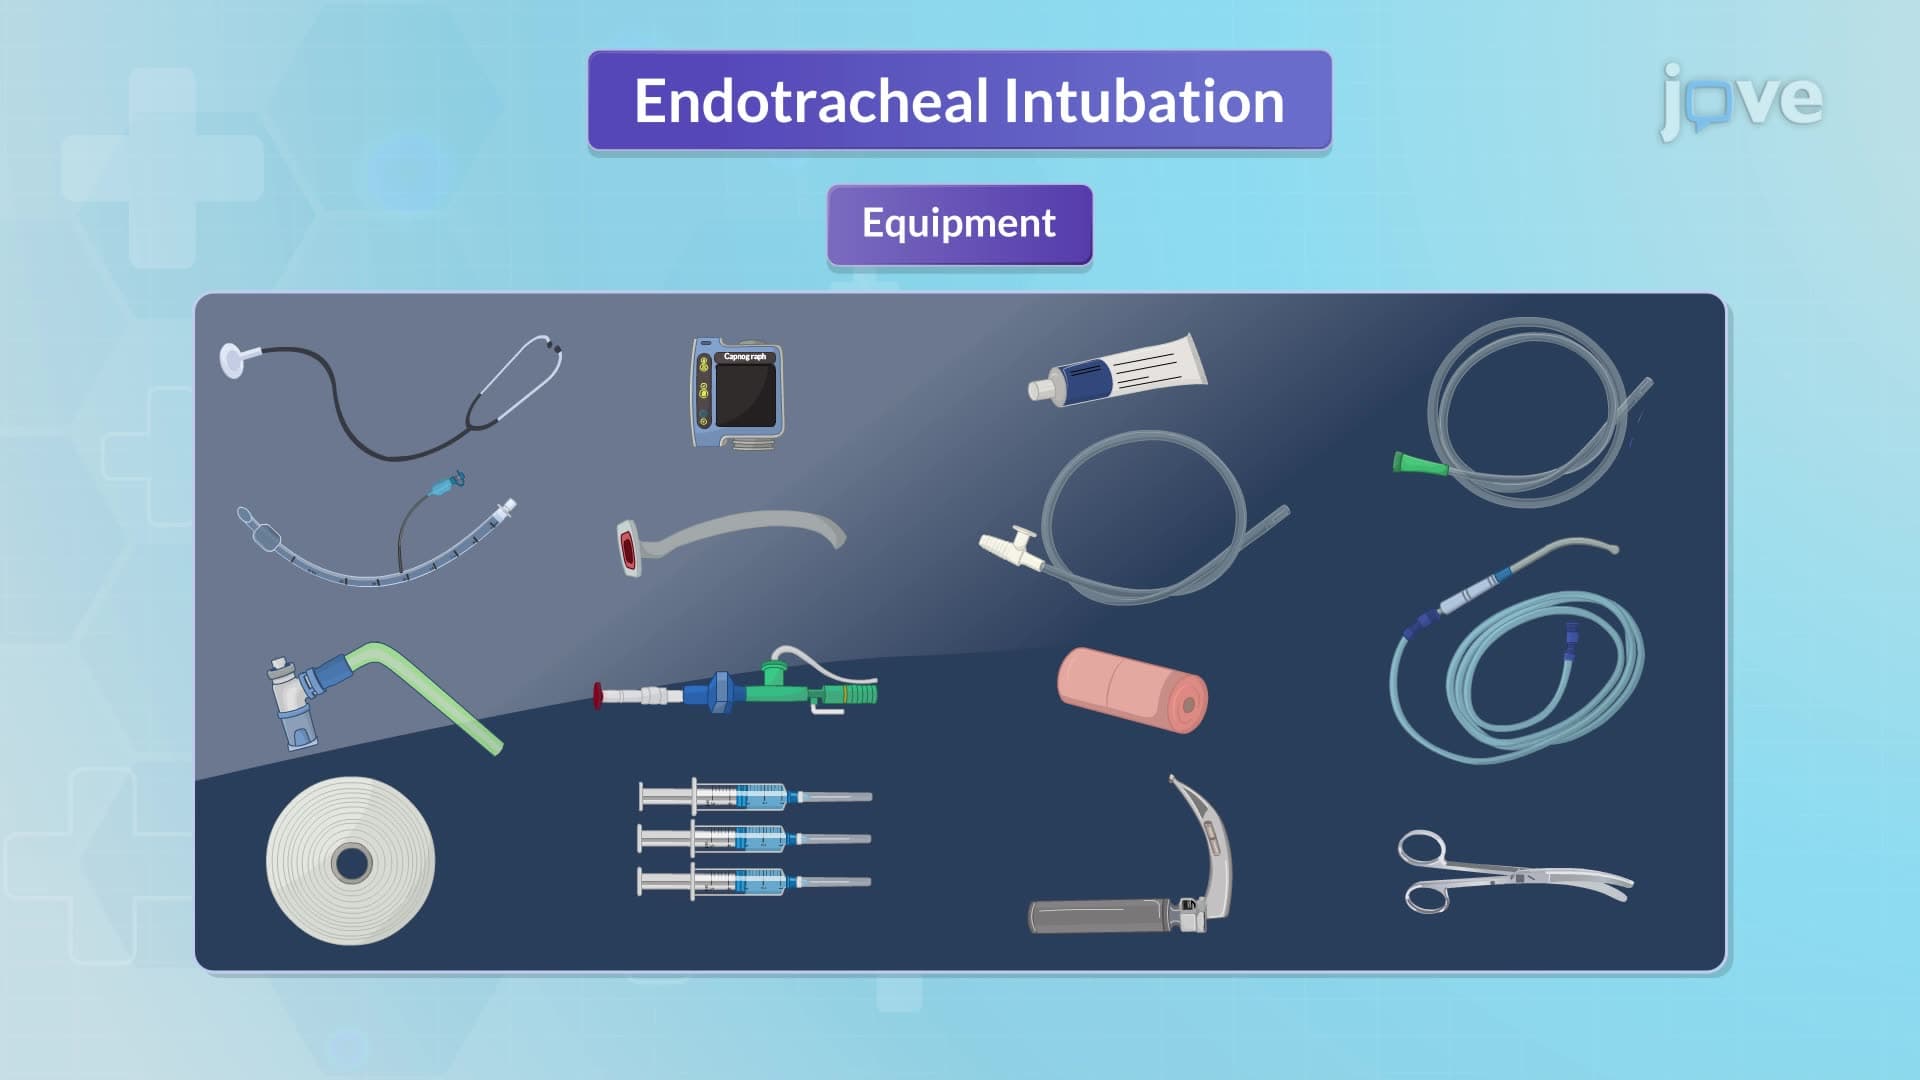
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
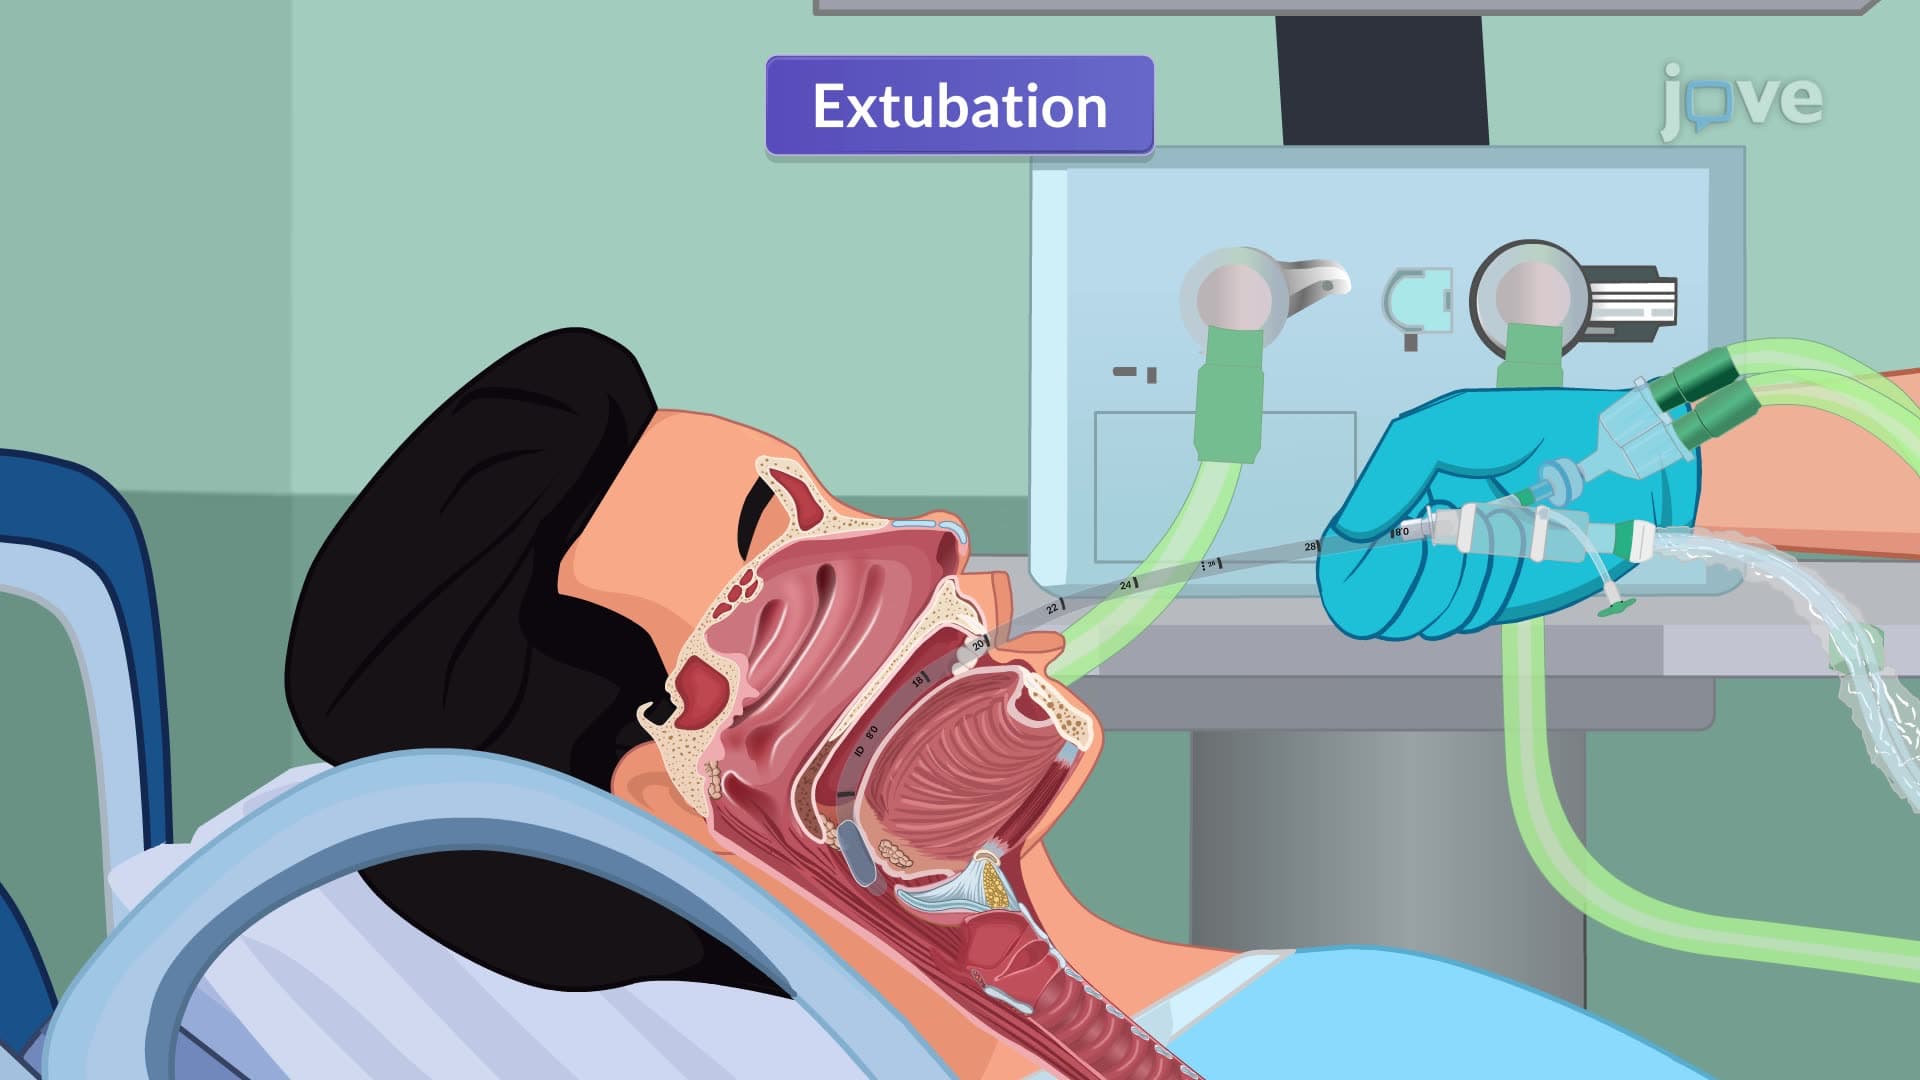
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care