Does Pre-operative Procalcitonin Add Diagnostic Value for Ventriculoperitoneal Shunt Infection After External Ventricular Drain? A Single-Institution Experience from Malaysia
Related Experiment Video
Updated: Nov 1, 2026
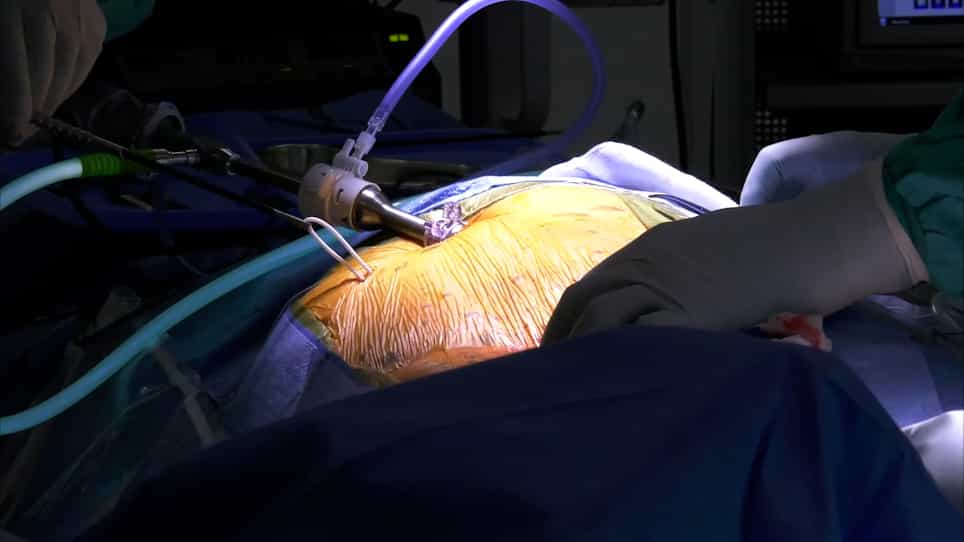
Neuronavigation and Laparoscopy Guided Ventriculoperitoneal Shunt Insertion for the Treatment of Hydrocephalus
Published on: October 14, 2022
Fauzan Arffin1, Ling Li Fan2, Retnagowri Rajandram3
1Division of Neurosurgery, Department of Surgery, Faculty of Medicine, Universiti Malaya, Kuala Lumpur, Malaysia.

Background:
Infection after ventriculoperitoneal (VP) shunt insertion following external ventricular drain (EVD) placement is clinically important, but the prognostic value of pre-operative serum procalcitonin (PCT) remains uncertain.
Objective:
To assess the association between pre-operative PCT and subsequent VP shunt infection and to compare PCT with other biomarkers and EVD-related factors.
Methods:
This retrospective, single-centre cohort included 85 independent patients who underwent VP shunt insertion after EVD placement at Universiti Malaya Medical Centre, Kuala Lumpur, Malaysia, from January 2020 to December 2025. All patients had serum PCT measured within 24 hours before surgery. The primary outcome was culture-confirmed VP shunt infection within three months. Analyses were limited to descriptive comparisons and receiver operating characteristic analysis because only seven infections occurred.
Results:
Seven of 85 patients (8.2%) developed VP shunt infection. Median pre-operative PCT was 0.24 ng/mL (IQR 0.09-0.30) in patients with infection and 0.10 ng/mL (IQR 0.04-0.18) in those without infection (P=0.106). PCT showed modest apparent discrimination (AUC 0.686; bootstrap 95% CI 0.469-0.877). Previous EVD infection was recorded in 28 patients and was more frequent among those who developed shunt infection (4/7 [57%] vs 24/78 [31%]; Fisher P=0.211).
Conclusions:
In this single-institution experience, pre-operative PCT showed modest and imprecise discrimination for later VP shunt infection. A single PCT value should not be used as a standalone predictor. These data do not validate a PCT cutoff or support recommendations about shunt timing.