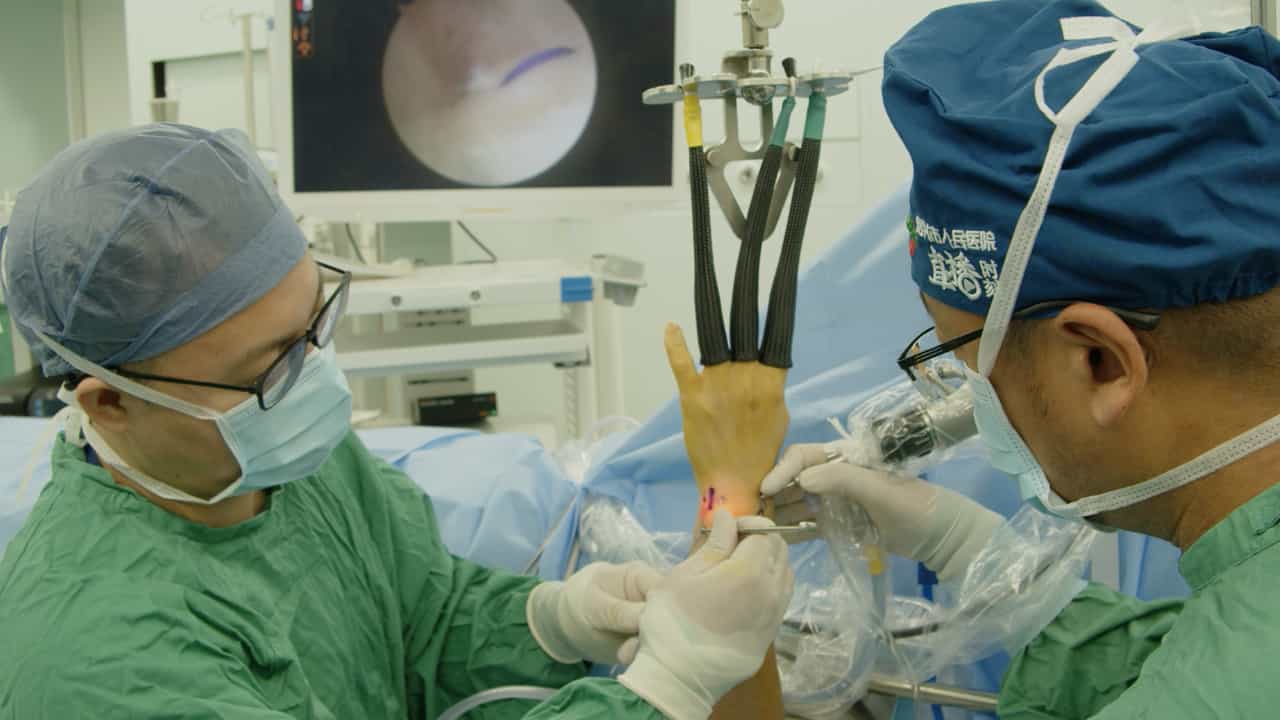
Closed reduction in distal radius fractures: manual manipulation vs. finger trap traction-a prospective randomized controlled clinical trial
Related Experiment Video
Updated: Nov 1, 2026
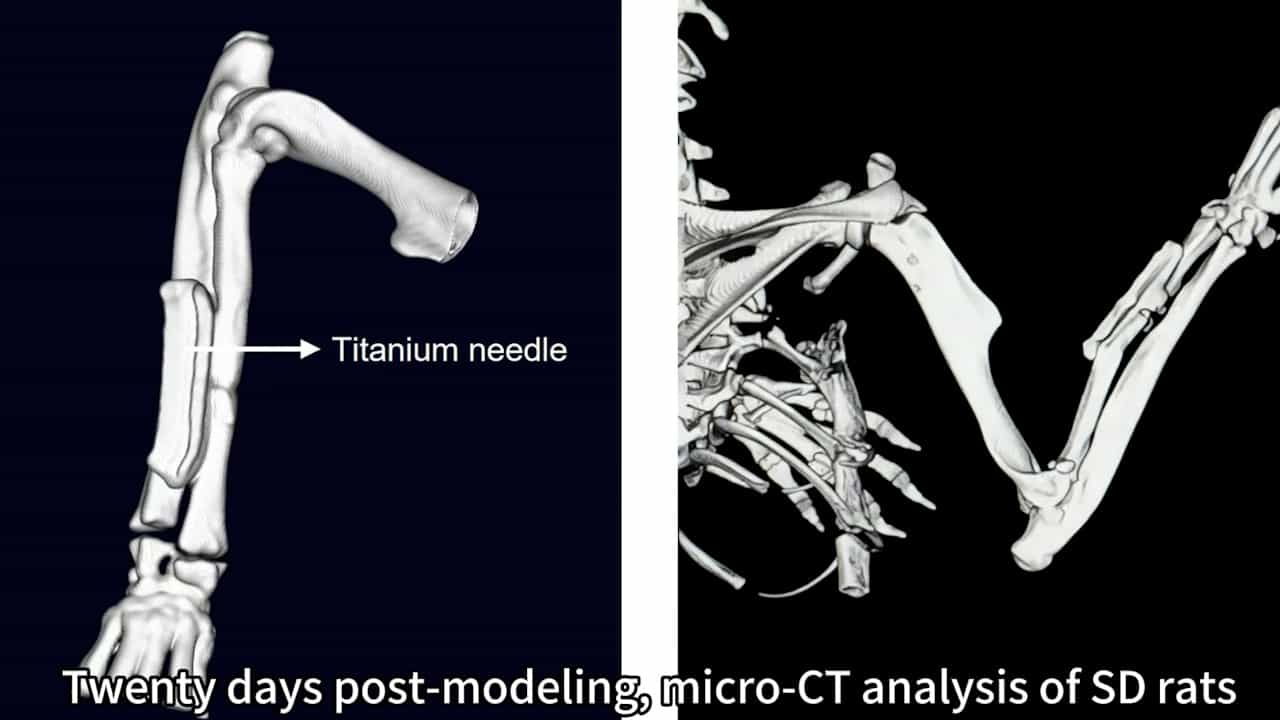
Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Stefan Benedikt1, Lukas Horling2,3, Simone Bode1
1University Hospital for Orthopaedics and Traumatology, Innsbruck Medical University, Innsbruck, Austria.

Background:
Initial treatment of distal radius fractures (DRF) can be either performed without reduction or with a reduction method as finger-trap traction (FTT) only or by additional manual reduction (MR) under hematoma block. There is no clear evidence on which reduction method is superior, however, MR is more invasive and seems to lead to higher pain levels and more post reduction complications. The objective of this study was to evaluate the clinical relevance of MR compared to FTT in acute DRFs.
Materials And Methods:
Study design was a prospective, single-centre, balanced randomized [1:1], and parallel grouped, controlled trial. Inclusion criteria were patients with a DRF type A2, A3 or C according to the AO classification and a dorsal tilt of ≥ 10°. The patients were randomized either in the FTT or in the MR group. Depending on the patient's functional demand and the fracture configuration, conservative or operative treatment was initiated. Over one year, clinical and radiological data were assessed at six follow-ups.
Results:
A total of 53 patients were included. Regarding radiological results neither FTT nor MR achieved sufficient reduction results (median dorsal tilt was - 16 to -18 after one year) and none of the techniques was superior. The clinical results between the conservatively treated groups were comparable and showed no significant difference. Complications included one CRPS in the conservative MR group, one CRPS after FTT and operation, one secondary carpal tunnel syndrome in the conservative FTT group and one skin lesion after MR.
Conclusion:
Manual reduction under haematoma block showed no benefit. In patients with AO type A2, A3 and type C fractures and a dorsal tilt ≥ 10° only FTT (if required under a haematoma block or comparable analgesia) is recommended regardless of whether surgery is performed or not.
Level Of Evidence:
Level I randomized controlled trial.
Trial Registration Number:
ClinicalTrials.gov, NCT07697976, registered 06/22/2026, retrospectively registered, www.
Clinicaltrials:
gov .