Consistency between Motor Nerve Conduction Studies and Changes in Clinical variables: A CIDP cohort study
Related Experiment Video
Updated: Nov 1, 2026
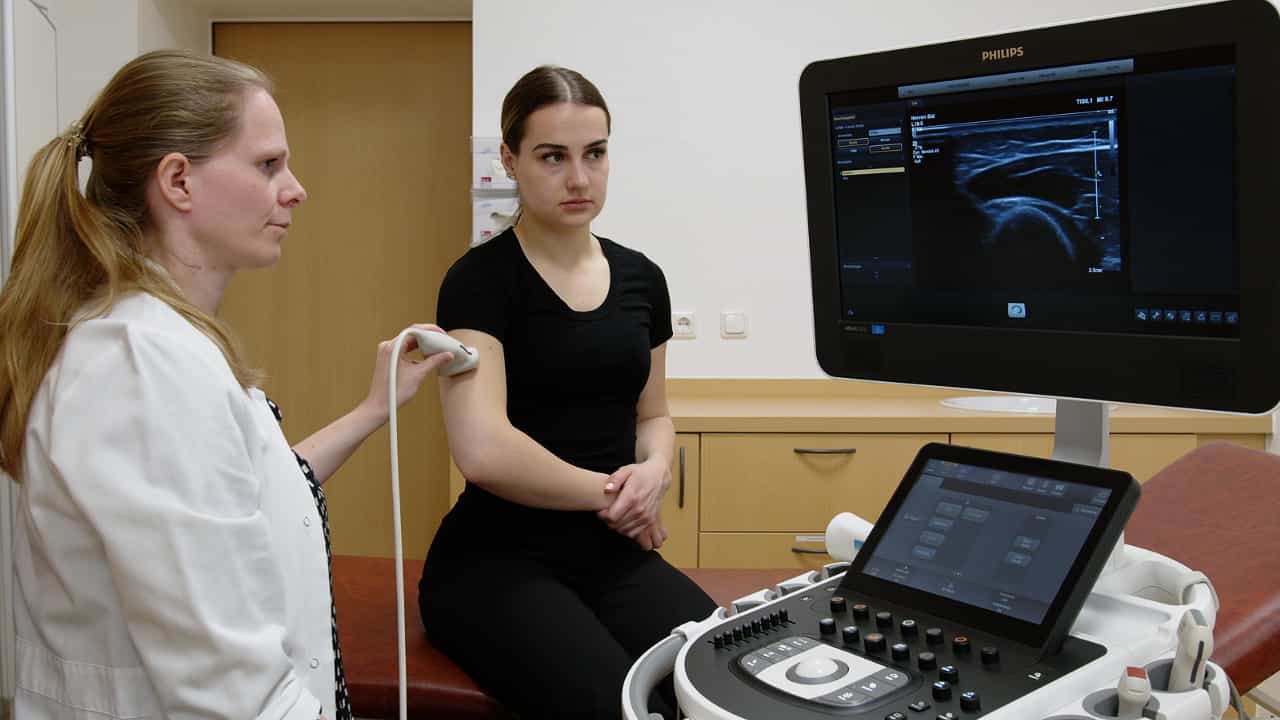
Nerve Ultrasound Protocol to Detect Dysimmune Neuropathies
Published on: October 7, 2021
Nan Hu1, Yichenga Zhu1, Liying Cui1
1Department of Neurology, Peking Union Medical College Hospital, Chinese Academy of Medical Sciences & Peking Union Medical College, Beijing, 100730, China.

Objective:
To investigate the consistency between nerve conduction study (NCS) improvements and clinical functional recovery in CIDP patients after immunotherapy.
Methods:
Twenty-six CIDP patients were prospectively enrolled. Clinical assessments included MRC sum score and INCAT scale. Motor NCS were performed on median, ulnar, tibial, and peroneal nerves at baseline and follow-up. Distal motor latency (DML), CMAP amplitude, motor conduction velocity (MCV), conduction block (CB), and temporal dispersion (TD) were analyzed using multiple absolute thresholds.
Results:
Overall, significant improvements were observed in MRC sum score, INCAT, and most NCS parameters. However, individual concordance was limited. Among patients with improved thumb abduction (n = 40), the proportion achieving ≥ 1.0 mV median CMAP increase was 70%; for improved ankle dorsiflexion (n = 25), only 40% achieved ≥ 0.5 mV peroneal CMAP increase. Using stricter thresholds (DML decrease ≥ 1.0 ms, upper limb CMAP increase ≥ 3 mV, MCV increase ≥ 10 m/s), the proportion fell below 50%. Eight patients (30.8%) showed clear clinical improvement without meaningful (< 10%) lower limb NCS changes. Upper limb CMAP correlations with muscle strength were moderate (rho 0.27-0.53, p < 0.05); lower limb correlations were weak or non-significant.
Conclusion:
Despite overall NCS improvements after CIDP immunotherapy, individual-level concordance with clinical recovery is limited, especially in lower limbs. Clinical functional scales should remain the primary outcome measures in CIDP trials.
Significance:
NCS parameters are not suitable as primary efficacy endpoints in CIDP trials. Clinical functional scales should remain the primary outcome measures for evaluating treatment response.