Testosterone treatment prevents most gonadectomy-induced metabolic and skeletal deficiencies in female mice
Related Experiment Video
Updated: Nov 1, 2026
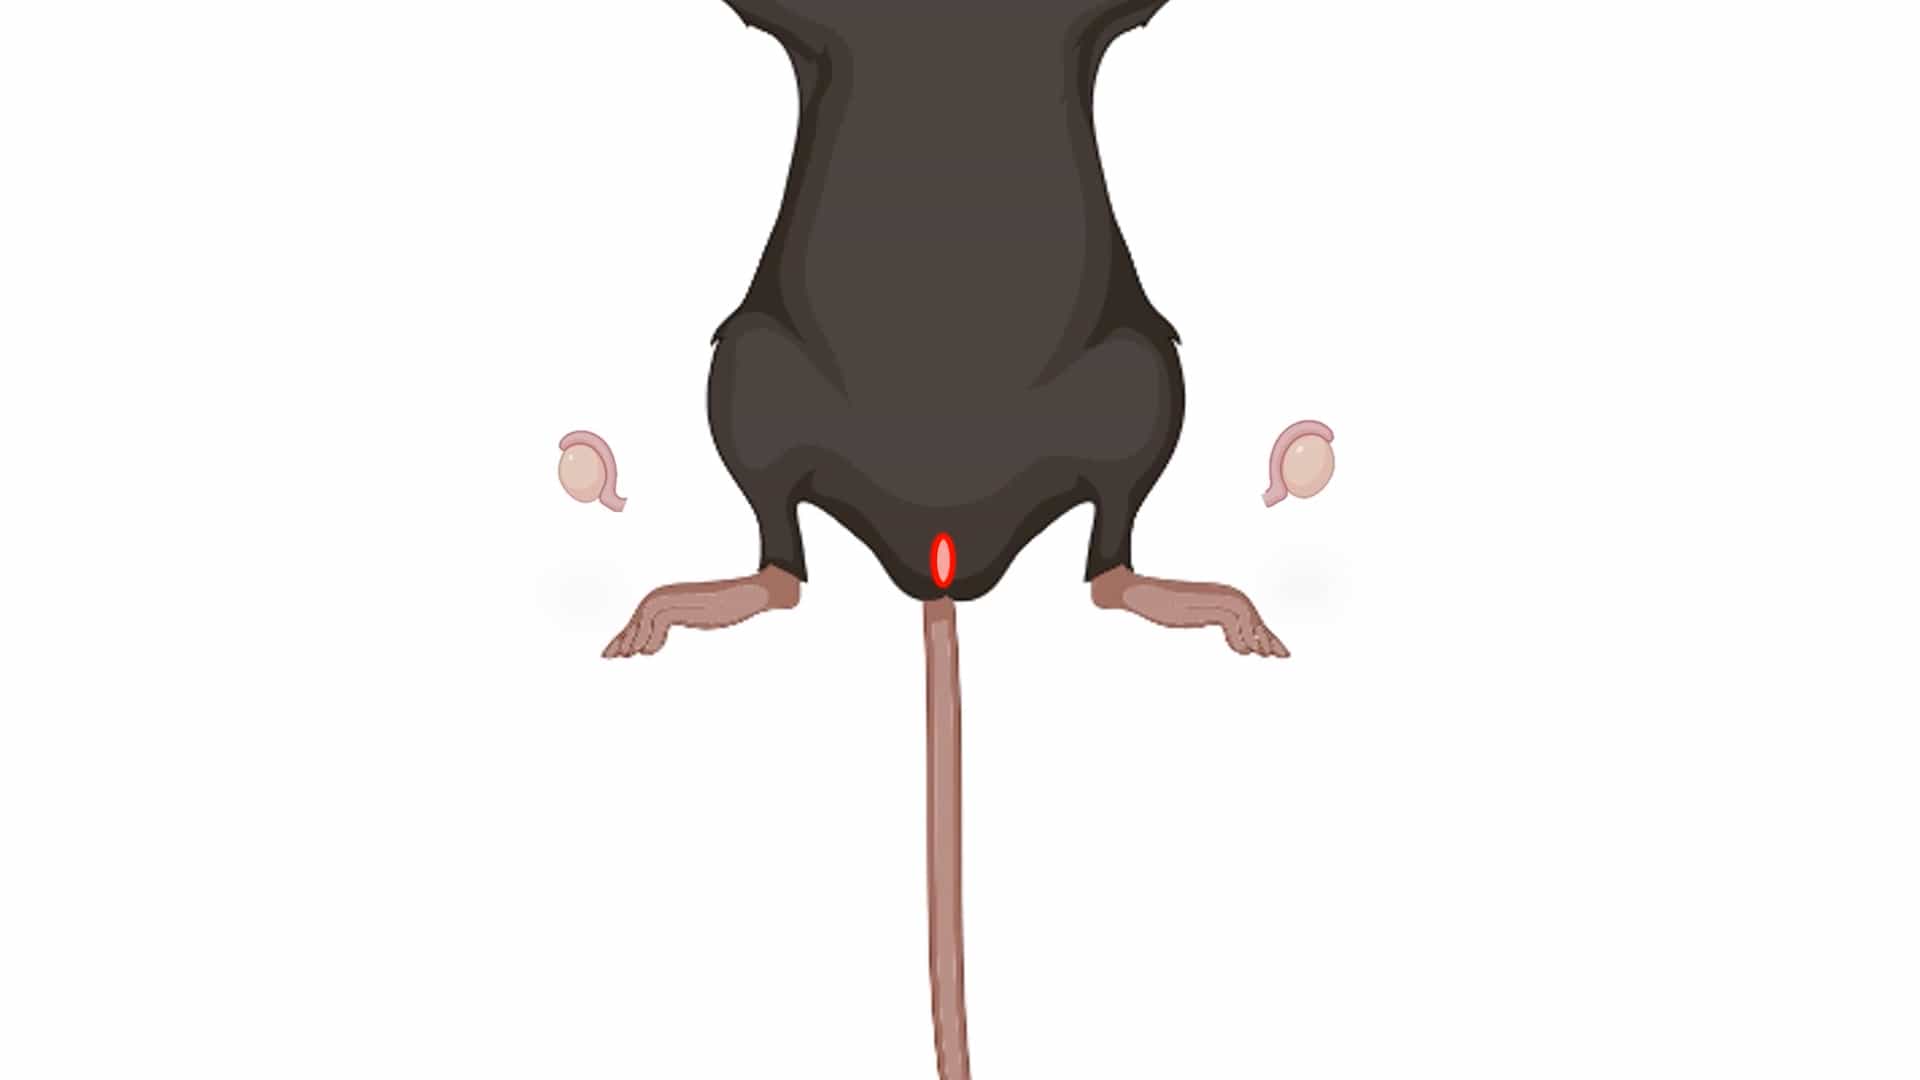
Murine Orchiectomy and Ovariectomy to Reduce Sex Hormone Production
Published on: November 17, 2023
Robin E Kruger1,2, Hannah Yohannes3, Evelyn Cho3
1Department of Obstetrics and Gynecology, University of Michigan, Ann Arbor, MI, United States.

Abstract:
Ovarian hormone depletion, whether due to ovariectomy, primary ovarian insufficiency, menopause, or gonadotoxic therapies, is associated with metabolic and skeletal dysfunction, while hyperandrogenic states such as polyendocrine metabolic ovarian syndrome are also linked to increased cardiometabolic risk. However, whether testosterone exacerbates, mitigates, or modifies the consequences of ovarian hormone loss remains poorly understood. This study examined whether testosterone treatment ameliorates ovariectomy-induced metabolic and skeletal impairments using an adult female mouse model. Eight-week-old CD-1 mice underwent sham surgery or ovariectomy and were implanted subcutaneously with capsules containing 10 mg testosterone or empty control capsules, yielding four experimental groups: Blank+Intact (n=7), Blank+OVX (n=7), Testosterone+Intact (n=7), and Testosterone+OVX (n=8). Each treatment combination resulted in hormonal milieus distinct to each group. After six weeks of treatment, testosterone mitigated ovariectomy-induced hyperglycemia and impaired glucose tolerance but did not prevent dyslipidemia or adipocyte hypertrophy (two-way ANOVA with Tukey's post hoc test, p<0.05). Testosterone treatment also increased circulating triglycerides, heart weight, femoral trabecular bone density, and radial strength independent of ovarian status. These findings indicate that testosterone compensates for some, but not all, metabolic and skeletal consequences of ovarian hormone loss, revealing distinct roles for androgens and estrogens in metabolic homeostasis. This may inform clinical management of ovarian insufficiency, menopause, hyperandrogenic disorders, and testosterone-based therapies.

