Model-informed precision dosing of vancomycin and amikacin in critically ill neonates: a pre- and post-intervention study
Related Experiment Video
Updated: Nov 1, 2026
A Neonatal Imaging Model of Gram-Negative Bacterial Sepsis
Published on: August 12, 2020
Beyza Kucukyildiz1, Merve Kasikci2, Irem Iyigun3
1Department of Clinical Pharmacy, Faculty of Pharmacy, Hacettepe University, Ankara, Türkiye.

Background:
Optimal antimicrobial dosing in neonates is complicated by extreme developmental pharmacokinetic (PK) variability. Traditional therapeutic drug monitoring (TDM) fails to achieve PK/pharmacodynamic (PK/PD) target attainment in this vulnerable population.
Objectives:
To evaluate whether implementation of Bayesian model-informed precision dosing (MIPD) improved PK/PD target attainment and exposure dose adjustment compared with conventional TDM in critically ill neonates.
Methods:
This pre- and post-intervention design comparing a historical retrospective cohort with a prospective MIPD validation single-center cohort study included 61 neonates receiving vancomycin or amikacin. An initial observational phase with standard dosing (n = 30) was followed by an intervention phase (n = 31) using Bayesian dose adjustment. Secondary outcomes included acute nephrotoxicity, ototoxicity, infection-related inflammatory biomarkers (ΔCRP and ΔProcalcitonin), illness severity (ΔSNAPPE-II), and the treatment-duration-to-hospital-length-of-stay ratio (DOT/LOS) in NICU.
Results:
Regarding posterior model concordance, agreement for vancomycin was limited, as evidenced by an overall mean absolute error (MAE) of 5.47 mg/L. For amikacin, concordance was modest (overall MAE: 8.96 mg/L; median absolute error [MdAE]: 1.31 mg/L), reflecting persistent modeling challenges. For vancomycin, therapeutic target attainment was higher with MIPD than with standard dosing (5/30, 16.7% vs. 1/26, 3.8%). Similarly for amikacin, therapeutic target attainment was higher in the MIPD group (10/27, 37.0% vs. 5/26, 19.2%). In an exploratory secondary analysis, ΔSNAPPE-II differed between the standard dosing and MIPD cohorts (-2.5 vs. 0; p = 0.040), favoring standard dosing; as SNAPPE-II is not validated for longitudinal monitoring and the design was non-randomized, this does not constitute evidence of clinical benefit for either strategy. For the overall combined cohort, DOT/LOS was significantly lower in the MIPD group (p = 0.043). No differences in the rates of acute kidney injury (6.9% vs. 10.0%, p = 1.000) or ototoxicity (8.0% vs. 7.1%, p = 1.000) were detected, although the study was underpowered to rule out clinically important differences.
Conclusion:
Bayesian MIPD was associated with numerically but not statistically higher pharmacodynamic target attainment (AUC/MIC and Cmax/MIC) for vancomycin and amikacin, and no improvement in clinical outcomes was demonstrated. While amikacin modeling requires further refinement, adequately powered trials are needed to definitively assess the impact of MIPD on safety and clinical outcomes.
Related Concept Videos
 01:15
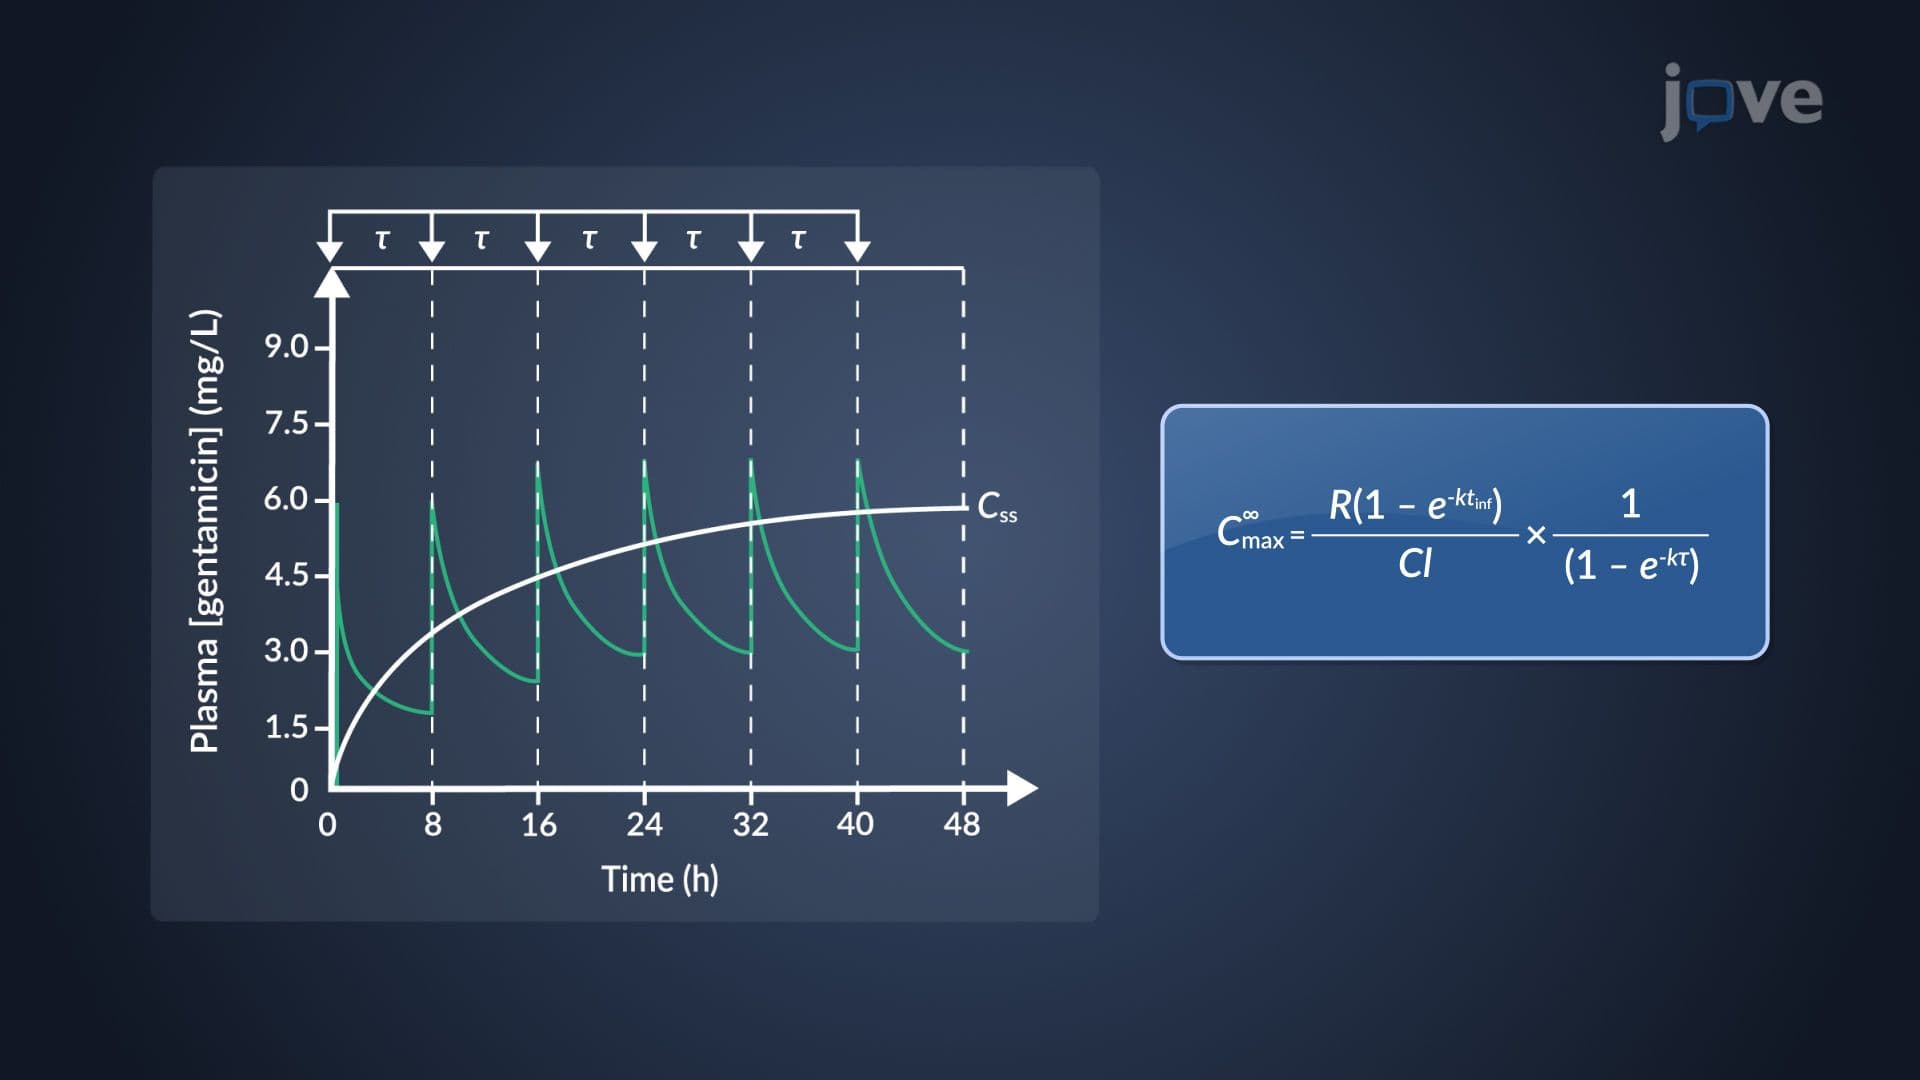
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:29
Drug Dosing: Infants and Children
 01:20
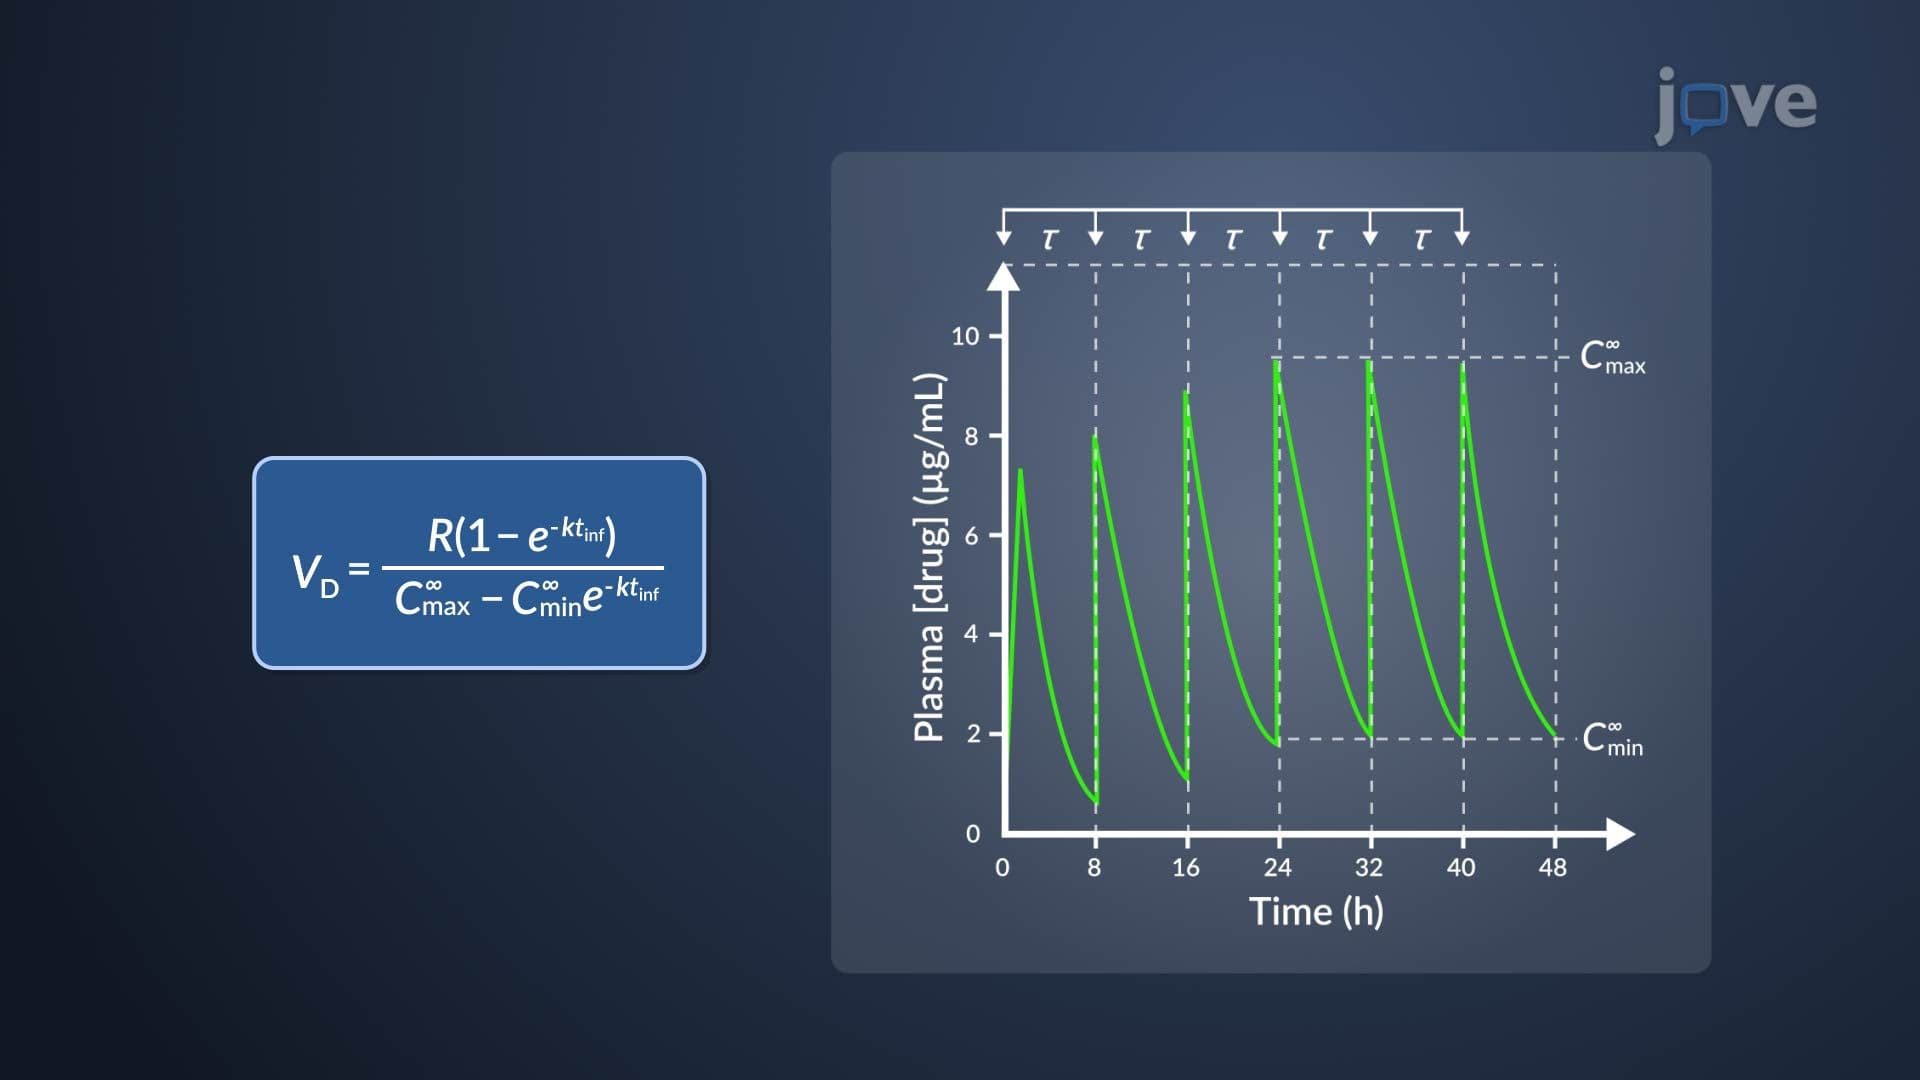
Estimation of k and VD of Aminoglycosides
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses