Dual-Channel Percutaneous Endoscopic Interlaminar Discectomy with Auxiliary Bony Decompression
Related Experiment Video
Updated: Nov 2, 2026
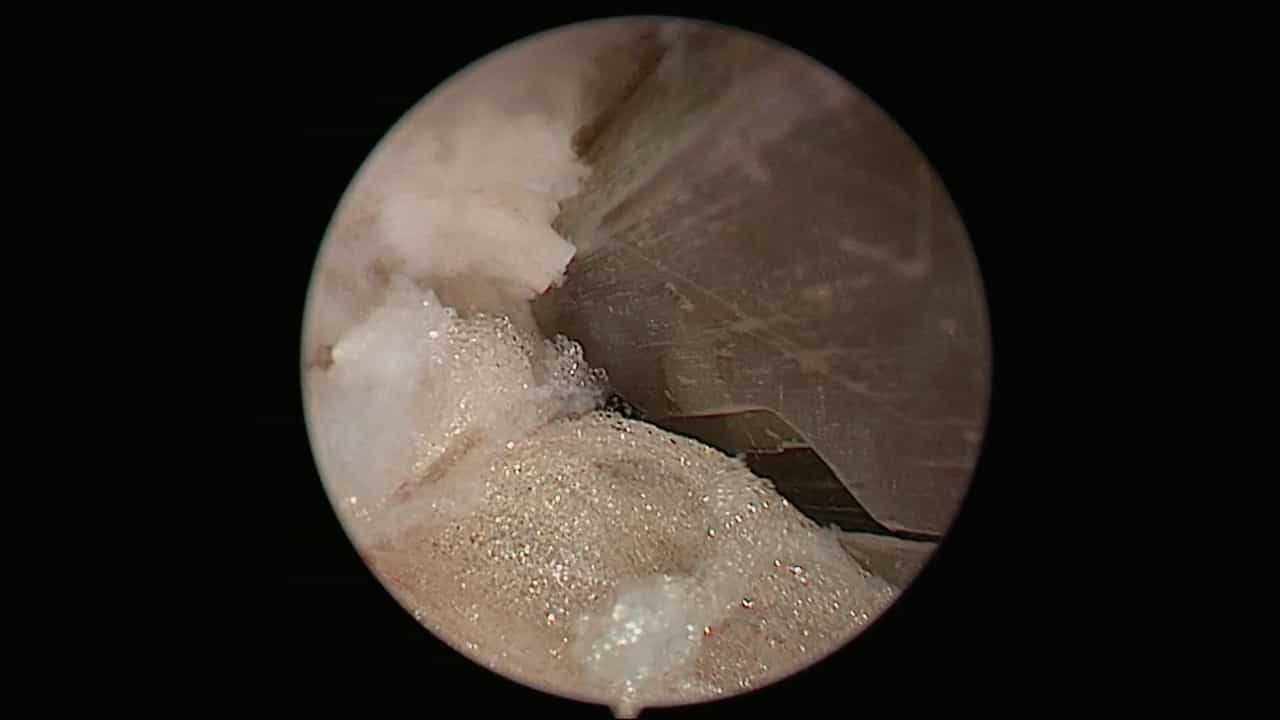
The Third Channel-Assisted Unilateral Biportal Endoscopic Technique for Lumbar Spinal Stenosis Combined with Contralateral Disc Herniation
Published on: November 17, 2023
Yanhong Chen1,2, Rujia Yu3, Zhouyang Hu1
1Department of Pain Medicine, National Key Clinical Pain Medicine of China, Shenzhen Nanshan People's Hospital.

Abstract:
Percutaneous endoscopic interlaminar discectomy (PEID) is frequently limited by hypertrophic lamina and lateral recess stenosis that confine instrument maneuverability within a single working cannula. Unilateral biportal endoscopy (UBE) overcomes these anatomical constraints but requires dedicated arthroscopes, larger incisions, and a distinct learning curve. Here we describe a modified dual-channel PEID technique that preserves standard single-portal instrumentation while achieving biportal-like working freedom and expanded instrument access for bony decompression through dynamic, bidirectional interchangeability of a single endoscope-cannula assembly between two ipsilateral 7.5 mm portals. A secondary sleeve-free channel is established 1.5-2.0 cm cranial to the primary portal to facilitate aggressive laminotomy and medial facetectomy using conventional osteotomes and Kerrison rongeurs, while the primary portal maintains continuous endoscopic visualization. The endoscope-cannula assembly is reversibly transferred between portals to optimize viewing angles for sequential decompression of the lamina, ligamentum flavum, and superior articular process, followed by standard discectomy and neural decompression through the primary working channel. Quantitative computed tomography (CT) analysis in an index patient with L5/S1 disc herniation and ligamentum flavum hypertrophy demonstrated a bony decompression volume of 695.1 mm3, laminectomy thickness of 6.79 mm, and superior articular process undercutting of 13.70 mm. This technique bridges the capability gap between conventional PEID and UBE for patients with concomitant bony stenosis, achieving extensive lateral recess decompression without dedicated biportal equipment or additional specialized instrumentation.