Age-adjusted and probability-adjusted D-dimer thresholds for the diagnosis of acute DVT: a narrative review
Related Experiment Video
Updated: Nov 2, 2026
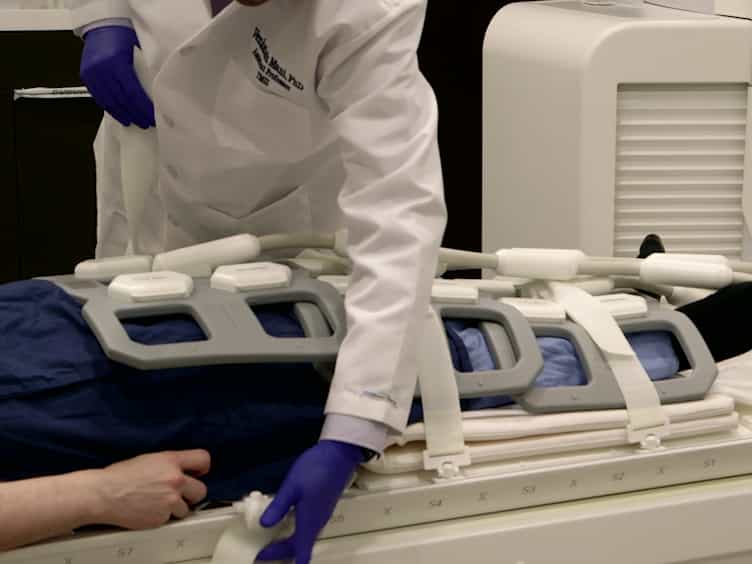
A Multicenter MRI Protocol for the Evaluation and Quantification of Deep Vein Thrombosis
Published on: June 2, 2015
Faisal Almuhanna1, Abdulmajeed Alotaibi2, Mohommad Abdulaal3
1Division of Hematology, University of Ottawa, Ottawa, Ontario, Canada; Division of Internal Medicine, Security Forces Hospital, Riyadh, Saudi Arabia.

Abstract:
In patients presenting to emergency departments with symptoms of lower-limb deep vein thrombosis (DVT), systematically ordering a compression ultrasonography (CUS) in all to rule out DVT contributes to crowding and low-yield testing. Contemporary diagnostic strategies aim at improving efficiency by avoiding the need for a CUS, while maintaining safety, as assessed by low short-term venous thromboembolism (VTE) rates among patients with a negative diagnostic work-up. This narrative review summarizes recent evidence, mainly from prospective management studies, supporting refined D-dimer-based pathways for first-episode DVT, and emerging data in patients with suspected recurrent DVT. In ADJUST-DVT, an age-adjusted D-dimer threshold (age×10 μg/L for ≥50 years) applied to outpatients with a non-high/unlikely pretest probability increased the proportion of patients ruled out without ultrasound by 7% overall as compared with the conventional 500 μg/L cutoff, with the largest gains in those ≥75 years. No failures were identified in patients with a D-dimer level 500 μg/L or greater but below the age-adjusted cutoff (0%, 95% confidence interval (CI) 0%-2.3%). In the 4D study, a clinical probability-adjusted D-dimer strategy (low Wells with D-dimer <1000 μg/L; moderate Wells with <500 μg/L) achieved a 0.6% 3-month VTE rate while reducing ultrasound use by 47%. In patients with a suspected recurrent ipsilateral DVT, D-dimer levels are often higher than in patients without previous DVT and are therefore less useful to exclude the disease. In this situation, a negative D-dimer test may also be associated with a higher failure rate. Indeed, in the PREDICTORS study, a higher-than-expected prevalence of recurrent VTE at presentation in patients with a non-high pretest probability and a negative D-dimer was reported. While CUS is also frequently non-diagnostic due to residual thrombi, the THEIA Study showed that magnetic resonance direct thrombus imaging (MRDTI) can safely guide management as a single test. Together, these studies support practical, outcome-validated approaches that improve diagnostic efficiency and may facilitate implementation in real-world workflows, while highlighting the need for accurate pretest assessment and continued prospective validation of simplified algorithms.
Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Venous Thrombosis III: Interprofessional Care
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation