Updated Staging System to Define Cardiogenic Shock Severity A Cardiogenic Shock Working Group Report
Related Experiment Video
Updated: Nov 3, 2026
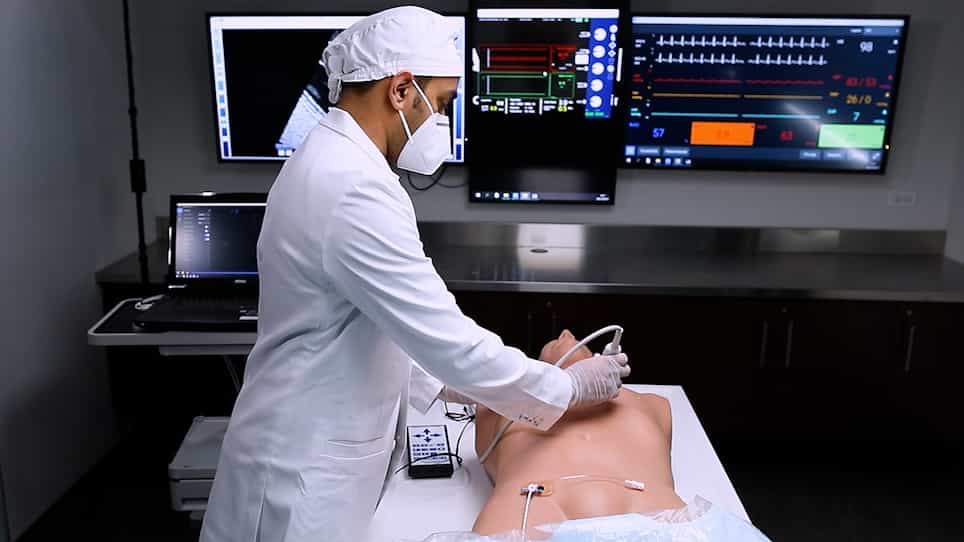
Utilizing Percutaneous Ventricular Assist Devices in Acute Myocardial Infarction Complicated by Cardiogenic Shock
Published on: June 12, 2021
Van-Khue Ton1, Song Li2, Elric Zweck3
1The Mass General Brigham Heart and Vascular Institute, Massachusetts General Hospital, Boston, MA, USA.

Background:
Cardiogenic shock (CS) severity is defined by the Society for Cardiovascular Angiography and Interventions (SCAI) stages and modifications from the Cardiogenic Shock Working Group (CSWG). Lactate thresholds, treatment intensity, and cardiac arrest modifiers remain incompletely defined. We aimed to refine the 2022 CSWG staging criteria using contemporary data.
Methods:
Patients with CS from heart failure (HF-CS) or myocardial infarction (MI-CS) enrolled in the multicenter CSWG registry (2021-2025) were analyzed. Associations between systolic blood pressure (SBP), lactate, treatment intensity, and in-hospital mortality, which is considered a surrogate for CS severity, were examined. External application of the updated system was performed in an independent U.S. health system.
Results:
Among 11,640 patients (60.5% HF-CS, 26.1% MI-CS), SBP and lactate demonstrated graded relationships with mortality across thresholds (SBP<60, 60-<90, ≥90 mmHg; lactate 0-2, >2-5, >5-10, >10 mmol/L). Mortality increased incrementally with treatment intensity. The 2026 staging system incorporating these thresholds and the number of vasoactive drugs and temporary mechanical circulatory support devices (stage C: 1-2, D: 3-4, E: ≥5) demonstrated progressive mortality across stages. Compared with prior CSWG staging, 28.4% of stage D and 56.4% of stage E patients were reclassified, with lower mortality among those reclassified to less severe stages. Out-of-hospital cardiac arrest functioned best as a stage modifier, whereas in-hospital cardiac arrest corresponded to stage E. Findings were consistent across HF-CS and MI-CS. The 2026 CS staging system was evaluated in 1,417,637 patients in a geographically and structurally diverse healthcare system and demonstrated a graded, monotonic increase in mortality across stages A-E.
Conclusions:
Using fewer clinical variables, the 2026 CSWG criteria provide a simple framework for CS severity staging that is applicable among HF-CS and MI-CS patients, and can be standardized across clinical trials and healthcare settings.
Related Concept Videos
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:29
Cardiomyopathy V: Interprofessional Care
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy