Bilateral Iliac Branch Endoprosthesis Deployment With IVUS-Guided Contrast-Sparing Technique: A Complex Case Report
Bachar Al Haj1, Charlott E Koehler1, Martin J Austermann1
1Department of Vascular and Endovascular Surgery, St. Franziskus Hospital Muenster, Germany.

Background:
Preserving internal iliac artery (IIA) patency during endovascular aortic repair (EVAR) for aortobiiliac aneurysms typically requires substantial contrast volume, posing risk to patients with renal insufficiency.
Case Description:
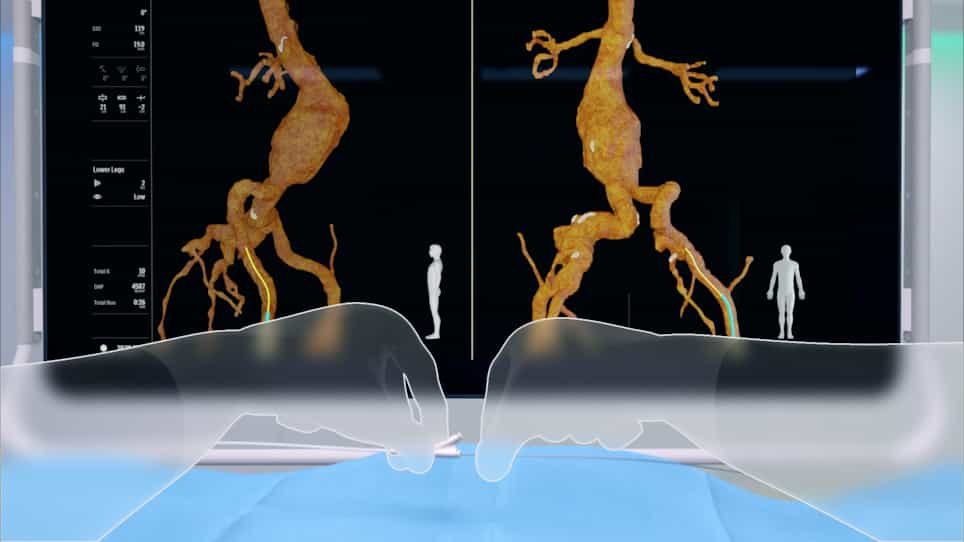
We present the case of an elderly female with chronic kidney disease (CKD) stage 3b (baseline estimated glomerular filtration rate 35 mL/min/1.73 m², serum creatinine 1.5 mg/dL) and an aortobiiliac aneurysm who underwent complex bilateral iliac side-branch (iliac branch endoprosthesis [IBE]) deployment. The procedure used intravascular ultrasound (IVUS) as the primary guidance to minimize contrast exposure. A notable intraoperative challenge arose on the left side, where retrograde cannulation was unsuccessful due to anatomical tortuosity and sheath dislodgement. We therefore performed a left axillary cut-down, which facilitated successful IIA reconstruction and resolved a type 1b endoleak. The total contrast volume employed was approximately 38 mL. Incidental findings included hyperthyroidism and suspected lymphoproliferative disorder.
Conclusion:
Intravascular ultrasound-guided bilateral IBE is feasible and substantially reduces contrast exposure in patients with renal impairment, though technical flexibility is essential for complex anatomy.Clinical ImpactIVUS-guided bilateral iliac branch endoprosthesis deployment may offer a contrast-sparing option for patients with chronic kidney disease undergoing endovascular repair of complex aortobiiliac aneurysms. Using IVUS for vessel identification, sizing, landing-zone selection, and stent-apposition assessment can reduce reliance on iodinated contrast while preserving internal iliac artery perfusion. This case shows that bilateral reconstruction is feasible with only 38 mL of contrast, even when complex anatomy requires axillary access. Its innovation is using IVUS as the primary guidance modality, with angiography reserved for confirmation and troubleshooting.
Related Concept Videos
 01:28
Endoscopic Procedures III: Video Capsule Endoscopy
 01:22
Imaging Studies VI: Voiding Cystourethrography and Cystography
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:28
Urologic Endoscopic Procedure: Cystoscopic Examination
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography