Bilateral Erector Spinae Plane Block With 0.375% Ropivacaine and Postoperative Analgesia After Laparoscopic Cholecystectomy: A Prospective, Randomized, Controlled Cohort Study
Related Experiment Videos
Kenny Omar Contreras Becerra1, Jesus Alberto Sanson-Riofrio2, Juan Manuel Lopez Diaz3
1Department of Clinical Coordination for Education and Research/Anesthesiology, Hospital General de Zona No. 33, Instituto Mexicano del Seguro Social (IMSS) en Bahia de Banderas, Nayarit, MEX.

Introduction:
Postoperative pain after laparoscopic cholecystectomy may delay recovery and increase opioid exposure. The erector spinae plane block has been proposed as a component of multimodal analgesia, but local prospective data remain limited.
Methods:
This prospective, randomized, controlled cohort study included 40 adults undergoing elective laparoscopic cholecystectomy. Of these, 20 participants received an ultrasound-guided bilateral erector spinae plane block at T9 with 0.375% ropivacaine (20 mL per side) plus multimodal analgesia, and the remaining 20 patients received multimodal analgesia without the block. The prespecified primary endpoint was resting Numeric Rating Scale pain at 12 hours. Secondary outcomes included pain at additional time points and recorded rescue tramadol use. Analyses were unadjusted and included repeated-measures models, Holm-adjusted pointwise comparisons, standardized mean differences, and Fisher exact tests.
Results:
At 12 hours, mean resting pain was 1.80 ± 0.70 in the block group and 3.40 ± 1.31 in the comparison group (mean difference -1.60; 95% CI -2.28 to -0.92; p<0.001; Hedges' g=-1.49). The difference did not reach the prespecified two-point threshold used for sample size planning. Recorded rescue tramadol use occurred in two (10.0%) participants in the block group versus 14 (70.0%) participants in the comparison group (risk ratio 0.143; 95% CI 0.037-0.549; absolute risk difference -0.60; p=0.00024). The group-by-time interaction was not significant for resting or movement pain. Postoperative nausea and vomiting occurred in one participant per group.
Conclusions:
Bilateral erector spinae plane block was associated with lower unadjusted pain scores and a marked reduction in recorded rescue tramadol use. The most clinically salient signal was the lower frequency of recorded rescue analgesia, although the indication for every administration could not be independently verified. Because the primary pain difference remained below the prespecified two-point threshold, the findings should be considered hypothesis-generating.
Related Concept Videos
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:29
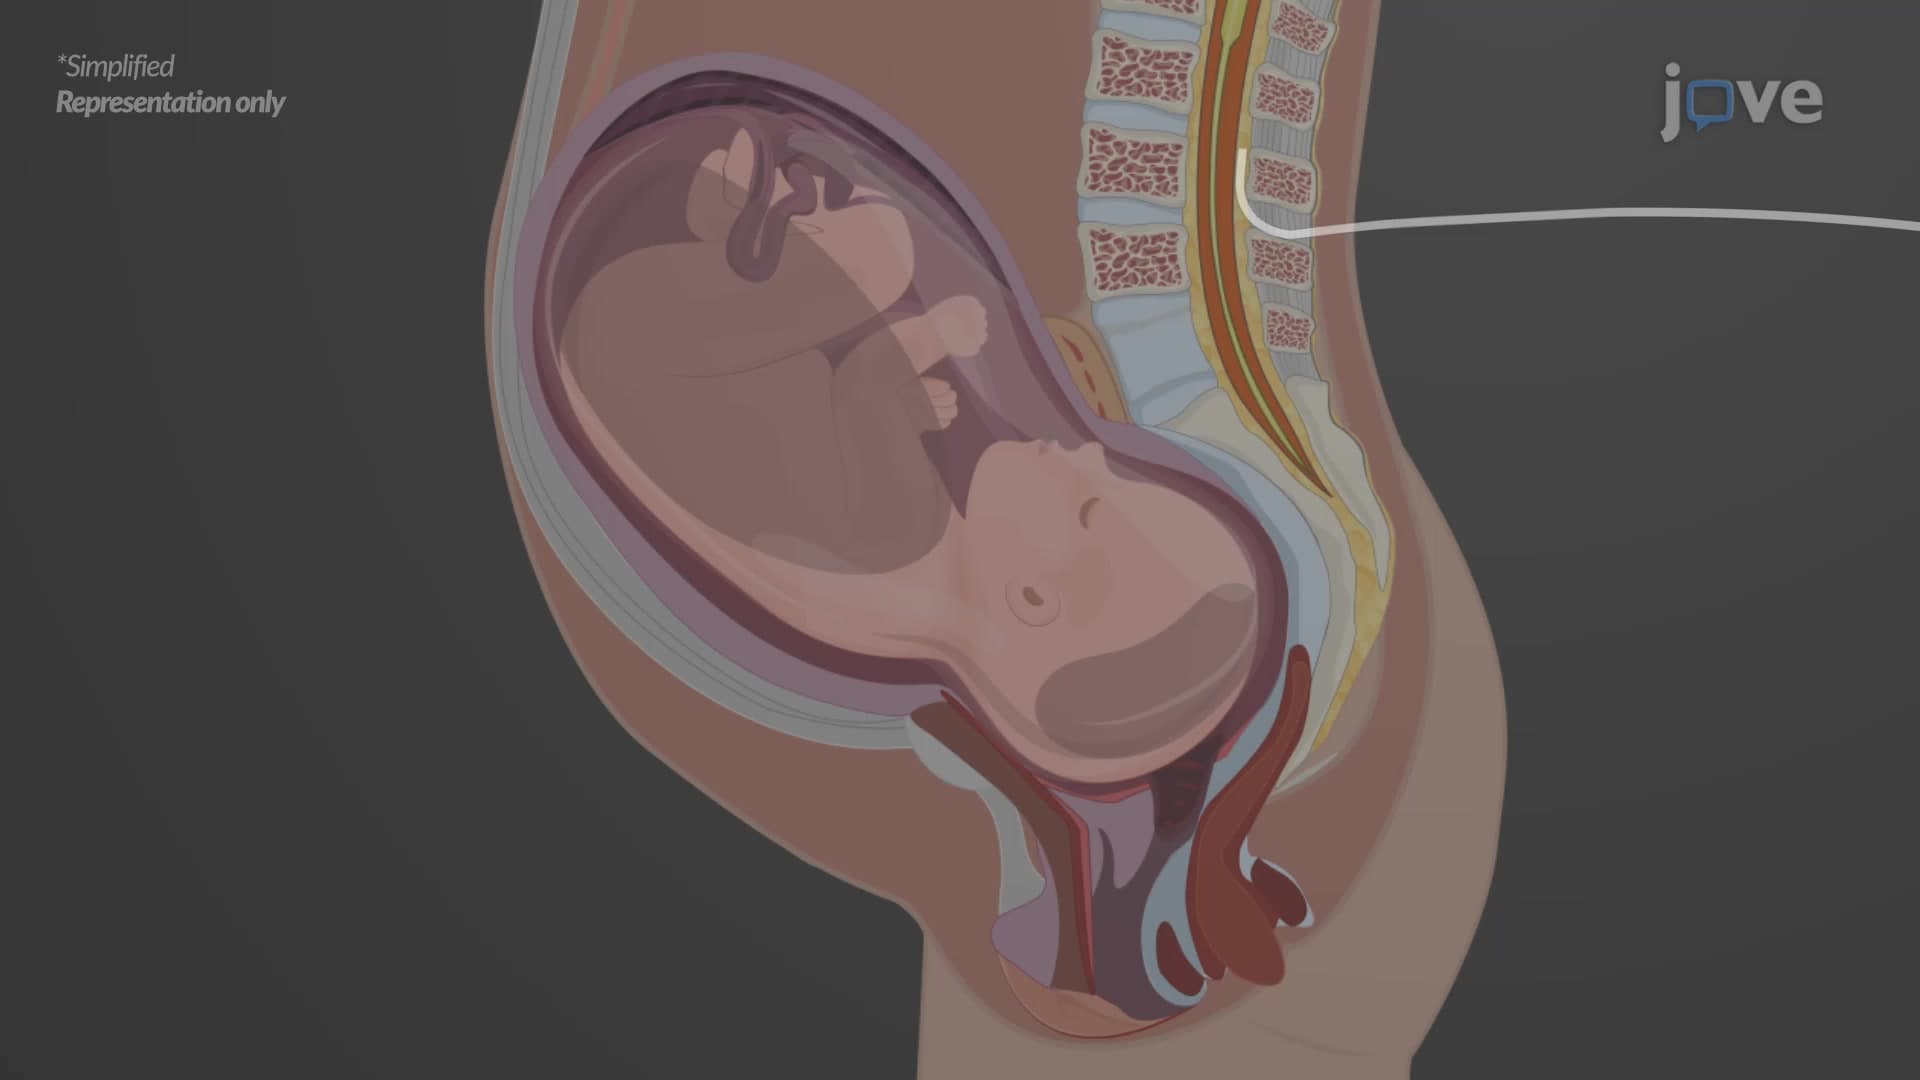
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:19
Depolarizing Blockers: Pharmocokinetics