Cerebellar and frontal lobe alterations in pulmonary hypertension implicate an inflammatory lung vascular/brain axis
Related Experiment Videos
Satoshi Okawa1,2,3, Yinan Shi1, Somanshu Banerjee4
1Center for Pulmonary Vascular Biology and Medicine, Pittsburgh Heart, Lung, and Blood Vascular Medicine Institute, Division of Cardiology, Department of Medicine.

Abstract:
Connections between vascular and neurocognitive diseases are emerging but remain poorly defined. Cognitive impairment is increasingly recognized in pulmonary hypertension (PH), a disease traditionally viewed as limited to the heart and lungs. Given that inflammation is shared by PH and neurodegenerative diseases, we investigated its role in driving brain and cognitive deficits in PH. Using structural and functional MRI data from UK Biobank (N = 248 PH) and a prospective validation cohort, we identified reduced cerebellar white matter volume, thinner frontal gyri, and weakened cerebellar-frontal connectivity in patients with PH but not in other heart or lung diseases. These changes were accompanied by worsened executive function and processing speed. Olink proteomics and targeted genomics linked inflammatory plasma proteins and a PH-associated nuclear receptor coactivator 7 (NCOA7) single nucleotide polymorphism, rs11154337, to these deficits. PH cerebellum showed increased microglial activation and white matter derangement. In PH mice, Ncoa7 deficiency worsened cerebellar inflammation and atrophy. Microglial functional assays, cerebellar single-nucleus RNA sequencing, and spatial transcriptomic analyses further implicated Ncoa7-dependent lysosomal, inflammatory, and cell-specific mechanisms of cerebellar pathobiology. These findings identify NCOA7-linked inflammatory dysfunction in the cerebellar-frontal axis in PH, redefining this disease with neurologic consequences and thus offering neural targets for diagnostic, prognostic, and therapeutic development.
Related Concept Videos
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:22
Cerebral Edema ll: Pathophysiology
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:24
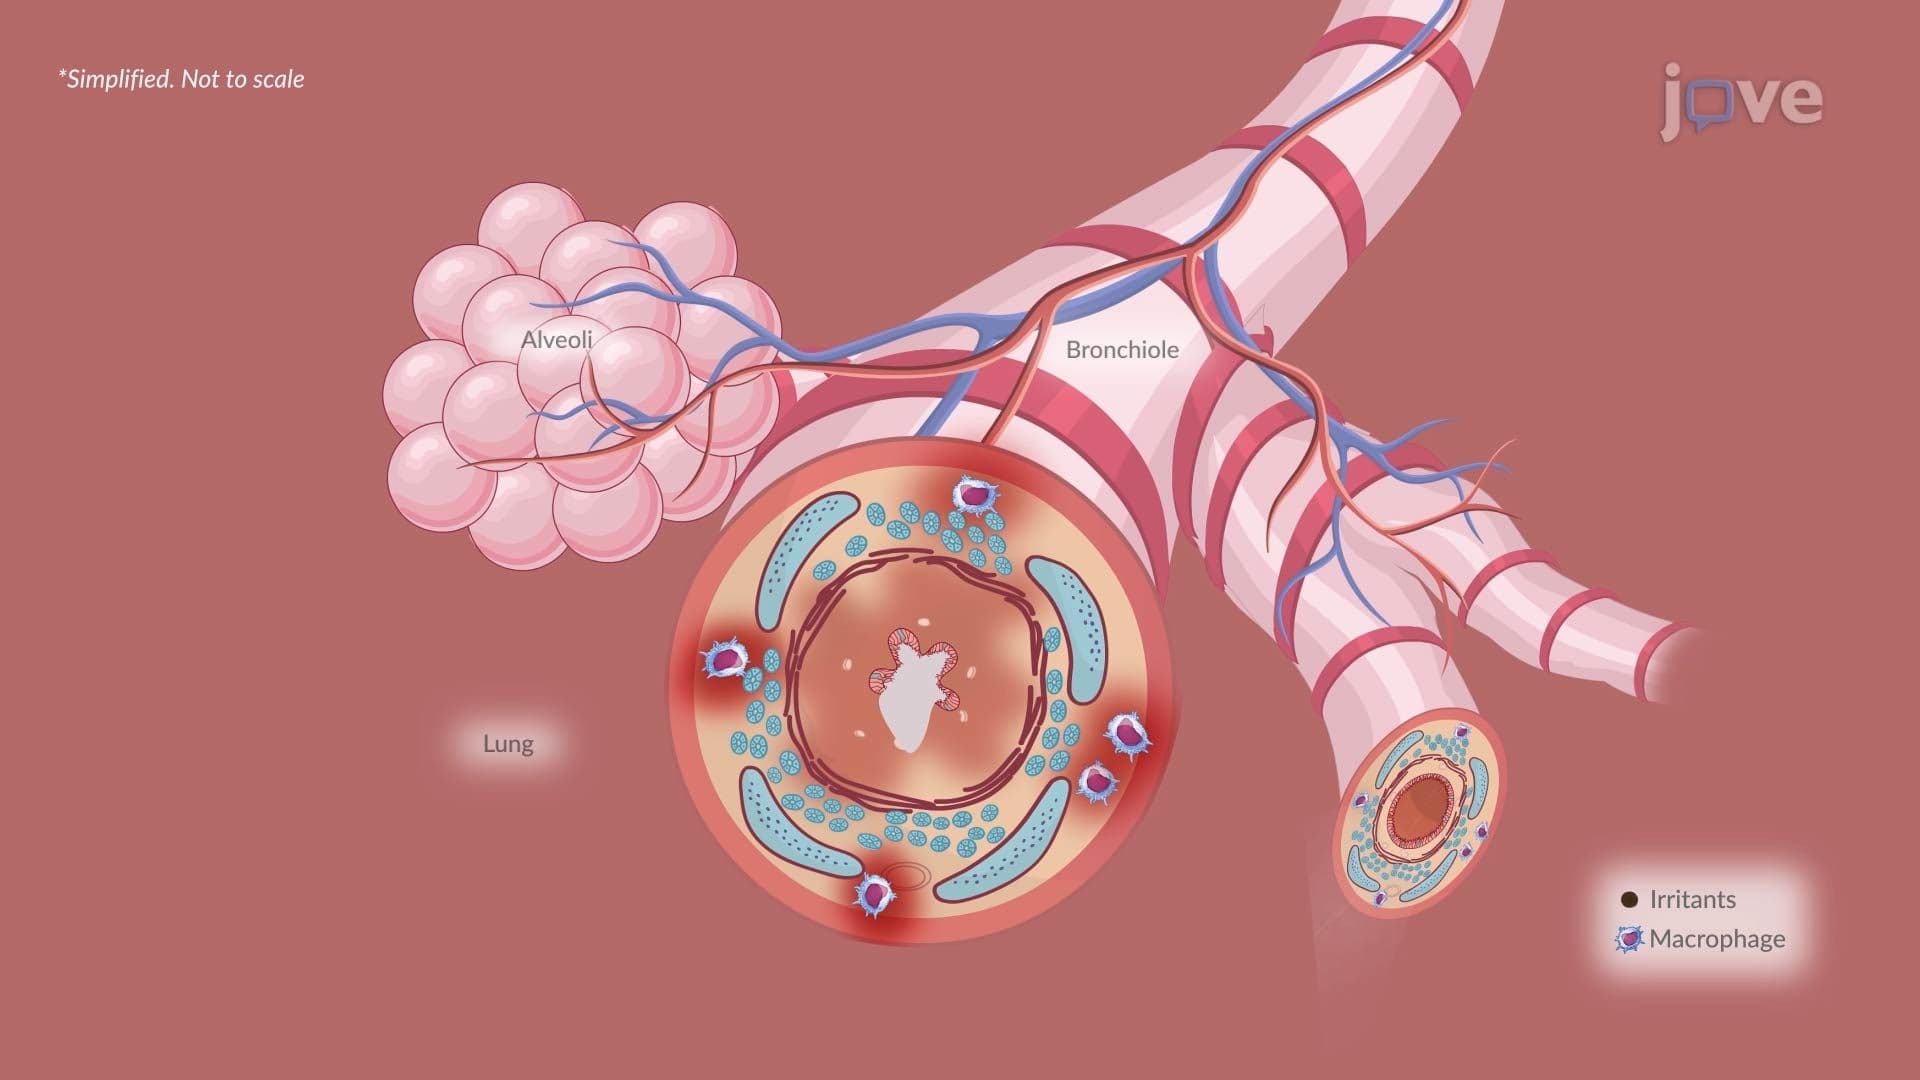
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:29
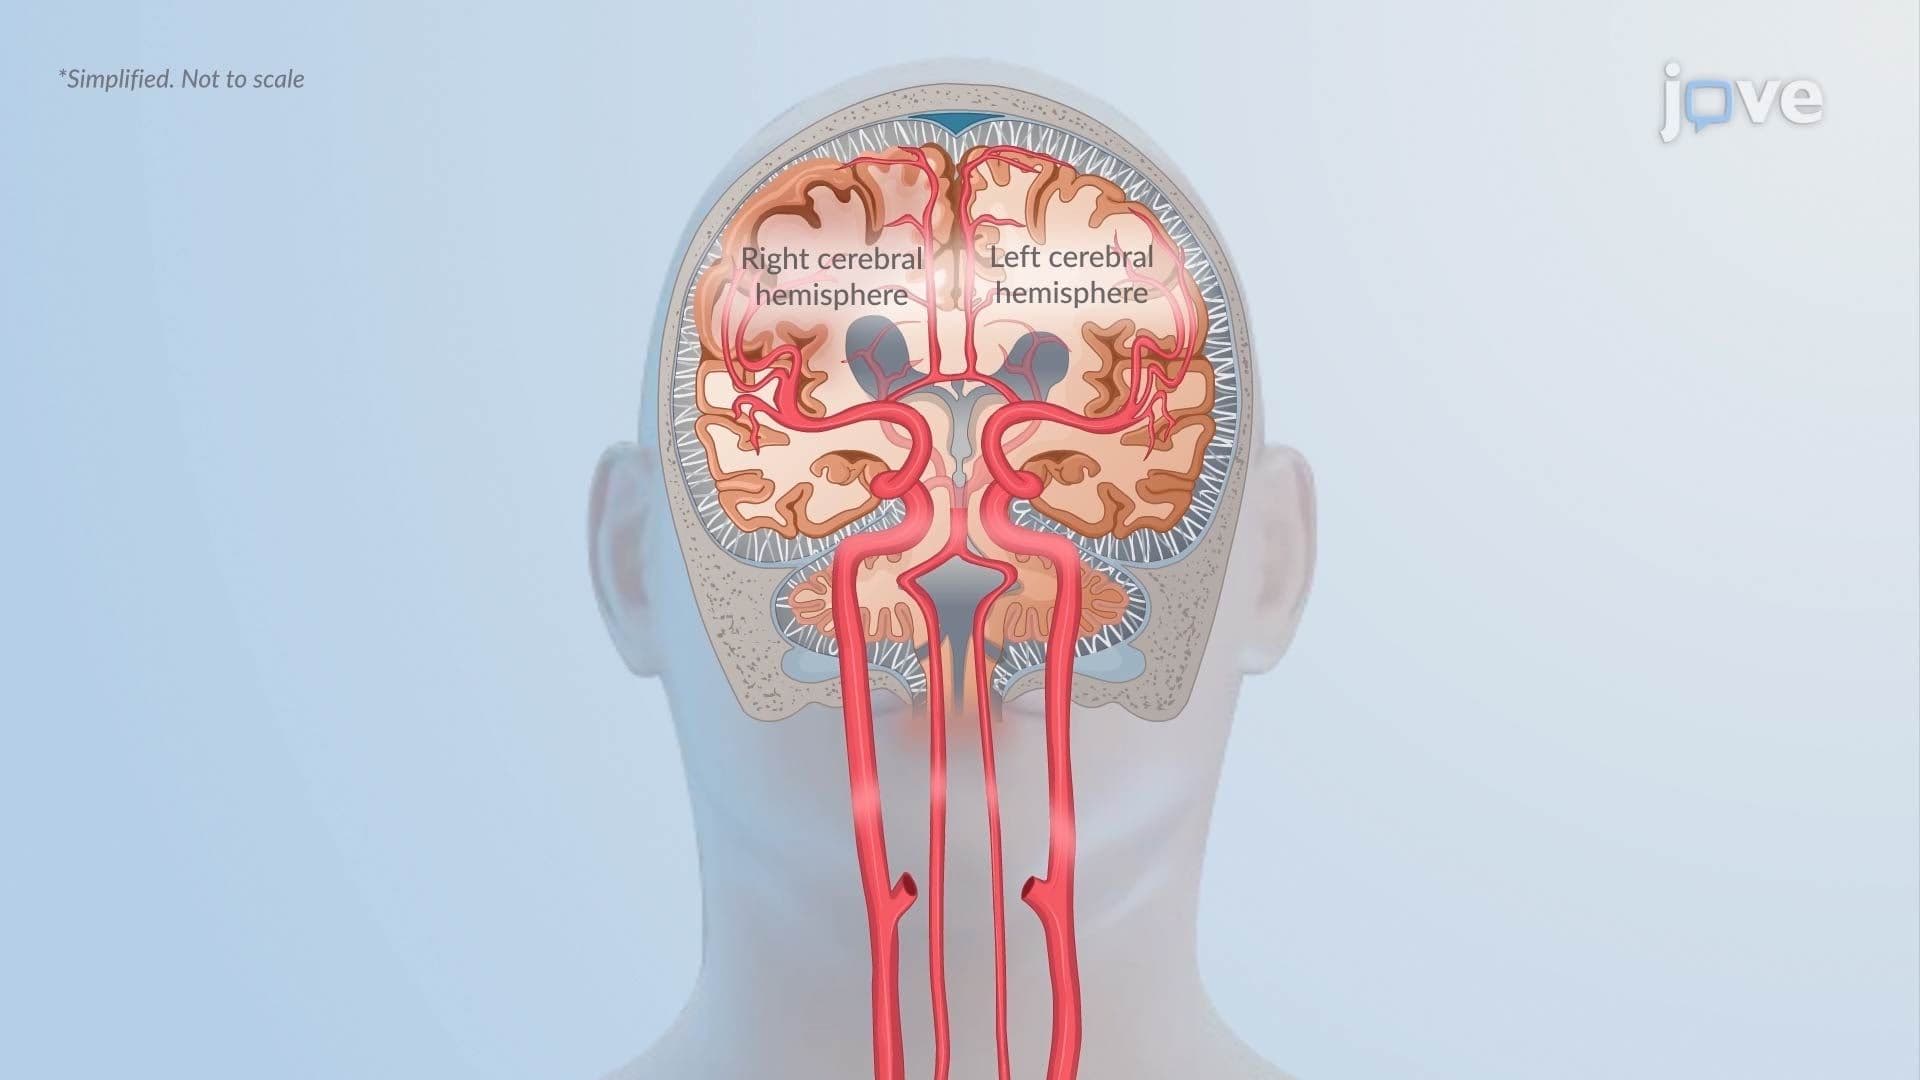
Increased Intracranial Pressure ll: Pathophysiology