Quantitative Analysis of Injection Speed During Endoscopic Cyanoacrylate Therapy for Gastric Varices: A Prospective Comparative Study
Related Experiment Video
Updated: Nov 4, 2026
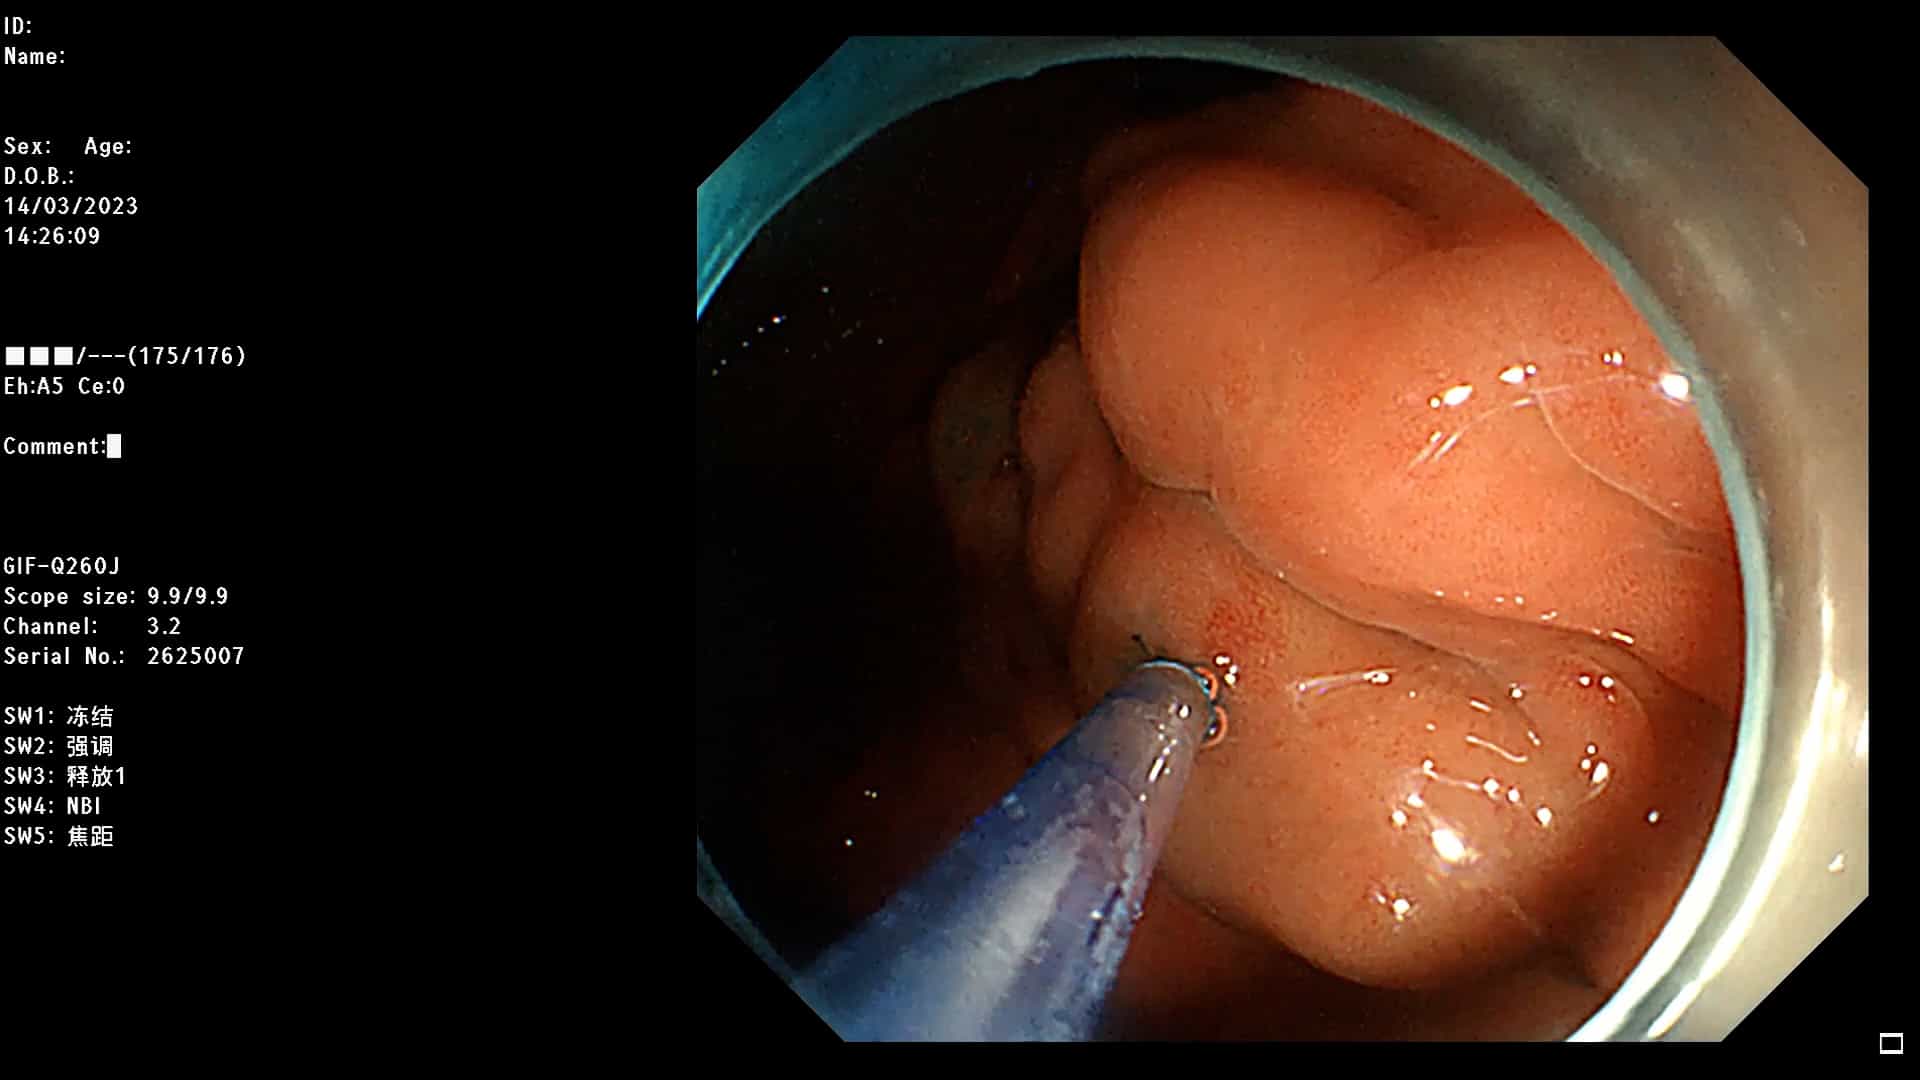
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
Wanyu Ma1, Zhihong Wang, Yingying He
1Department of Gastroenterology, The First Affiliated Hospital of Anhui Medical University, Key Laboratory of Digestive Diseases of Anhui Province, Hefei, Anhui Province, China.

Background And Aims:
Endoscopic cyanoacrylate (CYA) injection is the standard treatment for bleeding gastric varices (GV); however, the optimal injection speed remains undefined. Rapid, high-pressure injection is traditionally recommended to prevent needle blockage, yet clinical observations suggest that excessive speed may increase intraoperative adverse events. This prospective comparative study quantitatively evaluated the effect of injection speed on the efficacy and safety of endoscopic CYA therapy for gastric varices.
Methods:
A total of 175 CYA injection sessions were performed in 160 cirrhotic patients with gastric varices (GOV or isolated gastric varices type 1) across 4 tertiary hospitals. Patients were prospectively allocated into 2 groups according to the preset injection protocol: 1. Rapid-injection group (n=84): 0.5 mL CYA delivered in ≤1 second (≥0.5 mL/s). 2. Slow-injection group (n=91): 0.5 mL CYA delivered over 3 to 5 seconds (0.1 to 0.17 mL/s). The primary outcome was intraoperative adverse events (needle-site bleeding, glue extravasation, submucosal bulging). Secondary outcomes included clinical success, technical success, early rebleeding (≤6 wk), 12-month cumulative rebleeding rate, mortality rate, and rebleeding-free survival. Predictive factors for adverse events were analyzed using univariate and multivariate logistic regression, and Kaplan-Meier analysis was used to estimate rebleeding-free survival.
Results:
Overall clinical success was 100%. Adverse events occurred significantly more often in the rapid-injection group (19.0% vs. 1.1%, P<0.01), primarily due to glue extravasation and mucosal bulging. The overall technical success rate was 90.3% (158/175). Multivariate analysis identified rapid injection speed (OR=19.59, 95% CI: 2.51-152.80, P=0.005) and variceal diameter ≥2 cm (OR=3.58, 95% CI: 1.21-10.59, P=0.021) as independent predictors of intraoperative adverse events. Kaplan-Meier analysis demonstrated a significantly lower rebleeding-free survival in the rapid-injection group (Log-rank P=0.018). During follow-up, 1 patient in the rapid-injection group died of hemorrhagic shock secondary to postoperative early rebleeding. No cases of ectopic embolization or procedure-related mortality were observed.
Conclusions:
Quantitative assessment of CYA injection rate revealed that rapid, high-pressure injection (≥0.5 mL/s) substantially increased the risk of intraoperative adverse events without improving hemostatic efficacy. A controlled, slower injection rate (0.1 to 0.17 mL/s) provides comparable clinical success with superior safety and lower rebleeding risk. This study highlights injection velocity as a modifiable procedural parameter that should be standardized to optimize CYA therapy for gastric varices.