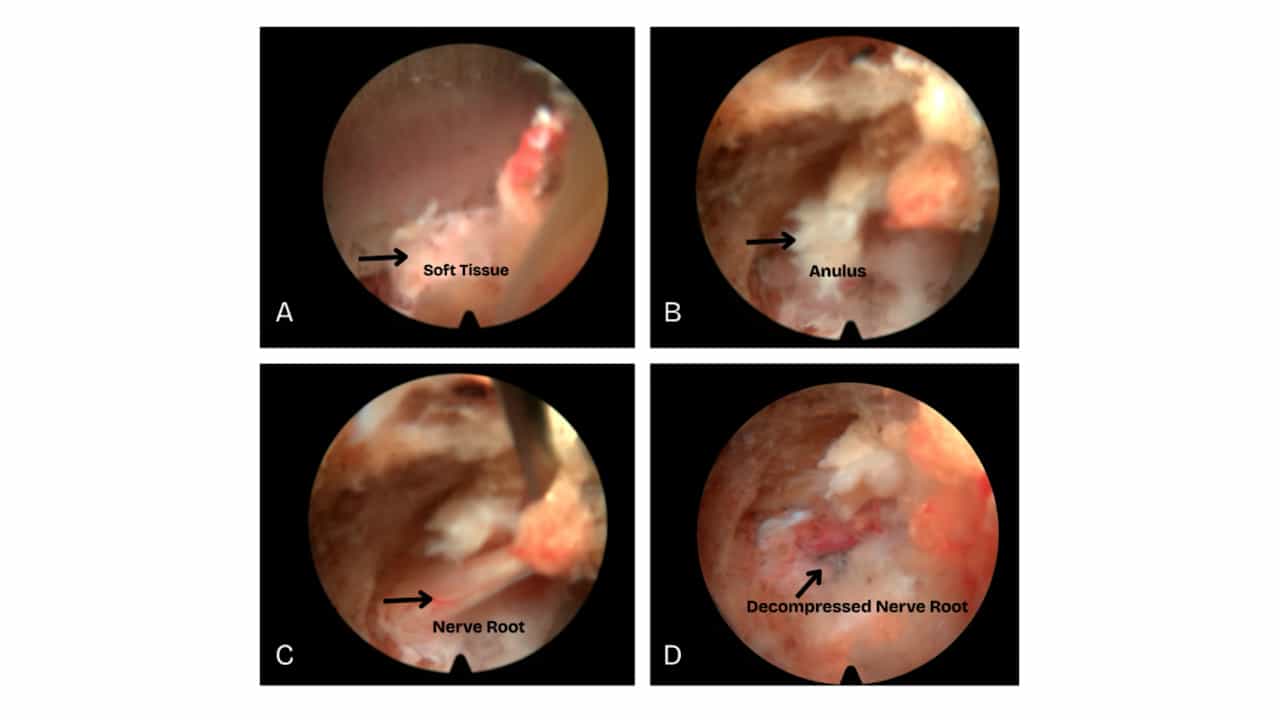
A Multicenter Prospective Study of Patient Outcomes After Three Full-Endoscopic Lumbar Decompression Techniques
Related Experiment Video
Updated: Nov 4, 2026
Percutaneous Endoscopic Unilateral-Approach Bilateral Decompression for Lumbar Spinal Stenosis
Published on: February 9, 2024
Guihe Yang1, Zheng Zhang1, Yuqi Ge1
1Department of Spine Surgery, Beijing Jishuitan Hospital, Capital Medical University, Beijing, 10000, China.

Study Design:
Multicenter prospective observational study.
Objective:
To characterize the application and outcome profiles of TELD, IELD, and UBE in routine clinical practice.
Summary Of Background Data:
Full-endoscopic lumbar surgery has been widely used in the treatment of lumbar disc herniation, yet multicenter prospective evidence on patient outcomes in real-world clinical practice remains limited.
Methods:
This multicenter prospective real-world study was conducted across 10 medical centers in four regions of China. Perioperative parameters, complications, and patient-reported outcome measures at postoperative day 1 and at 3, 6, and 12 months were recorded. Descriptive group comparisons were supplemented by adjusted repeated-measures analyses accounting for baseline outcome values, clinical covariates, operative level, and center.
Results:
A total of 623 patients were included: 105 in the TELD group, 109 in the IELD group, and 409 in the UBE group. Preoperative pain intensity, operative-level distribution, sensory deficit, and center distribution differed among groups. In adjusted analyses, TELD was associated with lower back-pain VAS than UBE at 3 months (mean difference, -0.73; 95% CI, -1.06 to -0.40; Holm P<0.001), 6 months (-0.51; -0.82 to -0.21; P=0.005), and 12 months (-0.77; -0.96 to -0.57; P<0.001). These differences were below the 3-point VAS MCID.
Conclusions:
TELD, IELD, and UBE were associated with favorable safety and midterm outcomes in this multicenter cohort. TELD was associated with modestly lower postoperative back-pain scores than UBE after adjustment for measured differences; however, the absolute differences did not reach the prespecified MCID and do not establish causal or universal procedural superiority.
Level Of Evidence:
Level 3.