Antithrombotic Therapy After Left Atrial Appendage Occlusion: The SIMPLAAFY Randomized Clinical Trial
Related Experiment Video
Updated: Nov 4, 2026
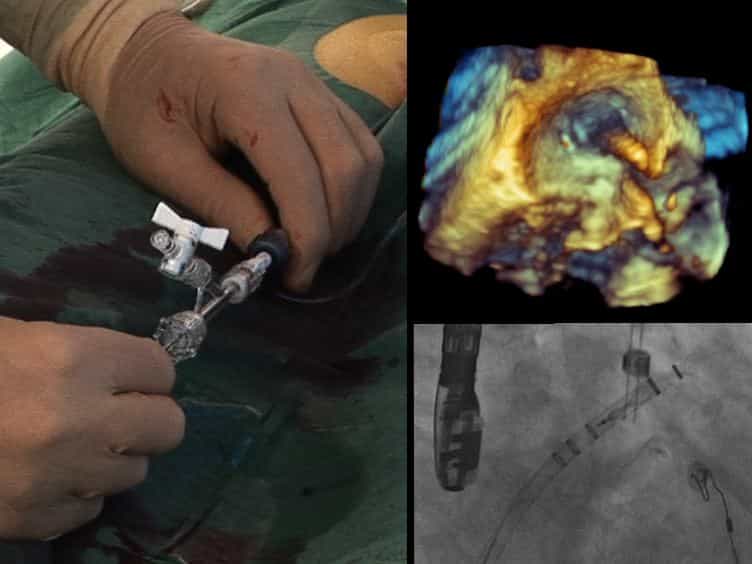
Catheter Ablation in Combination With Left Atrial Appendage Closure for Atrial Fibrillation
Published on: February 26, 2013
Vivek Y Reddy1, Walid I Saliba2, Thomas Waggoner3
1Helmsley Trust Electrophysiology Center, Mount Sinai Fuster Heart Hospital, Icahn School of Medicine at Mount Sinai, New York, New York.

Importance:
Following a left atrial appendage closure (LAAC) procedure, antithrombotic therapy is administered to safely allow time for device endothelialization. However, the optimal postimplant antithrombotic regimen is unknown.
Objective:
To determine if either reduced-dose non-vitamin K oral anticoagulants (NOACs) or aspirin alone are noninferior to dual antiplatelet therapy (DAPT) for the composite clinical end point of death, stroke, systemic embolism, or major bleeding through 6 months post LAAC.
Design, Setting, And Participants:
This open-label, 3-group, multicenter clinical trial randomized 1857 patients between October 2024 and December 2025 at 87 US investigational sites, with the final 6-month follow-up in July 2026. Enrolled patients had nonvalvular atrial fibrillation, underwent successful LAAC, and were eligible for all 3 regimens.
Interventions:
Patients were randomly allocated 1:1:1 to DAPT for 6 months followed by aspirin (n = 624), a reduced-dose NOAC for 3 months followed by aspirin (n = 620), or aspirin alone for 12 months (n = 613).
Main Outcomes And Measures:
The primary outcome was the 6-month composite of all-cause death, stroke, systemic embolism, or major bleeding. Noninferiority was tested in the primary analysis population with a 1-sided Farrington-Manning test (α = .025). Bleeding and 45-day device-related thrombus rates were exploratory without multiplicity adjustment.
Results:
The cohort had a mean age of 76 (SD, 8) years, 42.9% were female, the mean CHA2DS2-VASc score was 4.2 (SD, 1.3), and 68.0% had paroxysmal atrial fibrillation. The primary outcome occurred in 41 patients (6.9%) with DAPT vs 31 (5.1%) with a reduced-dose NOAC (risk ratio, 0.75 [95% CI, 0.48-1.18]; risk difference, -1.7 percentage points; 97.5% upper bound, 1.2) and 20 (3.3%) with aspirin alone (risk ratio, 0.49 [95% CI, 0.29-0.82]; risk difference, -3.5 percentage points; 97.5% upper bound, -0.8). Both monotherapy strategies met noninferiority criteria (P < .001 for noninferiority for both). Major bleeding was 4.5% with DAPT, 2.7% with reduced-dose NOACs, and 1.7% with aspirin alone; clinically relevant nonmajor bleeding was 8.7%, 4.8%, and 3.8%, respectively. Device-related thrombus was observed in 3.4%, 0.9%, and 2.7%, respectively.
Conclusions And Relevance:
Both reduced-dose NOACs and aspirin alone were noninferior to DAPT for 6-month outcomes after uncomplicated LAAC.
Trial Registration:
ClinicalTrials.gov Identifier: NCT06521463.
