Aortic Valve Replacement in Patients 50-65 Years: A Target Trial Emulation
Related Experiment Video
Updated: Nov 4, 2026
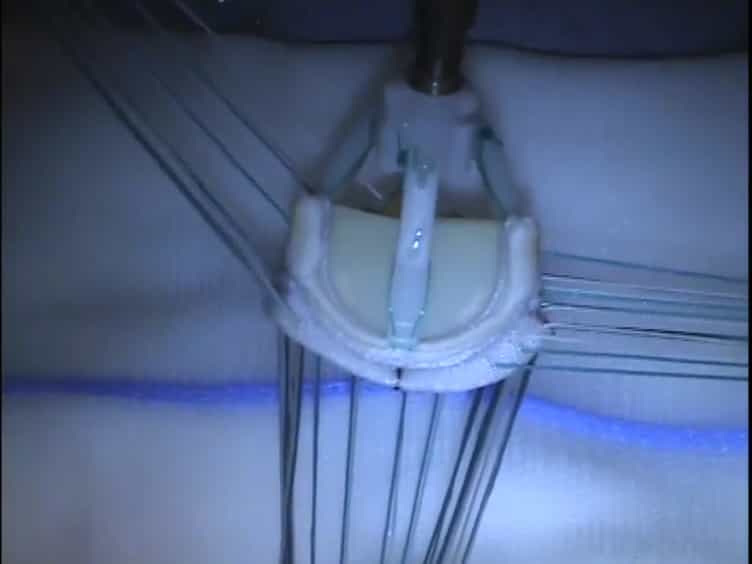
Technique and Patient Selection Criteria of Right Anterior Mini-Thoracotomy for Minimal Access Aortic Valve Replacement
Published on: March 26, 2018
J Hunter Mehaffey1, Stanley B Wolfe1, Raymond J Strobel2
1Department of Cardiovascular and Thoracic Surgery, West Virginia University, Morgantown, West Virginia.

Background:
Guidelines favor surgical aortic valve replacement (SAVR) in patients aged 65 years or younger with aortic stenosis, yet many receive transcatheter aortic valve implantation (TAVI) without supportive data. We performed a target trial emulation of SAVR versus TAVI in this population.
Methods:
Using the all-payer Premier Healthcare Database (2016-2024), patients aged 50 to 65 years undergoing isolated SAVR or TAVI within 90 days of an aortic stenosis diagnosis were evaluated. After trial exclusions, frailty and predicted risk were incorporated into a clone-censor-weight framework with inverse probability weighting. Reporting adhered to TARGET guidance. The primary outcome was the 5-year composite of all-cause mortality, stroke, valve reintervention, or heart failure rehospitalization.
Results:
The clone-censor-weighted analysis included 18,549 SAVR and 18,549 TAVI patients, balanced across all covariates (standardized mean difference <0.10). Mean age was 60 years, and many were of low surgical risk <4% (SAVR 69.5% vs TAVI 49.7%). In-hospital mortality (0.41% vs 0.31%; odds ratio, 0.61; p<0.001) and periprocedural stroke (0.31% vs 0.28%; odds ratio, 0.67; p<0.001) favored TAVI. At 5 years, risk-adjusted freedom from the primary composite outcome (87.5% vs 77.8%; hazard ratio, 1.87; p<0.001), heart failure rehospitalization (92.9% vs 88.2%; subdistribution hazard ratio, 1.72; p<0.001), and all-cause mortality (93.6% vs 85.6%; hazard ratio, 2.34; p<0.001) favored SAVR.
Conclusions:
For contemporary patients aged 50 to 65 years, the primary composite outcome favored SAVR over TAVI at 5 years, most markedly at centers with high young TAVI utilization. These data may guide heart team decision making and future trial design.
Related Concept Videos
 01:25
Aortic Regurgitation III: Medical Management
 01:15
Aortic Regurgitation I: Introduction
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:27
Mitral Valve Prolapse I: Introduction
 01:22
Mitral Stenosis I: Introduction
 01:26
Mitral Stenosis III: Medical Management