Infection and abduction loss predict equine laryngoplasty failure
Related Experiment Video
Updated: Nov 4, 2026
Surgical Closure of Equine Abdomen, Prevention, and Management of Incisional Complications
Published on: May 10, 2024
M Lahuerta1, D Argüelles2, F Rossignol3
1Department of Animal Medicine and Surgery, Universidad CEU-Cardenal Herrera, CEU Universities, Valencia, Spain.

Background:
Prosthetic laryngoplasty (PL) is the most common surgical treatment for recurrent laryngeal neuropathy (RLN) in horses. Post-operative complications may compromise outcomes, and the influence of breed and anaesthetic approach remains unclear.
Objectives:
To evaluate factors associated with surgical outcome at 3 months following PL, focusing on post-operative complications, anaesthetic modality and breed (particularly Iberian baroque breeds).
Study Design:
Multicentre retrospective cohort study.
Methods:
Medical records from 181 horses across 7 equine hospitals using the same standardised surgical technique were reviewed. Variables including breed, anaesthesia type, ventriculocordectomy (VeC) method and post-operative complications were analysed using χ2 or Fisher's exact tests and Spearman correlation. Two binomial generalised linear mixed models, with surgeon as a random effect, evaluated pre/intra-operative predictors and post-operative prognostic factors. Level of significance p < 0.05. Surgical success was defined as the absence of respiratory noise and exercise intolerance at 3 months.
Results:
Surgical success was achieved in 79.1% of cases. Complications occurred in 33.7% of horses and were negatively associated with treatment success (odds ratio [OR] 0.003; 95% confidence interval [CI] 0.000-0.052; p < 0.001). Major loss of arytenoid abduction (18.2%) and surgical site infection (SSI; 6.6%) were the only variables independently associated with reduced odds of treatment success in the post-operative model (OR 0.011; 95% CI 0.001-0.178; p = 0.001 and OR 0.046; 95% CI 0.004-0.559; p = 0.016, respectively). Breed was not associated with surgical outcome.
Main Limitations:
The retrospective multicentre design may introduce selection bias, variability in clinical practice and heterogeneous follow-up.
Conclusions:
Major loss of arytenoid abduction and SSI were the strongest predictors of failure, highlighting the importance of meticulous technique, preservation of arytenoid abduction and rigorous infection control to optimise outcomes after PL.

Related Concept Videos
 01:24
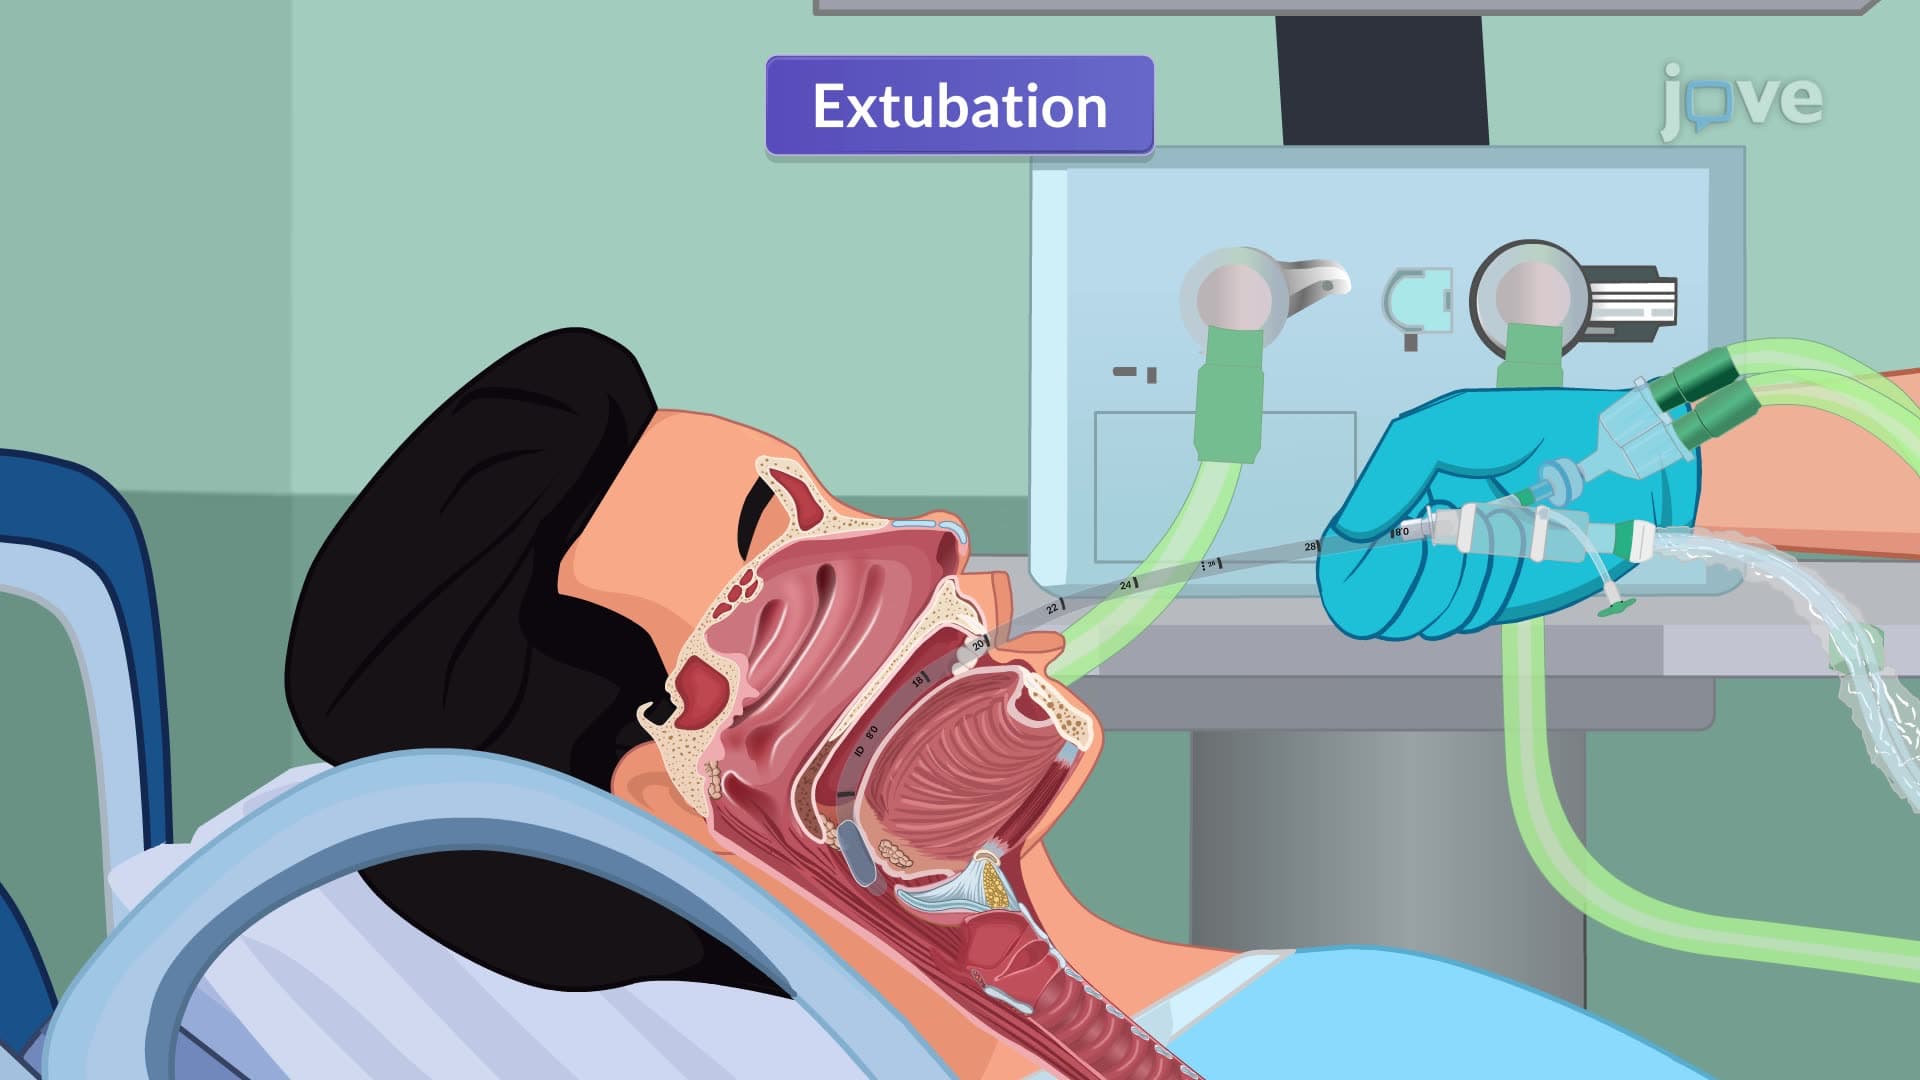
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques