Resuscitation and 30-day postoperative mortality in acute type A aortic dissection: A cohort study
Related Experiment Video
Updated: Nov 4, 2026
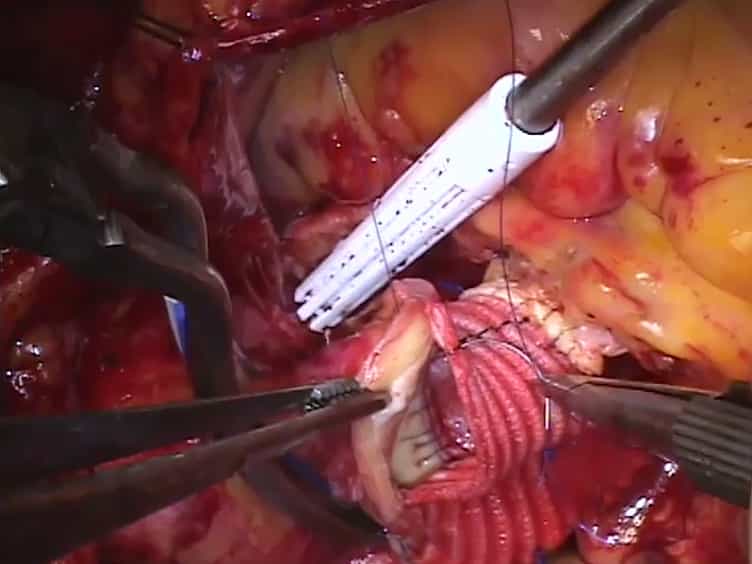
Standardized Technique of Aortic Valve Re-implantation for Valve-sparing Aortic Root Replacement
Published on: December 11, 2017
Soichiro Kageyama1, Takeki Ohashi2, Masahiko Kuinose1
1Department of Surgery, Kawasaki Medical School General Medical Center, Kita-ku, Okayama-city, Okayama, Japan.

Objectives:
Patients with acute type A aortic dissection who experience cardiopulmonary arrest require cardiopulmonary resuscitation before definitive repair, but the prognostic relevance of its duration is unclear. We evaluated the association between resuscitation duration and early mortality after emergency surgery.
Methods:
In this retrospective two-centre study, we included all adults who underwent emergency surgery for acute type A aortic dissection. The exposure was the combined preoperative and intraoperative duration of resuscitation until return of spontaneous circulation or initiation of extracorporeal membrane oxygenation or cardiopulmonary bypass, categorised a priori as none, <15 min or ≥ 15 min. Multilevel proportional hazards models and competing-risks regression, with multiple imputation of missing covariates, were used.
Results:
Of 880 patients, 815 (92.6%), 13 (1.5%), and 52 (5.9%) received no resuscitation, resuscitation for <15 min and resuscitation for ≥15 min, respectively (median recorded duration 29 min, interquartile range 15-43). Thirty-day mortality was 81/815 (9.9%), 3/13 (23.1%) and 42/52 (80.8%), respectively. Resuscitation for ≥15 min was associated with higher 30-day mortality (adjusted hazard ratio 9.59, 95% confidence interval 4.28-21.45; P < 0.001), whereas the estimate for resuscitation for <15 min was imprecise (adjusted hazard ratio 1.68, 95% confidence interval 0.46-6.13; P = 0.43).
Conclusions:
Among patients selected for emergency surgery for acute type A aortic dissection, combined preoperative and intraoperative resuscitation for ≥15 min was associated with higher 30-day mortality, and the risk increased with resuscitation duration. These findings provide prognostic information rather than a criterion for withholding surgery.
Related Concept Videos
 01:26
Aneurysm III: Interprofessional Care
 01:15
Aortic Regurgitation I: Introduction