When imaging misleads: Severe bulbar myasthenia gravis with a concomitant tectal lesion: A case report
Related Experiment Video
Updated: Nov 4, 2026
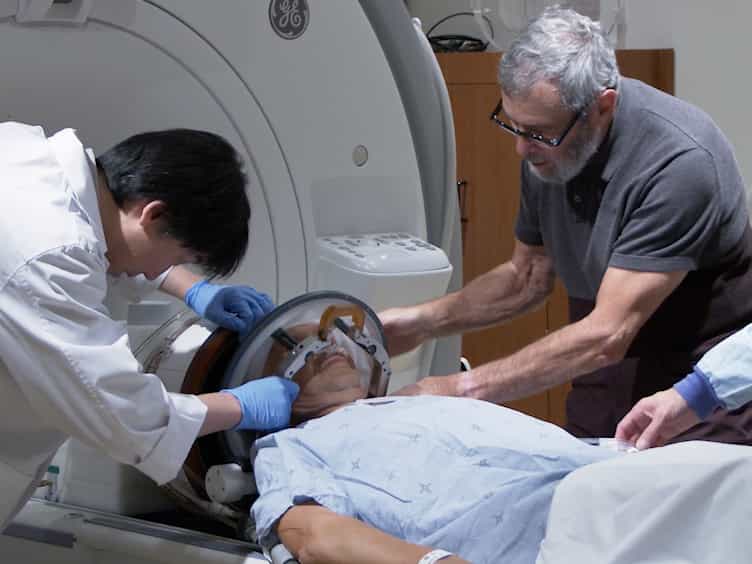
MRI-guided Focused Ultrasound Thalamotomy for Patients with Medically-refractory Essential Tremor
Published on: December 13, 2017
Kleber Orlando Mosquera Rodriguez1, María de Los Ángeles Álvarez Falcón1, Juan Carlos Moreira Holguín2
1Clinical Research Trainee, Department of Neurosurgery, Hospital de Especialidades, Guayaquil, Ecuador.

Background:
Myasthenia gravis (MG) may present with prominent oculobulbar symptoms overlapping with structural brainstem disorders, creating a diagnostic challenge when neuroimaging reveals a potentially explanatory lesion. We report generalized MG with severe bulbar involvement and a concomitant tectal lesion.
Case Description:
A 23-year-old woman with autoimmune thyroiditis presented with a 4-5-month history of ptosis, diplopia, dysarthria, nasal speech, dysphagia, proximal weakness, fatigability, and episodic dyspnea. Examination revealed fatigable bilateral ptosis, facial and masticatory weakness, severe bulbar dysfunction, bilateral tongue weakness with fasciculations, cervical weakness, and symmetric proximal limb weakness, without sensory, cerebellar, or pyramidal abnormalities. Brain magnetic resonance imaging demonstrated a small left tectal fluid-attenuated inversion recovery-hyperintense lesion without contrast enhancement or significant mass effect, initially suggesting a low-grade structural lesion. However, the extensive bilateral, fluctuating, and fatigable syndrome was discordant with this finding. Anti-acetylcholine receptor antibodies were positive (2.48 nmol/L), supporting generalized MG. Treatment with pyridostigmine, corticosteroids, intravenous immunoglobulin, and azathioprine produced progressive improvement. One year later, a respiratory infection precipitated a myasthenic crisis requiring intensive care, followed by recovery. At follow-up, she remained stable without dysphagia or dyspnea, while the tectal lesion was managed conservatively.
Conclusion:
This case highlights the risk of diagnostic anchoring on neuroimaging abnormalities. Careful clinicoradiological correlation, particularly recognition of anatomical discordance and fatigability, is essential before attributing a complex bulbar syndrome to a structural brainstem lesion.
Related Concept Videos
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...
 01:22
Myasthenia Gravis ll: Pathophysiology
 01:28
Disorders of the Skeletal Muscle
Musculoskeletal disorders
Musculoskeletal disorders involve injuries and conditions affecting the skeletal muscles and associated connective tissues. These disorders can arise from acute biomechanical stresses or chronic overuse and can occur across different age groups. Common injuries include sprains, fractures, and muscular strains, often resulting from...