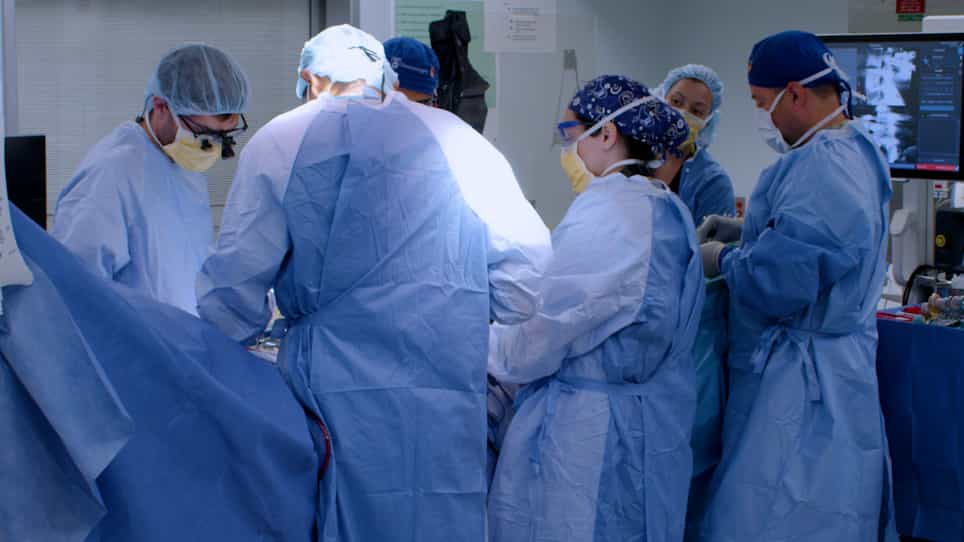
A Synchronized Two-Surgeon Workflow for Two-Level Unilateral Biportal Endoscopic Transforaminal Lumbar Interbody Fusion: Technical Note and Preliminary Case Series
Related Experiment Video
Updated: Nov 5, 2026
Uniportal Full Endoscopic Posterolateral Transforaminal Lumbar Interbody Fusion
Published on: June 6, 2025
Jixiang Zhang1, Zongjiang Wang1, Huiquan Li1
1Department of Spine Degeneration and Oncology, Weifang People's Hospital, Shandong Second Medical University, Weifang, Shandong, China.

Objective:
To describe a standardized four-phase synchronized two-surgeon workflow for selected two-level unilateral biportal endoscopic transforaminal lumbar interbody fusion (UBE-TLIF) and report its preliminary outcomes.
Methods:
This single-center retrospective Technical Note included 33 consecutive patients (66 operated levels) treated in 2025 by a fixed pair of experienced surgeons. Each surgeon performed endoscopic decompression and interbody fusion at an assigned level, with coordinated fluoroscopy, guidewire staging, shared-device use, and percutaneous instrumentation. Perioperative outcomes, pain and disability scores, 90-day adverse events, and CT-based fusion assessments obtained at least 12 months postoperatively were reviewed.
Results:
All 33 procedures were completed. Mean operative time was 294 ± 59 minutes, estimated blood loss was 299 ± 78 mL, and median spine-surgery ward stay was 7 days (interquartile range, 6-9). Three patients (9.1%) had recorded adverse events: incidental durotomy, wound infection requiring surgical debridement, and anemia requiring transfusion (one each). At a median final clinical follow-up of 427 days, median back- and leg-pain visual analog scale scores decreased from 6 to 1 and from 7 to 0, respectively; median Oswestry Disability Index decreased from 70 to 18 (all Holm-adjusted P < 0.001 versus baseline). CT at ≥12 months was available for 22/25 eligible patients; fusion (Bridwell I/II) was observed in 40/44 evaluable levels (91%) and at both operated levels in 20/22 patients (91%).
Conclusions:
The coordinated workflow was feasible in an experienced fixed surgical pair. Prospective comparative studies are needed to assess efficiency, safety, resource use, and generalizability.