Variation in Procedural Volume and Specialty Distribution at Trauma Centers
Related Experiment Video
Updated: Nov 6, 2026
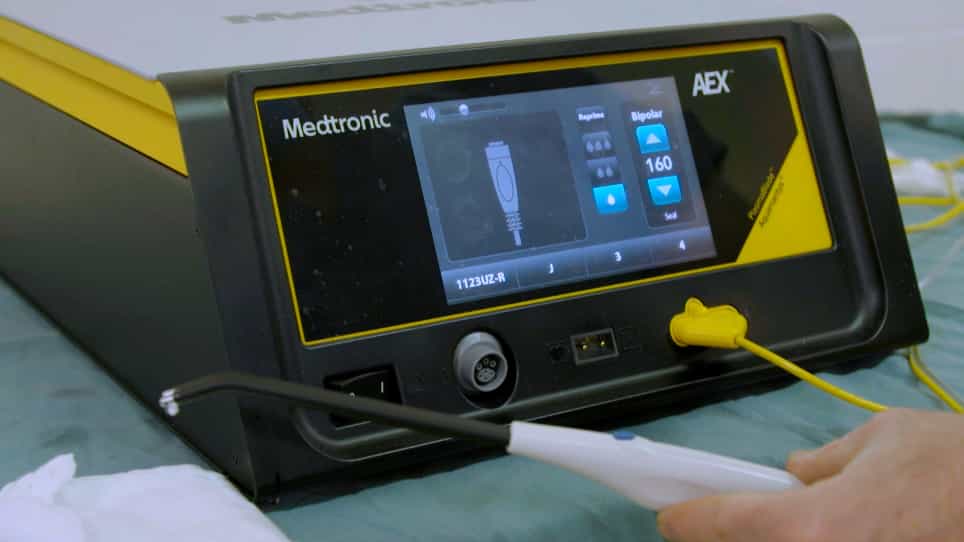
A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Robin M Litten1, Laura J Gerhardinger2, Joey P Johnson1
1Department of Orthopaedic Surgery, University of Alabama, Birmingham, Alabama.

Introduction:
The distribution of procedural workload across specialties and hospital locations at trauma centers has been poorly defined. The purpose of this study was to quantify procedural volume by specialty and hospital location at level I and II trauma centers.
Methods:
A retrospective cohort study was performed using data from a statewide trauma registry (2019-2025). Adult patients (≥18 y) with an Injury Severity Score (ISS) ≥5 who were admitted to a level I or II trauma centers were included. Procedures and procedure clusters (i.e., multiple performed in one setting) were identified using International Classification of Diseases, 10th Revision, Procedure Coding System (ICD-10-PCS) codes and categorized by provider specialty and hospital location, including the operating room (OR), emergency department, intensive care unit, and other settings.
Results:
There were 401,063 individual procedures and 238,436 procedure clusters identified in 117,518 patients. Orthopedic surgery performed the largest share of procedures (146,932, 36.6%) and procedure clusters (84,917, 35.6%) and did four to six times the number of OR-based procedures than either general trauma surgery or neurosurgery/spine surgery respectively. General trauma surgery performed the most intensive care unit procedures and nonsurgical providers did the most in the emergency department. Level I centers performed more operations per hospital than level II centers, but collectively level II centers accounted for a greater aggregate operative burden.
Conclusions:
Orthopedic surgery accounted for the largest share of procedures in trauma centers, whereas other specialties performed most of the procedures outside of the OR. Understanding these patterns may help trauma centers allocate resources to better match the location of actual procedural demand.

