Objectively measured nursing time for structured CAM-ICU delirium screening: A single-Centre observational study
Related Experiment Video
Updated: Nov 6, 2026
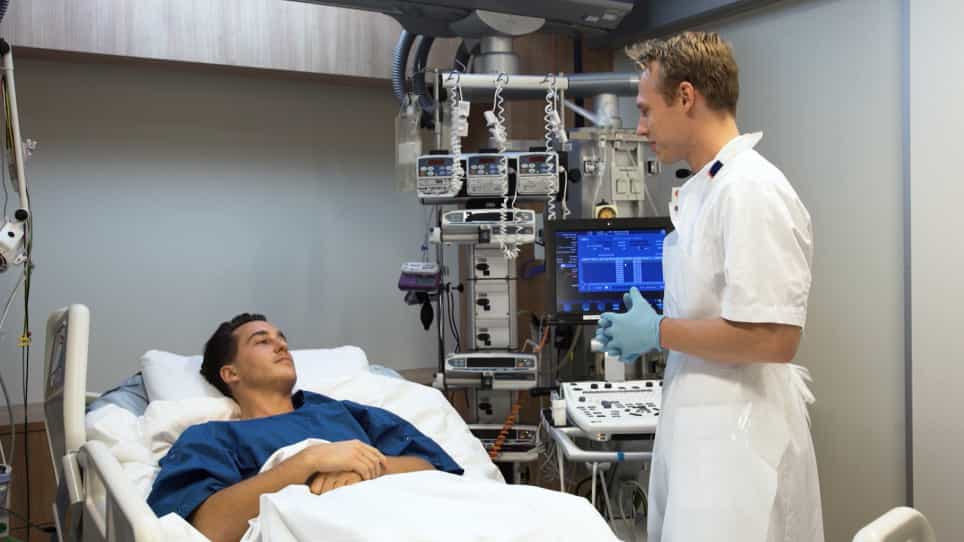
Observational Study Protocol for Repeated Clinical Examination and Critical Care Ultrasonography Within the Simple Intensive Care Studies
Published on: January 16, 2019
Maximilian Niederer1, Mathias Bader1, Sascha Hammer1
1Department of Anaesthesiology and Intensive Care, Medical University of Graz, Graz, Austria.

Objectives:
To describe, using objectively captured system timestamps, the time nurses require to perform structured Confusion Assessment Method for the Intensive Care Unit (CAM-ICU) delirium assessments, and to examine whether duration varies by unit, shift, or delirium status.
Methods:
Planned secondary analysis of a prospective, controlled pilot cohort study conducted across three perioperative/anaesthesiology-led intensive care units (ICUs) within a single university medical centre. During predefined "structured assessment weeks," CAM-ICU was performed twice daily; nurses manually pressed start/stop buttons within the clinical documentation system. Assessment duration was analysed descriptively and compared across ICU, shift, and CAM-ICU result using the Mann-Whitney U test; a mixed-effects linear model accounted for repeated measurements within patients.
Results:
1433 structured CAM-ICU assessments were analysed in 317 patients (median 2 assessments per patient, interquartile range [IQR] 1-5). Median assessment duration was 1 min (IQR 1-2, mean 1.6 ± 1.4, range 0-10). Duration did not differ significantly by ICU (p = 0.057), shift (p = 0.073), or CAM-ICU result (p = 0.192), and no covariate remained associated with duration after accounting for within-patient clustering.
Conclusions:
When embedded in routine workflow and supported by an integrated documentation system, structured CAM-ICU screening was consistently brief across units, shifts, and patient acuity, objectively confirming the lower end of previously reported estimates; confidence intervals around subgroup differences were narrow enough to exclude clinically relevant differences on the order of one minute or more.
Implications For Clinical Practice:
Perceived time burden may be a less decisive, stand-alone barrier to structured delirium screening than previously assumed. Units considering reduced screening frequency on time-burden grounds should first collect local, objective time data, and should prioritise streamlined documentation and sustained training over shortening the assessment itself. In this cohort, structured CAM-ICU screening took a median of only one minute per assessment.