Persistent Axillary Lymph Node Dissection After Nodal Downstaging in Node-Positive Breast Cancer: Surgical Context and Early Morbidity
Related Experiment Video
Updated: Nov 6, 2026
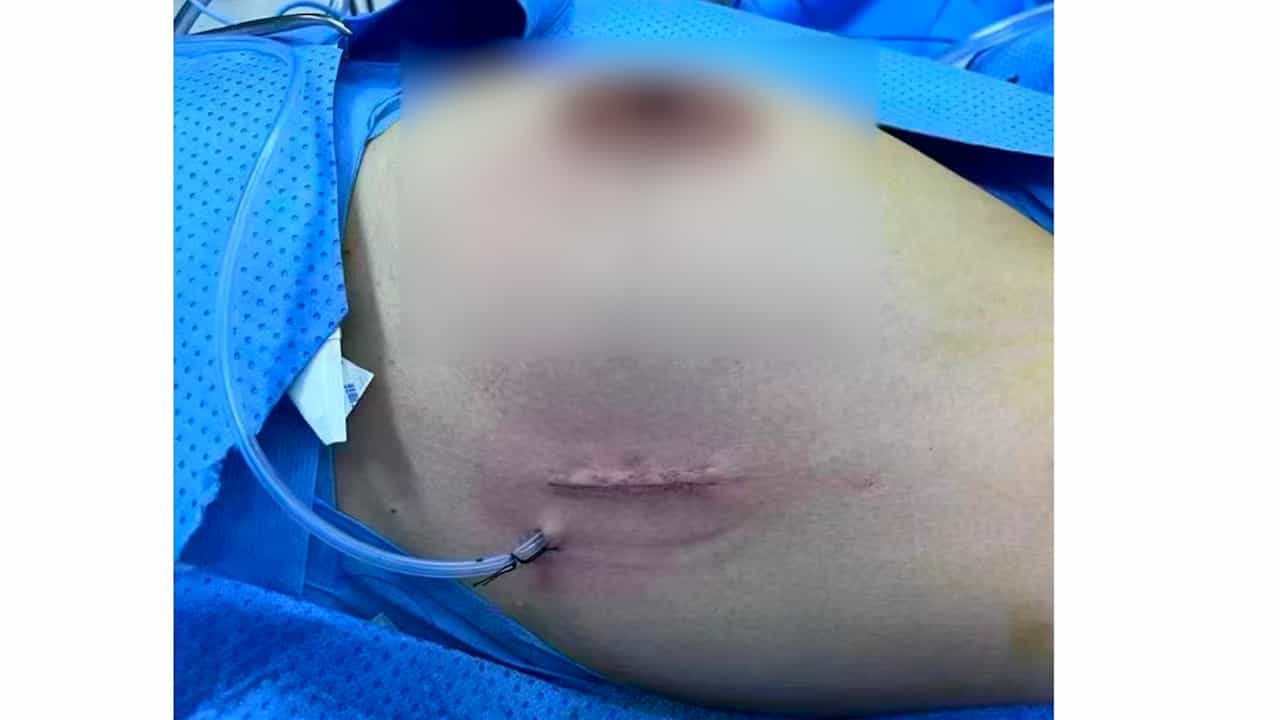
Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Serdar Sarıdemir1, Ali Toprak2, Seda Karaçam3
1Department of Surgical Oncology, Dr. Abdurrahman Yurtaslan Ankara Oncology Training and Research Hospital, University of Health Sciences, Ankara, Türkiye. dr.saridemir@gmail.com.

Purpose:
After neoadjuvant systemic therapy (NST), initially node-positive patients who achieve a nodal pathologic complete response are candidates for axillary de-escalation; however, the real-world persistence of axillary lymph node dissection (ALND), associated operative pathways, and early, procedure-specific morbidity remain incompletely defined.
Methods:
We retrospectively analyzed 335 consecutive patients who were initially node-positive and underwent NST and surgery at a tertiary cancer center; the prespecified primary cohort comprised patients with cN1 and ypN0 disease (n = 173). Axillary surgery was classified as de-escalation (sentinel lymph node biopsy [SLNB] or targeted axillary dissection [TAD] alone) vs. ALND-based surgery, the latter being further categorized as upfront ALND or TAD with ALND; a chart audit documented the clinical context underlying these decisions. Multivariable logistic regression, inverse probability of treatment weighting, Firth-penalized regression, and sensitivity analyses excluding patients who underwent upfront ALND were performed.
Results:
Among 173 patients with cN1/ypN0 disease, 113 (65.3%) underwent de-escalation and 60 (34.7%) underwent ALND-based surgery (upfront ALND, 23; TAD with ALND, 37); no patient met the predefined criteria for unplanned SLNB/TAD-to-ALND conversion. Mastectomy without immediate expander reconstruction was most strongly associated with persistent ALND (adjusted odds ratio [aOR], 8.75; 95% confidence interval [CI], 3.21-23.86). ALND-based surgery was associated with higher odds of any seroma (aOR, 3.85), clinically significant seroma (aOR, 3.91), and prolonged drainage (ratio, 1.37), but not with non-seroma wound complications; these associations persisted after excluding patients who underwent upfront ALND and within the mastectomy stratum. Seroma was numerically more frequent after TAD alone than after SLNB alone, although estimates were imprecise.
Conclusion:
ALND persisted through distinct operative pathways, clustered around mastectomy without immediate reconstruction, and was associated with greater early morbidity, particularly seroma and prolonged drainage. These findings indicate context-dependent variation in axillary management but do not establish that ALND was avoidable in individual patients.
More Related Videos
 13:35
Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024
 03:07
Single-Port Robotic-assisted Transaxillary Breast-conserving Surgery: A Prospective, Single-arm, Non-randomized Phase IIa Clinical Trial
Published on: August 19, 2025