Pre-extubation calculated serum osmolality and early invasive reintubation in critically ill adults: a dual-database study with multicenter external replication
Related Experiment Video
Updated: Nov 6, 2026
Observational Study Protocol for Repeated Clinical Examination and Critical Care Ultrasonography Within the Simple Intensive Care Studies
Published on: January 16, 2019
Weibin Huang1, Jiaxiang Bian1, Youli Chen2
1Department of Critical Care Medicine, Fujian Medical University Union Hospital, Fuzhou, Fujian, China.

Background:
Extubation assessment focuses on respiratory, neurologic, and airway readiness, whereas osmotic-metabolic status has received less attention. We examined whether pre-extubation calculated hyperosmolarity was associated with early invasive reintubation and whether this association replicated across independent critical care databases.
Methods:
We analyzed the first eligible extubation in each hospital admission in MIMIC-IV and independently replicated the analysis in the multicenter eICU-CRD. Calculated serum osmolality was derived from sodium, glucose, and blood urea nitrogen measured within 24 h before extubation. Modified Poisson models estimated adjusted risk ratios (RRs) for 48-h invasive reintubation comparing calculated serum osmolality >300 with ≤300 mOsm/kg, using the same prespecified adjustment set in both databases. Secondary analyses evaluated 72-h reintubation and continuous associations, with additional sensitivity analyses addressing respiratory severity, fluid and renal status, threshold stability, and competing events.
Results:
We included 2,639 eligible extubations in MIMIC-IV, with 317 reintubations, and 1,390 in eICU-CRD, with 93 reintubations. In MIMIC-IV, 48-h reintubation occurred in 13.6% of index extubations with calculated serum osmolality >300 mOsm/kg and 10.8% with values ≤300 mOsm/kg (adjusted RR, 1.31; 95% CI, 1.05-1.62). The association replicated in eICU-CRD, where the corresponding risks were 10.5% and 4.6% (adjusted RR, 1.88; 95% CI, 1.27-2.77). The corresponding adjusted 72-h RRs were 1.25 (95% CI, 1.02-1.52) and 1.53 (95% CI, 1.19-1.97). Additional adjustment for respiratory severity produced little change within the corresponding measured subsets, whereas the continuous association was weaker in MIMIC-IV.
Conclusion:
Pre-extubation calculated hyperosmolarity was associated with a higher risk of early invasive reintubation in two independent critical care databases. It may serve as an adjunctive metabolic-renal marker that complements established extubation assessment.
Related Concept Videos
 01:24
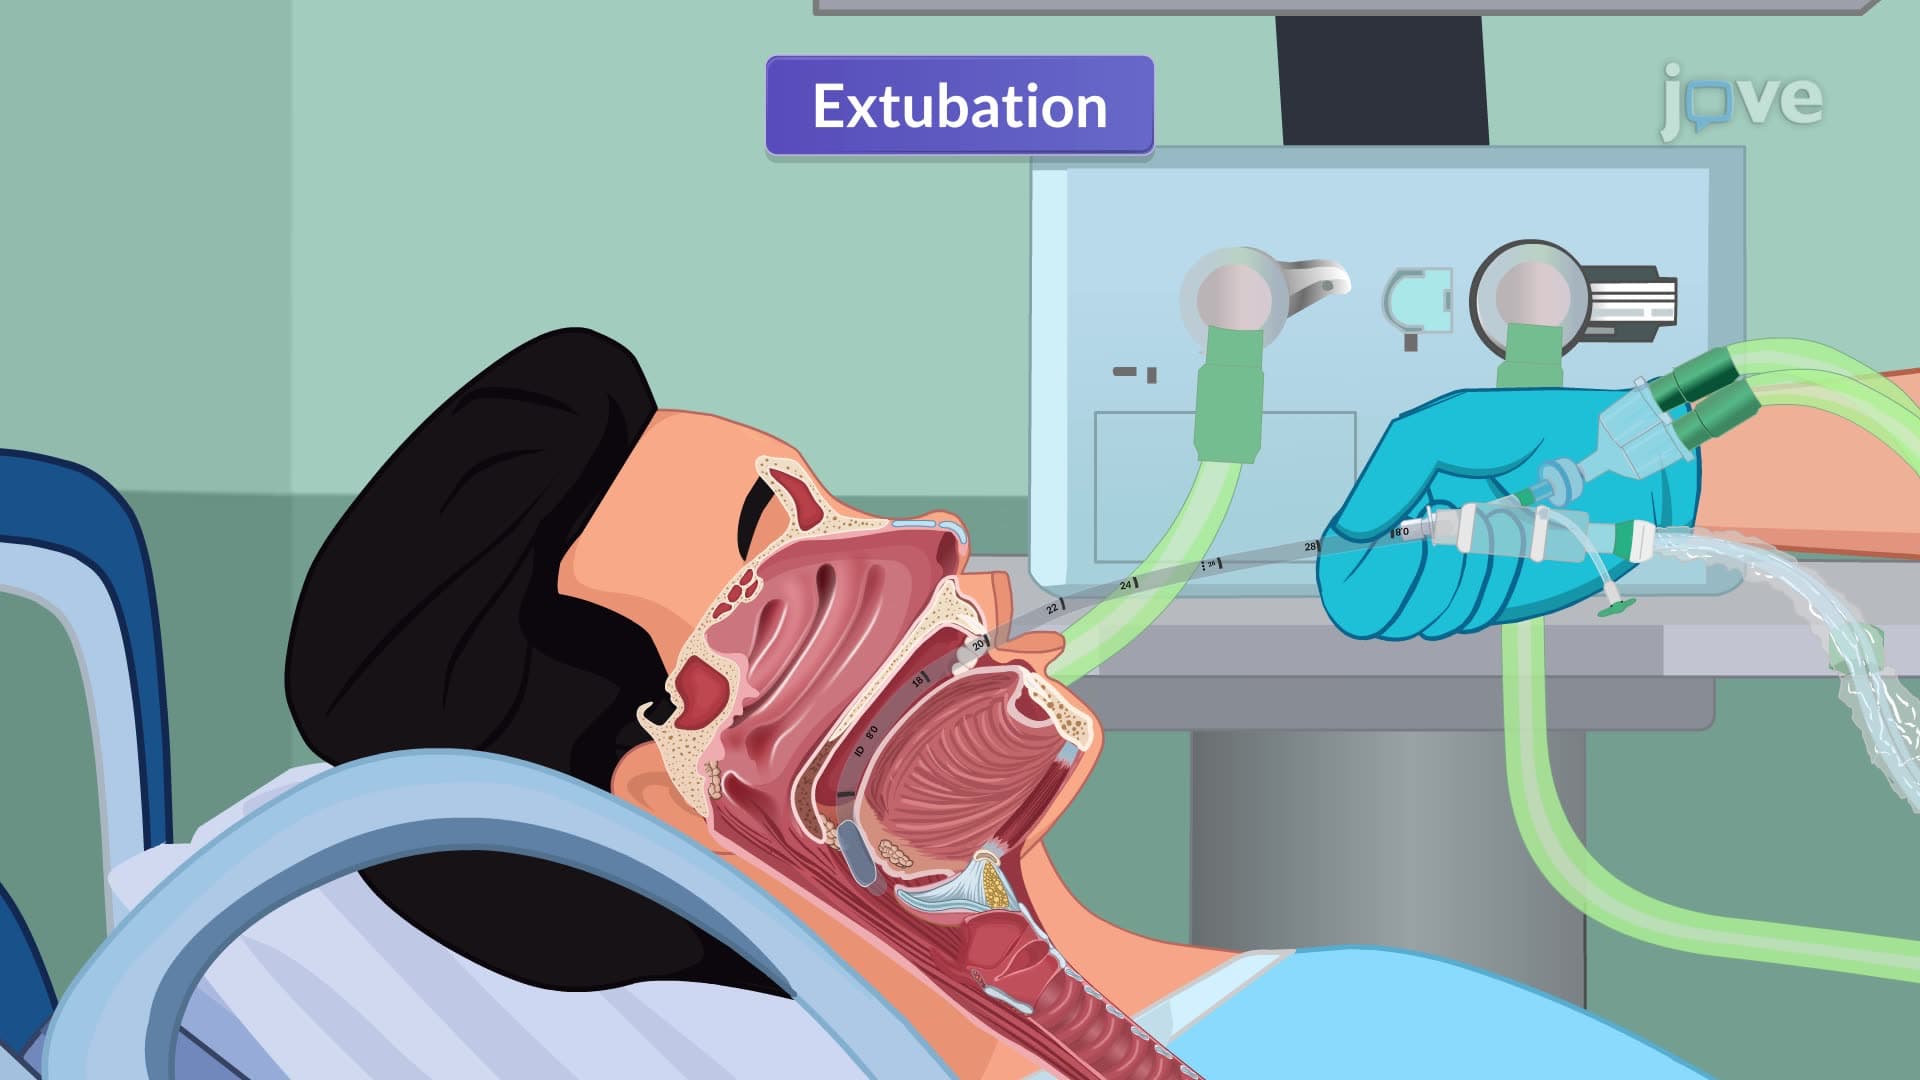
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:17
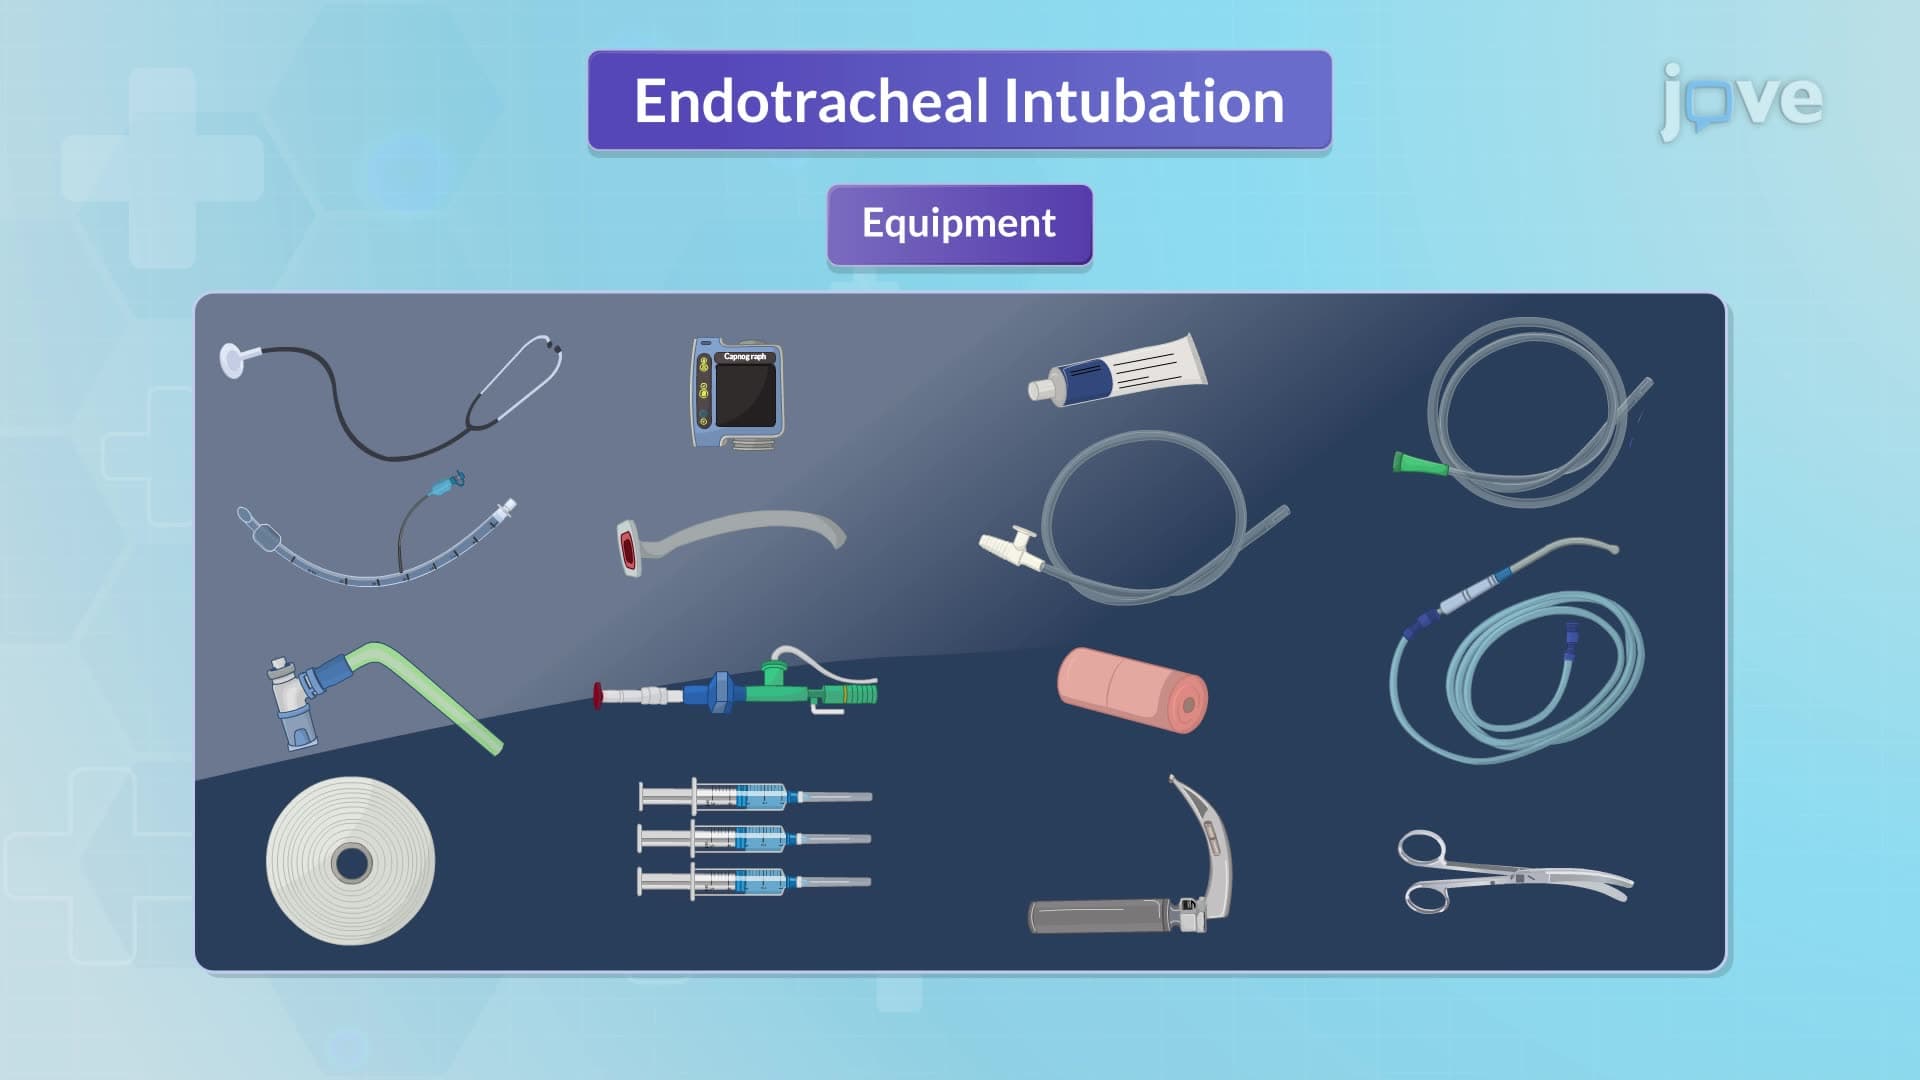
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...