Robotic (minimally invasive) Whipple: Ready for Primetime or experimental pipedream
Related Experiment Video
Updated: Nov 7, 2026
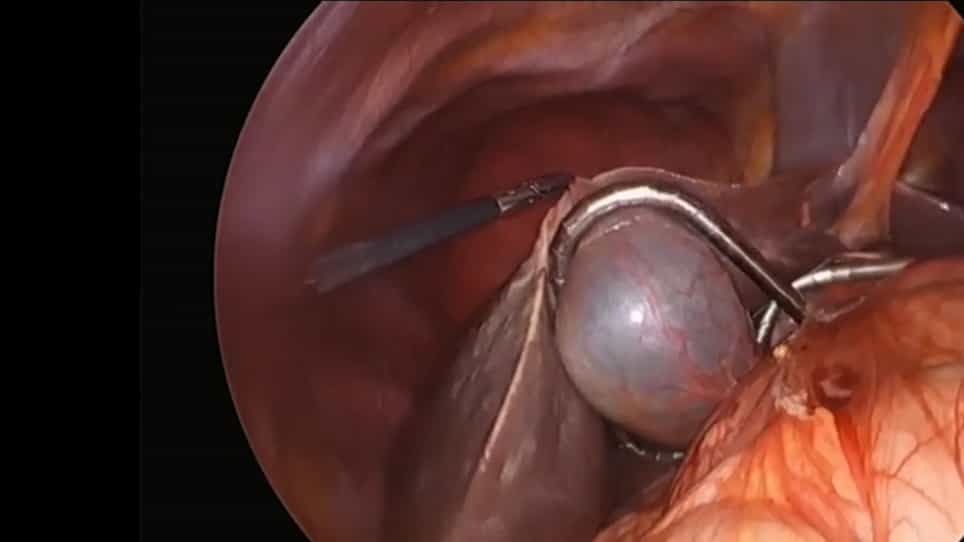
Technical Detail for Robot Assisted Pancreaticoduodenectomy
Published on: September 28, 2019
Micah C May1, Ashley Russell1, Melissa E Hogg2
1University of Chicago, Chicago, IL, USA.

Abstract:
In 1935, Allen Oldfather Whipple performed the first one-stage pancreatoduodenectomy, establishing the foundation for an operation that has since undergone nearly a century of technical refinement. Advances in surgical technique, perioperative care, training, and technology have progressively improved the safety and reproducibility of the pancreatoduodenectomy. More recently, the introduction of minimally invasive approaches-and particularly robotic surgery-has prompted another potential paradigm shift in the operative management of pancreatic disease. As robotic pancreatoduodenectomy (RPD) has expanded over the past decade, an important question has emerged: has the robotic pancreatoduodenectomy matured sufficiently for widespread adoption or will it remain an operation confined to selected surgeons and specialized centers? A growing body of evidence has addressed the safety, feasibility, and potential benefits of RPD. Although early experience was derived from retrospective and observational studies, more recent randomized controlled trials have provided higher-level evidence regarding its clinical performance. Collectively, these studies have demonstrated a reduced LOS, demonstrated noninferiority in morbidity, and similar oncologic outcomes relative to open pancreatoduodenectomy. However, evidence of safety and efficacy alone does not necessarily establish readiness for broad implementation. The critical question is therefore no longer simply whether RPD can be performed safely, but under what conditions it should be adopted and disseminated. In this review, we evaluate the evolution and current evidence for RPD through the context of the IDEAL (Idea, Development, Exploration, Assessment, and Long-term study) framework, a structured model developed to assess the introduction and evaluation of surgical innovations. Viewed through this framework, the available evidence suggests that RPD has progressed beyond the experimental phase and has entered a stage of evidence-supported clinical implementation. Outcomes remain dependent on surgeon experience, institutional volume, and completion of a substantial learning curve. Accordingly, the transition of RPD into routine clinical practice should be accompanied by structured training, mentorship, outcomes reporting, and appropriate institutional and procedural volume standards. These safeguards will be essential to ensure that expansion of RPD preserves the outcomes achieved in experienced, high-volume centers.